

SUBSCRIBE TO OUR FREE NEWSLETTER
Daily news & progressive opinion—funded by the people, not the corporations—delivered straight to your inbox.
5
#000000
#FFFFFF
To donate by check, phone, or other method, see our More Ways to Give page.
Daily news & progressive opinion—funded by the people, not the corporations—delivered straight to your inbox.

"This is a guy who wants to do service for the corporations," the Democratic US Senate candidate said of his Republican opponent.
Democratic US Senate candidate Abdul El-Sayed said during a televised debate Thursday night that his opponent, Mike Rogers, is "bought off," pointing to the Republican's financial support from the pharmaceutical industry and his opposition to legislative efforts to lower prescription drug prices and provide healthcare to all Americans as a right.
El-Sayed noted that Rogers once described himself as a "champion" of the pharmaceutical industry, which benefited from the Republican's tenure in the US House.
"This is what you can expect from a guy who's bought off: $5 million from corporations to run his previous campaigns," El-Sayed said of Rogers, who opposed the push to let Medicare negotiate drug prices directly with pharmaceutical companies.
El-Sayed said that Rogers "voted to raise your prescription drug prices or to keep them high 19 times" during his seven congressional terms.
"He has the audacity to do an ad looking at the drug prices in Canada," the Democratic candidate continued. "Except for he voted four times to keep you from buying the prescription drugs in Canada."
El-Sayed also touted his support for Medicare for All—which, according to new polling, is backed by two-thirds of US adults—and contrasted that position with Rogers'.
"He voted against the ACA, for God's sake," said El-Sayed, referring to Rogers' opposition to the Affordable Care Act. "I want to guarantee every single person in this country cradle-to-grave coverage, without premiums, co-pays, deductibles. That doesn't have a network. That does not pay a corporate CEO tens of millions of dollars a year."
"This is a guy who wants to do service for the corporations," the Democrat said of Rogers.
Later in the debate, El-Sayed accused Rogers of vying for the "Peeping Tom" vote, citing the Republican's consistent support for mass surveillance.
El-Sayed said he "absolutely" supports putting federal guardrails on Flock cameras and questioned why "we continue to have a situation in which we're watching more and more technology steal more and more data."
"The very Big Tech corporations that are buying his campaigns," El-Sayed added.
Ravi Mangla, national press secretary for the Working Families Party, applauded El-Sayed's performance in Thursday's debate and said that Rogers "has spent his career doing the bidding of Wall Street and Big Pharma CEOs, while watching jobs in Michigan get shipped overseas and prescription drugs grow more and more expensive."
"Tonight’s debate made it crystal clear that Abdul El-Sayed is the only candidate who will fight to put money back in the people's pockets, end the reckless wars abroad, and stand up to the billionaire CEOs who think they should be able to call the shots in Washington," said Mangla.

"Americans are done with a healthcare system that puts profits before people," said Congresswoman Ilhan Omar.
Two-thirds of Americans now support a national health insurance program commonly known as Medicare for All, according to a new poll released Tuesday by KFF, marking the highest level of support recorded since the public health policy group began tracking the proposal a decade ago.
The latest KFF Health Tracking Poll, conducted between September 16-21, found that 66% of US adults favor Medicare for All, up substantially from the 53% who supported the idea when KFF last asked the question in October 2020. Just 34% now oppose it.
KFF's findings come as healthcare affordability has emerged as a major concern heading into November's midterm elections. Health costs and gasoline prices are tied as Americans' top economic worries, while voters now trust Democrats over Republicans by a 20-point margin to handle healthcare costs, according to the poll.
Two-thirds of the public favor Medicare-for-All — the highest share since KFF began polling on the topic in 2016 — but public opinion is highly malleable and support shifts when competing claims from critics and proponents are heard: https://on.kff.org/4zgJv6z
[image or embed]
— KFF (@kff.org) October 6, 2026 at 11:04 AM
The poll results also underscore growing public frustration with the nation's costly and fragmented healthcare system, with progressives increasingly arguing that voters want more than incremental reforms.
"People are sick of a broken healthcare system driven by the greed of the insurance industry and Big Pharma," Sen. Bernie Sanders (I-Vt.)—who twice ran for president as a Democrat on a Medicare for All platform—said Tuesday on social media. "The time to pass Medicare for All is NOW."
Congresswoman Ilhan Omar (D-Minn.) said: "Two-thirds of Americans support Medicare for All. Americans are done with a healthcare system that puts profits before people."
"Medicare for All can save 114,000 lives and $1 trillion a year," Omar noted, referring to a recently published study out of Yale University and adding, "Turns out, progressive policies can be good politics AND good policy."
Audrey Kearney, a senior survey analyst at KFF, told Reuters that “all year, KFF polls have shown that the public is frustrated with the high cost of healthcare, and that may be leading to a desire for change."
As The Guardian reported Sunday, 1,500 unionized nurses gathered in San Francisco last week to rally for Medicare for All, a policy their unions have championed for many years.
Michigan Democratic Senate nominee Abdul El-Sayed, one of the proposal's most prominent 2026 advocates, asked the nurses: “Medicare for who?”
"All!” they shouted back.
El-Sayed then described Medicare for All as addressing “the very simple idea that in the richest, most powerful country in the world you should not have to suffer for your healthcare.”
I believe in Medicare for All like I believe in public schools. There for you no matter what.
[image or embed]
— Abdul El-Sayed (@abdulelsayed.bsky.social) October 4, 2026 at 6:16 AM
The California Nurses Association's Michelle Gutierrez Vo, meanwhile, pointed to the costs and failures of the existing system.
“There’s too many unnecessary illnesses and unnecessary costs,” she said. “What are we doing?”
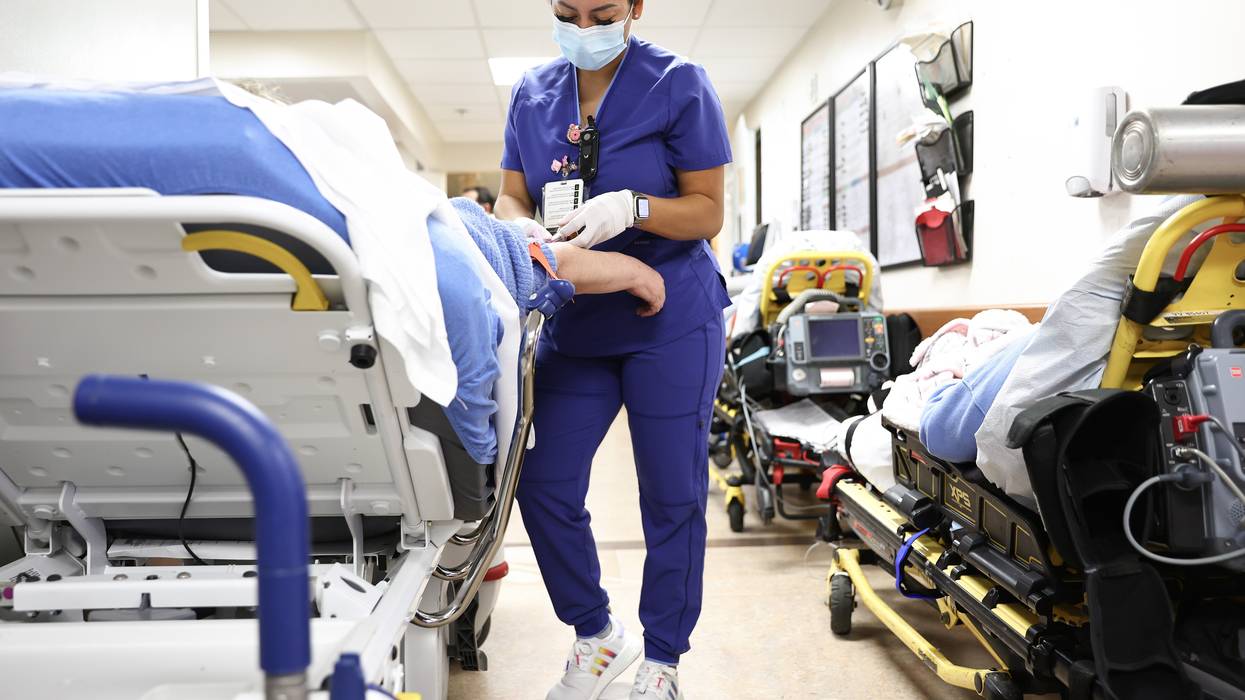
"Not exactly the cancer cure we were promised," quipped one critic.
Artificial intelligence proponents claim AI will make healthcare more efficient, but an analysis published Wednesday suggests that the burgeoning technology is instead helping hospitals identify more lucrative diagnoses—and is driving nearly $1 billion in additional costs for patients and insurers.
The Blue Cross Blue Shield Association (BCBSA) analysis found that the share of inpatient cases billed as "medically complex" rose from 37% at the beginning of 2023 to 40% by the end of 2025. While that may seem like a small increase, it translated into an estimated $942 million in additional costs for Blue Cross plans over two years, including $653 million attributable to secondary diagnoses that pushed hospital claims into higher-paying categories.
“Critically, what we found is underneath all of that data [was] no change in corresponding care for a more complex patient,” Luke Chalker, BCBSA’s senior vice president of product and data science and a co-author of the analysis, told reporters. “We find no evidence of a corresponding change in care.”
The analysis' findings underscore an intensifying battle between hospitals seeking maximum reimbursement and insurers trying to contain payouts—a conflict increasingly mediated by AI. AI-powered coding systems can scan medical records, doctors' notes, and laboratory results for additional diagnoses that can increase the amount hospitals are paid. Ambient AI systems can also listen to clinician-patient conversations and automatically document them.
While AI can have legitimate benefits—like reducing paperwork and administrative burdens—BCBSA contends that the financial incentives built into the nation's fee-for-service healthcare system can turn those capabilities toward maximizing profits.
"Not exactly the cancer cure we were promised," More Perfect Union quipped on social media.
In one example, the analysis examined secondary diagnoses like anemia following major bowel surgery.
“If patients are truly sicker, we'd expect to see more treatment,” Chalker said. “For example, we're seeing significantly more anemia diagnoses at these hospitals without a corresponding increase in transfusions. The disconnect between diagnoses and treatment suggests that AI is identifying more billable conditions, not sicker patients.”
The analysis' findings echo an earlier BCBSA study of maternity care, which found that some hospitals dramatically increased diagnoses of acute posthemorrhagic anemia, while transfusion rates barely changed. BCBSA estimated that the increase in that single diagnosis alone added $22 million to maternity admission costs in one year.
Progressive healthcare advocates argue that the problem cannot be solved by tweaking the current system. Advocates for a Medicare for All-type system, including US Sen. Bernie Sanders (I-Vt.) and Rep. Pramila Jayapal (D-Wash.), propose replacing the for-profit insurance system with a universal public program.
In August, Sanders cited a Yale study estimating that his Medicare for All legislation could save 114,000 lives each year, while reducing national healthcare spending by more than $1 trillion annually.
“We do not suffer from scarcity in this country; we suffer from greed,” Jayapal said at a July Medicare for All shadow hearing.
"Medicare for All is the path to fix the broken healthcare system that has let corporate interests determine who lives and dies," Jayapal added. "The reality is that Medicare for All is the only solution that guarantees care for everyone in the US, brings down costs for working families, and generates savings for the country.

“With everyday costs getting higher and higher, it is clear that we need a system like Medicare for All," said the director of the group behind a new survey.
Nearly half of Michiganders surveyed for a poll published this week said they're struggling to pay for groceries and gas because of the high and rising cost of health insurance, underscoring an affordability crisis that Democratic US Senate candidate Abdul El-Sayed has cited as one of the reasons why the United States needs Medicare for All.
Forty-nine percent of Michigan voters queried by Progress Michigan and Public Policy Polling said the cost of health insurance affects their ability to afford basic necessities at least some of the time. Twenty-four percent said it happens “all the time,” while another 25% said it happens “sometimes.” Among Black Michiganders, the figures were substantially higher, with 34% reporting the problem occurs all the time and 31% saying it happens sometimes.
“Half of Michigan is already struggling with the cost of health insurance,” Progress Michigan executive director Justin Mendoza said Thursday in a statement. “With everyday costs getting higher and higher, it is clear that we need a system like Medicare for All to help Michiganders improve their health and afford their lives.”
El-Sayed, a physician and former Detroit health official, has made universal healthcare one of the three policy pillars of his campaign, alongside getting money "out of politics” and putting it "in your pocket.”
At a Monday "Students vs. Billionaires" town hall at Western Michigan University in Kalamazoo, El-Sayed argued that healthcare should be treated as a basic public investment rather than a commodity.
"You need good healthcare. You need a good education. We need childcare. We need good roads and bridges," he said. "We don’t need to send our money to big corporations to subsidize them, we need to be invested in people so they have the human capital to be able to do all the things as they graduate and come out. That's how the system should work."
El-Sayed has also repeatedly highlighted the plight of families who are insured but still cannot afford care because their deductibles are prohibitively expensive, and others who worry what will happen to their families' healthcare if they lose their jobs—an increasingly likely prospect as artificial intelligence usurps human workers.
“Medicare for All would allow us to actually provide every single person cradle-to-grave insurance,” El-Sayed said in a recent CBS interview, “without having to worry about losing it” after changing jobs, losing employment, getting married, or reaching retirement age.
The health insurance affordability crisis is likely to worsen in 2027. Healthinsurance.org reports that insurers are proposing a median increase of roughly 15% for individual market premiums nationwide, with Michigan insurers seeking an average 14.2% increase. The final rates could change before approval.
“Imagine not having to pay that," El-Sayed told CBS.
A new New York Times/Siena poll of Michigan voters found that 57% of respondents believe El-Sayed would do a better job on healthcare than Republican opponent Mike Rogers. Only 33% said Rogers would do a better job. Among all surveyed women, 67% said El-Sayed would be better for healthcare.
The overwhelming majority of voters ages 18-29 (86%) and Black voters (82%) agreed. Just 4% of Black respondents said Rogers would be better on healthcare. Among young voters, none—0%—said Rogers is the better choice for healthcare.

At long last, the nation’s healthcare plan will guarantee that not only is everyone covered for care, free at the point of service, but that there is a place within reasonable distance to find that care.
After a century of providing healthcare to this rural, southeast Michigan community, Sturgis Hospital closed in June with only 70 hours warning.
The hospital was not on the at-risk-of-closing list that had been published by Sen. Ed Markey (D-Mass.) a year earlier.
Over 300 Sturgis Hospital employees are scrambling to find work. Registered nurse Beth Kelley, who had worked at Sturgis for 32 years, described the meeting room as filled with “shock” and “devastation” when management announced that the hospital was closing.
Nationwide more than 700 rural hospitals are at risk of closing, over half at immediate risk within the next two to three years. The 700 hospitals represent about one-third of all rural hospitals.
The termination of care at Sturgis Hospital overloads the city’s emergency medical services. Director of public safety Ryan Banaszak said, “What was once approximately a 2-mile transport for patients has now become closer to 25 miles, which takes ambulance personnel and equipment out of service for a much longer period of time.”
The impact is great on Michigan Medicaid patients, who cannot use the closest hospital because it is across the state line in Indiana.
“Rural hospital closures lead to significant increases in mortality, and birthing outcomes and obstetric care suffer following closures,” said Michael Shepherd, University of Michigan health policy researcher. The risk increases with every additional mile for emergencies like strokes and heart attacks.
A few weeks later the rural River District Hospital in St. Clair County northeast of Detroit announced the closing of its inpatient and emergency services. Four more rural Michigan hospitals—in Mt. Pleasant, Carson City, Ontonagon, and Dowagiac—are in danger of closing with the upcoming Medicaid cuts.
Rural Americans live sicker and die younger than those in urban areas. Life expectancy is about three years shorter in rural communities. When a rural hospital closes, the mortality rate rises by 5.9%. Rural hospital closures increase mortality for emergencies such as heart attacks and strokes by about 10%.
“There are two kinds of Americans: those who live 12 minutes from an emergency department and those who live 72,” writes Ayla Ellison who grew up in Carmi in southern Illinois. “Whether you survive a heart attack, deliver a healthy baby, or die from something entirely treatable increasingly depends not on the severity of your illness, but on the distance to the nearest hospital,” she continues. She explores the consequences of rural hospitals folding in a country where no one is responsible for assuring help is close enough for a chance at life. The hospital in Carmi closed 20 years ago. Nine more Illinois hospitals are at risk of closure, most of them in southern Illinois.
Other states are worse off. In Mississippi, 51% of the rural hospitals are at risk of closing; in Alabama, 52%; in Arkansas, 68%.
Dr. Kenneth Williams battled for decades to sustain the hospital (Alliance Healthcare System) in Holly Springs, Mississippi. Rapid expansion of Medicare Advantage plans reduced reimbursement and increased denials of payment to the hospital. In 2023, facing financial desperation, the hospital converted to Rural Emergency Hospital status, a federal program designed to stabilize struggling rural hospitals. The Center for Medicare and Medicaid Services (CMS) later removed that designation, leaving the hospital again fighting to stay open.
Nationwide more than 700 rural hospitals are at risk of closing, over half at immediate risk within the next two to three years. The 700 hospitals represent about one-third of all rural hospitals. That report was prior to the passage of HR 1, the “One Big Beautiful Bill” that slashes $1 trillion from Medicaid. The crisis escalates from grim to disastrous with the looming Medicaid cuts.
Federal efforts to save our rural hospitals have been pitifully inadequate in the face of the towering problem.
Critical Access Hospitals, created by Congress in 1997, allow small rural hospitals to receive cost-based Medicare reimbursement. The plan was designed to stem the tide of closures.
Between 2010 and 2025, 152 rural hospitals closed. Of these, 52 were Critical Access Hospitals.
In 2021 Congress created Rural Emergency Hospitals. This designation provides for enhanced Medicare payments allowing rural hospitals to continue with outpatient and emergency services only, instead of closing.
In 2023, Sturgis hospital was “saved” by conversion to a Rural Emergency Hospital, delaying its shutdown by three years.
Neither these nor any other federal plans are big enough or thorough enough to work.
CMS Director Mehmet Oz recently visited Kentucky, home of 35 rural at-risk hospitals. He touted the $50 billion in Rural Health Transformation Funds as the solution. The assertion is absurd.
At best, Kentucky will get $1 billion from the rural transformation funds as it loses $21 billion in Medicaid funds. Not even a wizard can turn that into a winner.
As Boston University professor Alan Sager notes, no US entity is responsible for sustaining or building or financing hospitals based on community need.
“The whole Appalachian area has been abandoned, but its hospitals should be funded and improved, as a necessity of life—like the post office,” says Dare Cima, who is from southeastern Kentucky.
With passage of H R 3069, Improved Medicare for All, finally, the nation will take responsibility for assuring that rural areas have adequate facilities. Hospitals will be paid quarterly, in advance, with a global budget that provides operating expenses.
The allocation to hospitals ensures proper staffing with safe nurse-to-patient ratios and optimal staffing for physicians and other healthcare workers. Physician salaries can be included in the global budget. Adjustments to the operating budget will be made “to decrease healthcare disparities in rural or medically underserved areas.”
Special projects funds will be used to end discrimination based on race or other underserved categories including geography. Funds will be allocated for construction of new facilities where needed. At long last, the nation’s healthcare plan will guarantee that not only is everyone covered for care, free at the point of service, but that there is a place within reasonable distance to find that care.
The late Dr. Ewell Scott, Medical Staff president of St. Clair Regional Medical Center in Morehead in the mountains of eastern Kentucky, predicted that if current policy continued, it was just a matter of time until all of Kentucky’s hospitals east of I-75 would be closed.
Sadly, that prediction is breathtakingly close as 16 of east Kentucky’s hospitals in the 5th Congressional District, including Dr. Scott’s beloved St. Clair hospital, are on the list of those endangered with closing by the passage of HR 1.
But Dr. Scott was fighting for a different future. He persuaded the City of Morehead to pass a resolution supporting Improved Medicare for All, a national single-payer plan that would cover us all and fund the hospitals.
Dr. Scott urged all who would listen to tell their congresspersons: “We know the solution. You’ve got to have the guts to stand up and do it.”

Everyone who wants Improved Medicare for All to become law should reach out to friends, family, and neighbors and urge them to get involved and we should create Improved Medicare for All clubs nationwide to galvanize this movement.
Reaching our destination won’t be easy. Americans have been fighting for universal, government-sponsored national health insurance for over 100 years. Progress was made in 1965 and 1972, when Medicare was enacted and expanded. Since, then, though, not only was Medicare not expanded; frustratingly, its opposition has succeeded in partially privatizing it.
The moment in which the nation finds itself does not appear particularly hopeful even for the country to remain the United States. Not since the Civil War has the nation been so divided.
Almost 100 years ago, the Great Depression brought economic collapse and with it, a serious threat to democracy. Like today, there was hostility to those perceived to be elites. The economic turmoil opened the door to widespread radical movements and demagogues.
Like today, “others” were scapegoated, along with the “elites.” Jews were a particular target. One extremely powerful, influential anti-Semite was radio preacher Father Charles E. Coughlin. At the height of his popularity, his Sunday radio show, Golden Hour of the Little Flower, which was broadcast over dozens of radio stations around the country, was heard by nearly one in four Americans and had a larger share of the listening audience than the more recent broadcasters Howard Stern, Rush Limbaugh, Paul Harvey, and Larry King put together. Before the 1936 Presidential election, he asserted. “This is our last election. It is fascism or communism. We are at the crossroads. I take the road to fascism.”
Another leader of the time seeking radical change was Louisiana Governor and then Senator Huey Long, who targeted the extreme income and wealth inequality which exploded during the so-called Roaring Twenties. His Share Our Wealth plan proposed confiscatory income, wealth, and inheritance taxes on the wealthiest and generous federal benefits for working and middle-income families. Just one year after announcing the plan, there were 27,000 Share Our Wealth local clubs, mainly in the South, with over 7.5 million members.
Long planned to run for president as a third-party candidate, even setting out his plans and strategy in his 1935 novel, My First Days in the White House. His plans came to an abrupt end, though, in September, 1935, when he was assassinated by the son-in-law of a political opponent whom Long had targeted and slandered.
Another radical leader of the time was socialist author and journalist, Upton Sinclair, who sought to expose corruption in business and government, while shining a spotlight on the horrendous working conditions at the time. In 1934, he ran for Governor of California on his “End Poverty in California” (EPIC) plan, which, like Long, he set out in a novel, the 1933 I, Governor of California, and How I Ended Poverty: A True Story of the Future. His plan called for the state to seize idle factories, farms, movie studios, and other businesses and convert them to worker-run co-ops, financed with progressive revenue. Two dozen candidates who ran on the EPIC plan won seats in the state legislature, including lawyer and journalist Culbert Colson, who successfully ran for Governor four years later, becoming the first Democrat in 40 years to win the office.
At base, people were suffering and open to radical solutions to address their misery. Franklin Roosevelt was undoubtedly the right person to meet that moment. He was extremely politically savvy, pragmatic, and smart. His speeches were inspiring and visionary. His famed fireside chats, named to convey a sense of cozy familiarity, established a strong personal connection between the president and the American people. He radiated optimism. Perhaps most importantly, he exuded compassion and empathy.
Though he enjoyed extraordinary wealth and privilege, his paralysis, resulting from contracting polio at age 39, was apparently transformative. His close colleague Frances Perkins, who became the first woman to serve as a Cabinet secretary to a president, described his transformation in her book, The Roosevelt I Knew. She witnessed Roosevelt undergo, she wrote:
“a spiritual transformation during the years of his illness….The man emerged completely warmhearted, with humility of spirit and with a deeper philosophy. Having been in the depths of trouble, he understood the problems of people in trouble.”
The brilliant achievements of the charismatic Roosevelt can continue to be felt today. His Social Security program was carefully crafted to embody basic American values, containing both progressive and conservative elements that continue to appeal to Americans across the ideological divide. Roosevelt’s legacy provides good news in today’s troubling time. As polarized and hostile as Americans are in general, we are overwhelmingly united in our support for Social Security and Medicare, which grows out of Roosevelt’s legacy. A 2025 Bipartisan Policy Center poll, for example, found that 91 percent of Americans believe that Medicare is valuable. That same poll found that 93 percent believe Social Security is valuable. Numerous other polls, taken over many years by groups across the ideological spectrum, have found similar results of unanimity of support.
Despite how divided and combative the American people are generally, these numbers provide a ray of hope. Supporters of Improved Medicare for All must build on this support systematically. The cause and its success may have the byproduct of helping to bring the country back to more normal, less fractured, and hostile times.
Notwithstanding Joe Biden’s 2020 victory, none of the Democratic presidential nominees in the last few election cycles nor the mainstream leaders of today’s Democratic Party appear to match Roosevelt’s political insights or capabilities. Senator Bernie Sanders (I-Vt.) showed that he can garner enthusiastic support, as has New York Mayor Zohran Mamdani, but the Democratic leadership has not embraced them or similar charismatic progressive leaders. Consequently, the Democratic Party has not spoken with one single clear voice and capitalized effectively on the broad support for Medicare and Social Security.
Unfortunately, unlike Roosevelt, the current politicians who appear most likely to win the 2028 Democratic presidential nomination do not appear to have the vision or charisma to capitalize on the popularity of Medicare and Social Security. There is no candidate with Franklin Roosevelt’s many gifts who is in a position to fully embrace Improved Medicare for All and ride it to victory, together with an expanded Social Security program. At this moment, the Democratic Party does not seem united in a path forward, certainly not one that would embrace as bold a vision as Improved Medicare for All.
Nevertheless, the political movements of the 1930s provide evidence that those policy goals can be achieved without a political leader. While the Share the Wealth and End Poverty in California grassroots movements had high-profile personalities leading the efforts, another astoundingly successful grassroots movement did not.
While policymakers in Washington were primarily focused on unemployment in the early years of the Great Depression, they apparently did not fully appreciate that hidden in the shadows of the unemployment numbers were impoverished, aged parents reluctantly dependent on their adult children for support. When Social Security became law in 1935, every state but New Mexico had poorhouses (sometimes called almshouses or poor farms). The vast majority of the residents were elderly. Most of the “inmates,” as they were often labeled, entered the poorhouse late in life, having been independent wage earners until they were no longer able to work.
Although official Washington was not focused on the plight of the elderly, ordinary people were. In September 1933, a Long Beach, California doctor, Francis E. Townsend, found himself at age 66 unemployed with no savings. He was gazing out his window when he spotted two elderly women, dressed in rags, rummaging through his garbage, searching for anything edible. It so upset Dr. Townsend that he sent a letter to the Long Beach Press-Telegram, his local newspaper.
His letter, published on September 30, proposed a plan. He proposed that the federal government provide every person aged 60 or older a pension of $200 per month, a princely sum in the 1930s. The only requirement, in addition to being retired and not a criminal, was that the recipient had to spend every penny within 30 days of receipt. He claimed that his plan would not only eradicate old-age poverty; it would so stimulate the economy that it would create jobs and end the Depression.
The idea spread around the country at a rate astonishing to believe in that pre-Internet, pre-social media world. A year after Townsend wrote his letter to the newspaper, Time magazine reported in its October 15, 1934, issue:
By last week the flow of money…was enough to pay the wages of 50 people….There were Townsend Clubs in every State except Delaware…. Between 2,000,000 and 5,000,000 people had put their names to petitions begging their Congressmen to vote the Plan into effect at once.
Even in the short time between the publication of Townsend’s letter and the establishment of Roosevelt’s Committee on Economic Security (CES), his interagency task force to develop the Social Security Act, supporters of the Townsend proposal were exerting considerable pressure on the Administration and Congress. At the height of CES’s work, mail from Townsendites averaged about 1,500 letters a day. In some congressional districts, a candidate’s position on the Townsend plan determined the outcome of the election.
By mid-October 1934, Townsend had acquired two million signatures on petitions urging congressional action on his plan. Just three months later, he was claiming to have 25 million signatures. The number of Townsend clubs had climbed to 25,000 across the country. The plan’s popularity was not hard to fathom. As political columnist, Mark Sullivan with The New York Herald Tribune explained: “The zeal of those promoting the plan is evangelical, almost fanatic.”
A Time magazine piece explained the political climate surrounding the plan:
The good doctor’s Old Age Revolving Pensions scheme, better known as the Townsend Plan, had by last week become one of the biggest political facts in the US. The early California groundswell of sentiment in its favor had grown to a tidal wave, battering at nearly every door in House and Senate Office Buildings.
In the end, the Townsend plan, which policy experts understood to be unworkable—benefits would have cost half the income of the United States, for example—was instrumental in enacting Social Security, because it provided the widespread pressure to address old age insecurity. That is the kind of pressure that today could get Improved Medicare for All enacted, as well.
To build such a movement is both easier and harder than it was almost 100 years ago. While American news consumption is much more siloed, social media, email chains, and the internet generally allow people to connect much more easily and effectively. Of course, people are drawn to a variety of important issues, including climate change, gun violence, and immigration. Nevertheless, similar to the 1930s with respect to old age insecurity, Americans appear to be reaching the end of their rope with respect to the nation’s health insurance companies, as was demonstrated by the strong, instantaneous outpouring of frustration with commercial health insurance in response to the murder of the UnitedHealthcare executive.
The movement for Improved Medicare for All already has powerful, effective, knowledgeable and resourceful leaders. They are members of a far-reaching, forceful coalition, the National Coalition for Medicare for All. The coalition meets regularly to strategize and advance the issue. They are doing a spectacular job in championing and pushing forward Improved Medicare for All. To help them succeed in its enactment, the rest of us should provide them with an overwhelming army of passionate, dedicated grassroots supporters.
The goal, as impossible as it might seem, is to build a broad-based, energized, and determined Townsend-like grassroots movement. Everyone who wants Improved Medicare for All to become law should reach out to friends, family, and neighbors and urge them to get involved. In addition to joining already-existing groups, such as MoveOn, Public Citizen, and Indivisible, supporters should create Improved Medicare for All clubs.
Those clubs should play a number of roles. First, the clubs could educate members and others about why Improved Medicare for All is so important. They could discuss at club meetings how health care is a right, not a privilege and how Improved Medicare for All is the only realistic way to get us there. Just as the Townsend clubs hounded their elected representatives, supporters should flood offices with phone calls, keep track of when their Senators and representatives are home from Washington, DD, and attend their town halls if they host them. If they don’t, the clubs can seek meetings with their members and staff. If their members won’t commit to cosponsoring Improved Medicare for All legislation, they should put pressure on them, including picketing their offices.
With or without membership in an Improved Medicare for All club, those wanting to help the effort have many other steps they can take. On this and many other issues, there are a multitude of effective civic and social organizations active on political issues, such as Indivisible, MoveOn, Public Citizen, and many more. If you have access to a union, they remain extremely important and effective actors with which to engage. With or without engagement with these organizations, it is perhaps most important to educate family, friends, and neighbors. Writing letters to the editor and posting on social media are helpful actions. If possible, there may be an opportunity to hold an event at a school, perhaps through the PTA, as well as at assisted care facilities, libraries, and other spaces. If you want to organize an event but want experts to be the speakers and/or panelists, that is relatively easy these days, particularly, if the speakers can appear virtually.
Moreover, because healthcare costs affect everyone, the issue of Improved Medicare for All can be tailored to a variety of organizations and groups. School groups may be concerned about the impact of healthcare costs on their budget. Women’s groups may be concerned about reproductive rights. Again, the point is to make the movement for Improved Medicare for All as large a mass movement as possible.
This moment in history may make enactment of Improved Medicare for All appear as far away as it possibly could be. However, the mythological phoenix should be the symbol of the effort. The phoenix, an immortal bird that continually arose from the ashes of its predecessor, symbolizes renewal after a period of hardship.

"Voters see this election not just as a referendum on Trump... but as a repudiation of the entire political system."
A poll released by the Cook Political Report on Thursday shows US voters in key swing districts overwhelmingly dislike artificial intelligence companies—but are feeling warm about Medicare for All.
In total, the poll finds that voters in 37 swing districts across the US view AI companies unfavorably by a two-to-one margin, with 64% of voters saying they're more concerned than excited about the technology, compared to just 31% who say they're more excited than concerned.
Opposition to AI data centers is even stronger, as 63% of voters say they would oppose building one in their communities, compared to just 28% in favor. Additionally, 44% express strong opposition to local data center construction, making strong opposition higher than overall support.
At the same time, the poll finds much stronger support for Medicare for All, with 62% of swing-district voters having a favorable view of the policy, compared to 34% who said they were opposed. The intensity gap is also notable, as 41% of voters sat they have a strongly favorable view of Medicare for All, while just 25% have a strongly unfavorable view.
This does not mean that these voters are socialists, however, as the poll shows just 32% expressing a positive view of socialism, compared to 58% expressing a negative view. When it comes to Democratic Socialists of America (DSA), 37% of voters say they have a favorable view of the group, compared to 56% who say they have an unfavorable view.
Regardless of specifics about policy and ideology, the poll shows a deep dissatisfaction with the American political system and an openness to major changes.
Amy Walter, editor-in-chief of the Cook Political Report, commented in a social media post that "the most interesting finding was that these voters see this election not just as a referendum on Trump (who’s underwater by 16 points), but as a repudiation of the entire political system."
Walter pointed to a striking finding among independent voters in the survey, who vastly preferred a candidate promising to change the whole political system compared to a candidate who would just be a check on Trump.
"This also suggests," Walter added, "that these voters would want a Dem-led Congress that focuses more on an agenda that tackles corruption and institutional rot than one that focuses solely on Trump and his overreach."
Yasmin Radjy, executive director of Swing Left, said that the Cook Political poll "tracks with everything we're hearing" in conversations with voters.
The idea that the "system is broken," wrote Radjy, "is overwhelmingly the top issue/theme we hear from voters across the ideological and partisan spectrum—even more than affordability!”
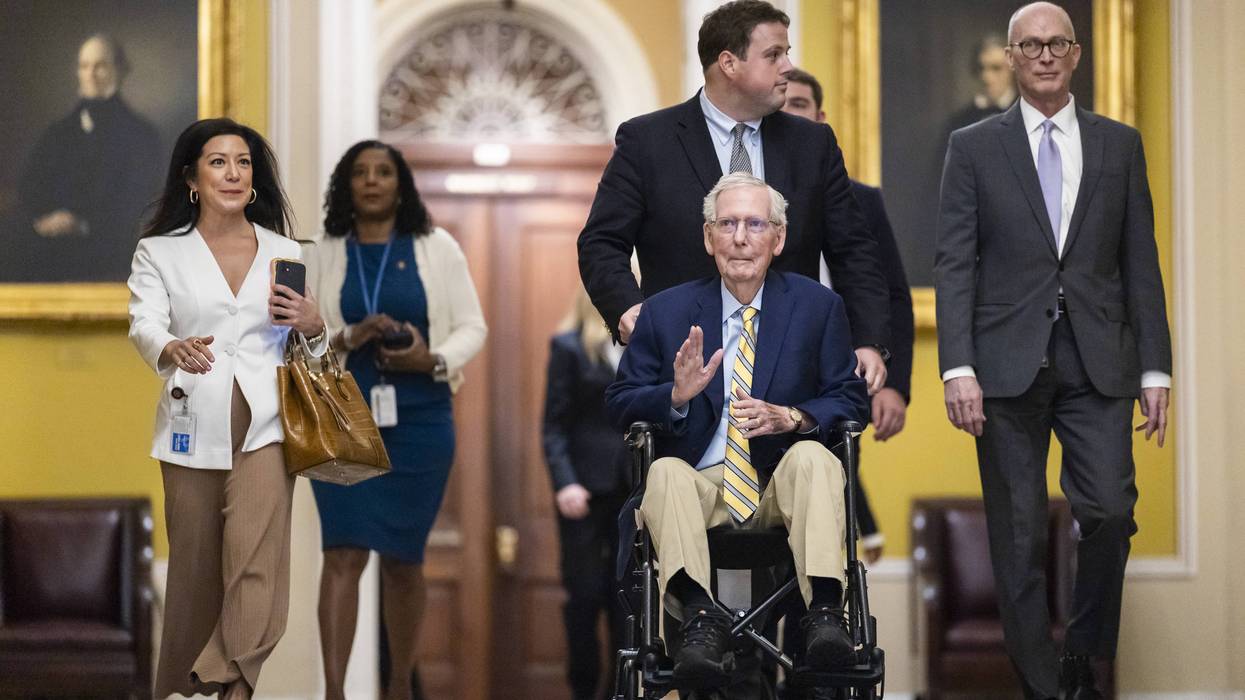
"They oppose the things for us that they give to themselves," said universal healthcare advocate Melanie D'Arrigo.
Former US Senate Majority Leader Mitch McConnell finally came back to the Capitol on Monday after a three-month absence that fueled calls for the Kentucky Republican's resignation and widespread speculation over whether he was even still alive.
The 84-year-old senator, who plans to retire after this term, has not been seen in public since he was hospitalized following a fall in mid-June. However, he announced Monday evening that he would return to the Senate floor to cast a vote.
"My recovery has been a long and often frustrating process, and the lingering effects of childhood polio haven't made it any easier," said McConnell, who had reporters capture footage of him leaving his home and arriving at the Capitol.
McConnell said he was "still not quite back to 100%" but had assured Senate Majority Leader John Thune (R-SD) that, as he continues with physical therapy, he will do his "best to be present for tough votes" when the GOP needs him.
According to NBC News' Frank Thorp V, the senator told reporters at the Capitol: "I must admit, after two years, two decades after dodging your questions, I wasn't sure how many of you would be here today. So I'm glad to see you. Time to get back to work to finish the job for this Congress."
"I'm here to work on the farm bill... and as you know, I have an ongoing interest in NATO and backing up our good friends who are totally in the fight against the Russians," added McConnell.
Punchbowl News' Andrew Desiderio said that the reporters he spoke with on Monday "were barred from recording video."
Melanie D'Arrigo, executive director of the Campaign for New York Health, which advocates for universal, single-payer healthcare, forcefully called out the Republican senator in response to this statement on social media Monday.
"Mitch McConnell has spent his career opposing paid sick leave and cutting healthcare," she said. "He just took three months of paid leave, with healthcare... subsidized by taxpayers. They oppose the things for us that they give to themselves."
With McConnell due to finish his term at the end of this congressional session, Republican US Rep. Andy Barr and former Democratic Congressman Charles Booker are facing off to replace him in the November midterms—in which Democrats are aiming to win back majorities in both chambers.
Before McConnell announced his return, Booker highlighted his "absolutely embarrassing" absence on social media, writing that "Kentuckians are getting crushed by the rising costs of groceries, healthcare, and gas while McConnell gets a taxpayer-funded paycheck and Kentucky gets an empty seat."
Booker and Democratic Kentucky Gov. Andy Beshear—a potential 2028 presidential candidate—are among those who have criticized McConnell over his lack of transparency regarding his absence over the past few months.

Because Improved Medicare for All is such a winning policy, powerful forces opposed to it must rely on fear, division, and lies to prevail. Knowing their lines of attack will help assure our ultimate victory.
To move forward toward Improved Medicare for All, the supporters must be strategic, persistent, and patient. In addition, supporters must be ready to neutralize the counterattacks from the opponents who are rich, formidable, and devious.
Because Improved Medicare for All is such a winning policy, those powerful forces must rely on fear, division, and lies to prevail. They succeed not by convincing us with reason but rather by tricking us into working against our own best interests. President Roosevelt exposed this dynamic in 1936, as he fought for our Social Security. “It is an old strategy of tyrants to delude their victims into fighting their battles for them,” he warned us.
As a first step, it is imperative to recognize who the “tyrants” are. They include some of the largest, most profitable, multinational corporations in the world, the ones that profit so enormously from the current healthcare system. The “tyrants” also include billionaires who are determined to amass more and pay as little as possible toward the common good. These wealthiest people in the history of the world have no intention of paying their fair share.
In addition to them are their surrogates, some of whom may be disguised. They include those we elect, who are supposed to work for us, but want to keep open and flowing the pipeline to campaign contributions and other benefits the wealthy “tyrants” provide. Some of the surrogate-politicians are obvious. They seek unabashedly and openly to rip away even the inadequate health insurance Americans currently have. They are the ones working toward the further privatization of Medicare.
Some, though, whether they rationalize to themselves or simply are confused and don’t realize that they are doing the bidding of the “tyrants,” claim that they support national health insurance, but argue that it’s not practical. They not only don’t fight for Improved Medicare for All, they muddy the debate and even may subtly throw up roadblocks to its enactment. Another group of surrogates are some journalists and editors who often work for publications owned by the billionaire “tyrants.”
All of these surrogates are highly influential and may convince your family, friends, neighbors, and even you, that Improved Medicare for All is something to be feared – notwithstanding that virtually every other industrialized country has their own form of Improved Medicare for All, systems that cover their entire populations less expensively and have better health outcomes than the United States.
To understand how the “tyrants” and their surrogates delude their victims – the rest of us – into fighting among ourselves and working against our own best interests, it is essential to keep in mind the Powell memo of the 1970s and the Gingrich memo of the 1990s. Underlying both was the retreat from honest policy discussions and instead a power struggle backed by huge amounts of money. Their views represent a small minority, so their method of prevailing is to divide and instill fear.
Supporters must be hyper-vigilant against the monied interests tricking the American people into succumbing to this “old strategy of tyrants.” Those who want to enact Improved Medicare for All must understand the facts and the ploys.
Perhaps the oldest line of attack is simply to call Improved Medicare for All “socialized medicine.” The phrase “socialized medicine” has become the proverbial four-letter curse word to many Americans. Opponents are quick to label any health proposals they don’t like, “socialized medicine.”
One might think that the phrase, “socialized medicine,” has lost its bite. After all, the Soviet Union and the Cold War officially ended decades ago, on December 25, 1991, when the hammer-and-sickle flag last flew over the Kremlin in Moscow. The phrase appears to be effective because it invokes irrational fears of change and the unknown. It is, in essence, shorthand for something that is foreign, dangerous, and scary.
Because the charge plays on people’s fears, the lie that Improved Medicare for All is socialized medicine can’t be defeated with logical explanations. Rather, it makes sense to address quickly the epithet but then immediately pivot to what people like about Improved Medicare for All.
Another powerful lie is that Improved Medicare for All will hurt the people who are currently on Medicare. This is a deeply cynical stratagem, but, unfortunately, it is effective. Because seniors and people with disabilities, on average, have the greatest health care needs, they are, as a group, particularly susceptible to this kind of fearmongering. It is therefore imperative that advocates of Improved Medicare for All have a honed, well thought-through strategy aimed toward current Medicare beneficiaries and those close to turning age 65.
In fact, those currently on Medicare will be much better off with Improved Medicare for All. Their benefit package will be more comprehensive, their out-of-pocket costs will drop to zero, and the security of the program will increase, since everyone will have a personal stake in seeing it expanded and not cut.
Moreover, it will be simpler. Gone will be all premiums, deductibles, co-insurance, and co-pays. Those who today have their Medicare premiums automatically deducted from their Social Security benefits will see those benefits increased. Gone also will be the impossible tasks of deciding what prescription drug plan best covers one’s future needs, whether to go with so-called Medicare Advantage, and if so, which one, and if not, whether to buy a supplemental plan and if so, which one.
It is important to recognize that there is a thread of a concern that vaguely connects the “socialized medicine” charge and the accusation that current beneficiaries will be hurt. Today, Medicare and Social Security are accurately recognized as earned benefits. To qualify for those benefits, a worker has to have worked and contributed for long enough to be insured, in the case of Social Security and Medicare’s Part A hospital insurance. Workers contribute to the cost of those benefits throughout their working lives, underscoring their earned-benefit nature. Supporters of Improved Medicare for All can and must deal with the sense of current beneficiaries that they earned their Medicare, while it will just be “given” to everyone else, when it is expanded.
The reality is that unlike retirement income, which replaces earned wages, everyone needs health care. The nation has some means-tested programs, like Temporary Assistance for Needy Families, which are designed to alleviate poverty, some earned-benefit programs, like Social Security, which are designed to replace earnings, and some universal benefits, like public parks, freeways, and the police, which are designed to safeguard and improve the lives of all of us.
As much as the American image is one of individualism, virtually all Americans recognize the importance of some communal activities. While Americans differ about whether there should be a military draft, virtually everyone accepts the need for a military paid for collectively. Similarly, public libraries, local fire departments, and public roads and bridges are all seen as public goods appropriately paid for with tax dollars and available to all of us.
With health insurance so tied to employment, it often has to be earned – but it shouldn’t. Having guaranteed high-quality health insurance with no out-ot-pocket costs as a benefit to all Americans is what it means for it to be a right, not a privilege.
It is important to be especially aware of how this subtle attack on national health insurance paid through taxes is perceived not just by Medicare beneficiaries but also by union members. Many unionized workers have been successful in negotiating for excellent health insurance. To obtain the plans, the workers generally had to trade away higher cash compensation. Consequently, it is not surprising that they are reluctant to give them up.
The message to the workers is that, as excellent as their current plans may be, the new coverage will be even better. Union members should be assured, and the Improved Medicare for All legislation should require, that their employers continue to pay what they have been paying in total compensation. Instead of paying that compensation in the form of health care premiums to health insurance corporations, though, the payments will now be in the form of increased current compensation and non-health care benefits.
A related fear tactic to the claim that current Medicare beneficiaries, union members, and others will be worse off is for opponents to tell you that you will lose your current health insurance. The implication is that either it won’t be replaced or the replacement will leave you worse off. It is effective not because people so love their current health insurance, but because the fear of losing even the inadequate coverage you may now have is literally a matter of life and death. It is a classic deployment of people’s aversion to loss. It is another tactic aimed at division.
As a related matter, opponents seek to play on the fear of loss by emphasizing that people will lose choice. Importantly, the choice that people will lose is trivial – to which insurance company their hard-earned money goes.
Most Americans will gain choice in what matters: who their health providers will be. Indeed, Improved Medicare for All will improve people’s ability to get the care they want from the doctors and hospitals they want anywhere in the country and ensure continuity of care.
Another way that opponents have sought to turn people away from Improved Medicare for All is with a sleight of hand. They emphasize that federal expenses will increase resulting in increased taxes or borrowing. Indeed, this same sleight of hand is used to convince too many Americans that today’s Medicare is unaffordable. By focusing on the money going into the government’s coffers and out to providers, opponents seek to convince Americans that Improved Medicare for All will produce “big government,” which is somehow scary and negative.
The truth is that in the modern world, no one is truly opposed to “big” government; it is just that progressives and conservatives have different views of what a big, powerful, modern government should do. Conservatives want a big government military and a big brother government, limiting what women can do with their own bodies, what schools can teach, what museums can display, what kind of gender-affirming care parents, doctors, and children can utilize, how immigrants should be treated, and so on. Progressives want all of us, collectively through government, to ensure every American has economic security in the form of expanded Social Security, health care as a matter of right, a living wage, and more.
If the nation once again has a truly progressive tax system, we can have much greater economic security for everyone. If multimillionaires, billionaires, and multinational corporations were simply required to pay their fair share and the revenue raised dedicated to Improved Medicare for All, that would be sufficient to cover the costs. Even if some revenue were to come from working families, though, their out-of-pocket costs would be considerably lower than today. It is just that the payments would go to the federal government, rather than UnitedHealthcare and other private health insurance companies.
At base, the issue isn’t big government versus small government or increased taxes. It is one of values. That is what supporters should emphasize. Not only will Improved Medicare for All cost less, the money will be spent more productively. Instead of wasteful time spent on the phone appealing denials and seeking pre-authorizations, most of the monies will be spent on paying doctors, hospitals, and other providers.
Another fear tactic is to selectively point to other countries and claim that the quality of care will decrease, at least for the very wealthy, and people will have to wait for inordinately long periods of time for basic care. Importantly, both parts of that framing are untrue. They are both well-cultivated myths. As many people know, the United States is worse than its counterparts in terms of health care outcomes and affordability of care. What is generally not known is that it measures around average or worse in terms of timeliness of care.
The truth is that wait times to see a primary care doctor or a specialist vary among countries that have mandatory, universal health care plans, as do wait times for urgent and non-urgent surgery. Some are longer wait times than patients experience in the United States and some are shorter. Indeed, doctors in other countries are much better at providing care after hours and even make house calls!
What is of legitimate concern are the people who will lose their jobs as our health care system becomes more efficient. That is an issue that proponents of Improved Medicare for All must address. Indeed, proponents not only recognize this responsibility; they include, in their Improved Medicare for All proposals, ways to address it.
Every single job loss is generally a destabilizing event for working families. it is essential that the workers who are displaced are properly treated. Systematic, planned, and consistent outreach should be made to those workers.
One way to alleviate the many fears and concerns that Roosevelt’s “tyrants” are sure to exploit is through an incremental approach, so that Americans will see that they are no worse off, and, in fact, are better off, when Medicare is improved and expanded. Ideally, the incremental steps should combine expansion to additional groups with improvements for current beneficiaries. In that way, current beneficiaries will see clearly the advantage to them. As more Americans receive the benefit, along with an active campaign to assure people additional expansions will leave them better off, not worse off, this natural fear of change should dissipate, and support for expansion increase, like a snowball rolling down a snowy hill.
As long as the final destination remains in mind and is continually invoked, steps that are truly along the way help, but supporters must be wary of disguised alternatives and incremental steps that will hurt the effort. Numerous polls reveal that Medicare for All is an extremely popular idea. Unfortunately, those who oppose the idea of Improved Medicare for All or simply don’t completely understand its striking advantages, have put forward proposals that are decidedly not Improved Medicare for All and, indeed, would not lead us to our desired destination.
The far right is not the only source of these similar-sounding alternatives. Some Democrats have advanced these confusing alternatives. They do so, while seeking to persuade supporters that Improved Medicare for All is not practical, not politically realistic. The assertion that Improved Medicare for All is somehow not able to be enacted may be simply a misguided perception, or it may be a product of the work of the monied interests. In either event, it is destructive and must be taken seriously.
At base, advocates must be wary of steps that appear to point in the right direction, but carry significant risks of derailing the effort. Anything short of a universal, mandated Improved Medicare for All has to be clearly understood as simply a stop along the way, not the final destination. That final destination cannot have an opt in or an opt out, nor include a competing commercial alternative. Just as Social Security is and indeed must be mandatory and virtually universal to work so well, Improved Medicare for All must be, also.
An important lesson from history is that even when victory is achieved, particularly if the victory is incremental, the fight continues. It should be celebrated. It should not be seen, though, that the fight is over. The enactments of Social Security and Medicare were hard fought. Once they were well established and popular, the monied interests sought to prevent their expansion and undermine them from within. Indeed, there are many who today seek to undermine public education with vouchers and charter schools, illustrating that these fights never end.

The pessimistic view that we are moving in the wrong direction sees only the waves at the surface. It misses the subterranean tremors underneath. If we fight, we can win.
As policy-wise and popular as Improved Medicare for All is, the nation may appear to be as far away from enacting Improved Medicare for All as possible. During his first term, Trump did what he could to accelerate the privatization of Medicare. Unfortunately, his thumb on the scale in favor of privatized Medicare is not only back, but is on steroids.
Adding to the sense that the nation may be as far away from Improved Medicare for All as possible, the Republicans enacted legislation that is projected to cause 15 million people to lose their health insurance. Adding to the sense that we are nowhere near enacting Improved Medicare for All, the two prior presidential elections, in 2016 and 2020, saw Senator Bernie Sanders (I-Vt.) and Senator Elizabeth Warren (D-Mass.), two leading champions of Medicare for All, lose in the primary to the more centrist candidate Hillary Clinton, in 2016, and Joe Biden, in 2020. Trump defeated Clinton and won a second term in 2024 against Vice President Kamala Harris. Though Harris did not mention the fact in her presidential campaign, she was an original cosponsor of the Sanders-authored Medicare for All Act.
Trump’s election to a second term, the Republican control of Congress (as these words are written), and a Supreme Court with two-thirds of the justices who are acting as Trump advocates rather than independent jurists appear to suggest that the nation is moving away from national health insurance. But it is crucial to recognize that today is only a snapshot in time. The pessimistic view that we are moving in the wrong direction sees only the waves at the surface. It misses the subterranean tremors underneath. The Republican cuts to health insurance are already putting a strain on rural and inner-city hospitals, as well as nursing homes. The nation is seeing hospitals close as a result of the enactment. Their closure, in turn, strains even those hospitals and nursing homes not directly affected by the cuts.
Improved Medicare for All won’t magically become a reality. It will take all of us who support it to fight for it, in small and large ways.
With the cost of health care rising and, with it, increased insecurity, a majority of the electorate are concluding that the nation is moving in the wrong direction. Perhaps even more significantly, it will become clearer and clearer that the current path is unsustainable.
Importantly, two action-forcing events requiring Congressional legislation are on the horizon. Social Security and Medicare Part A, by law, can only pay benefits if they have sufficient dedicated revenue to cover their costs. To avoid an automatic across-the-board reduction of around 20 percent of the monthly Social Security benefits received by more than 70 million beneficiaries, and to avoid hospitals no longer being reimbursed, Congress must act. However the precise dates shift over the next few years, Congress unquestionably will have to act in the next half decade or so, before the revenue is insufficient to continue to pay full benefits.
Those action-forcing events provide an opportunity. Because those action-forcing events will result in must-pass legislation, provisions that expand Medicare, as well as Social Security, could be included. To make that a reality, though, it is essential that those who support Improved Medicare for All are fully prepared.
Improved Medicare for All won’t magically become a reality. It will take all of us who support it to fight for it, in small and large ways. The wonderful news is that determined activists are currently working hard to make Improved Medicare for All the law of the land. Building a winning coalition and other steps are already underway.
It is imperative that a winning coalition is built strong enough to defeat those who will fight against Improved Medicare for All. Physicians have been extremely active politically since the United States first started to seriously debate universal health insurance at the start of the twentieth century. Initially, the American Medical Association, whose members in 1910 comprised more than half the doctors in the nation, endorsed the legislation under consideration. Individual doctors, however, strenuously objected and made those objections known through their state medical societies. As a result, in 1920, the AMA’s House of Delegates formally voted to reverse its support, and instead opposed the initiatives.
While the AMA has been a staunch opponent ever since, that may be changing. Though the AMA has opposed national health insurance for over a century, doctors have much to gain from it. The image of the self-employed family doctor who makes house calls is virtually an anachronistic image. Today, around four out of five physicians – 77.6 percent – work for corporations. Historically, doctors have expressed concern over government oversight and interference. More and more, though, physicians’ reality is that they now live under commercial insurance oversight and interference. Unlike elected officials for whom Americans vote and whose salaries are set and paid transparently from public funds, doctors have no say over who runs private insurance companies and how they are operated.
A survey of doctors conducted by the Chicago Medical Society found that 66.8 percent had favorable views of a single-payer system.
The doctors most active in support of Improved Medicare for All are the leaders and 25,000 members of Physicians for a National Health Program (PNHP). They have provided a clear and steady voice on the issue since their founding in 1987. In part because of PNHP’s sustained effort, doctors seem to be moving toward support for Improved Medicare for All. A survey of doctors conducted by the Chicago Medical Society found that 66.8 percent had favorable views of a single-payer system. In fact, when asked to choose between Medicare for All and an improved Affordable Care Act (colloquially known as Obamacare), the doctors chose Medicare for All by two to one!
The increasing support among doctors for Improved Medicare for All is likely in large part a response to how vexing and inadequate the current system is for all participants, including doctors. The increasing support for Improved Medicare for All may also reflect a more diversified pool of physicians. When Medicare was enacted in 1965, doctors were overwhelmingly white men, who tended to identify as Republicans. Accordingly, the AMA gave the majority of its campaign contributions to Republican candidates. Ninety-four percent of the medical students at that time were men. Only 2.5 percent of practicing physicians were African-American, generally having been trained in segregated settings. An even tinier 0.2 percent of medical students were Hispanic or indigenous at that time.
In contrast, women comprised 55.1 percent of the entering classes in accredited medical schools across the country for academic year 2024-25. That was the sixth year in a row that women made up the majority of medical school students. They comprised 54.9 percent of total enrollment. African-Americans comprised 10.3 percent of total enrollment, and Hispanics, 12.3 percent. In 2021, more than one out of four surgeons and other physicians – 26.5 percent – were foreign-born.
Led by PNHP, advocates of Improved Medicare for All must have a focused strategy geared toward physicians to solidify the support of doctors, with the goal of converting the AMA from a force in opposition to a force in support. With a focus on improving the quality of medical practice while compensating its providers adequately, along with improving Medicare and extending it to everyone, the goal for supporters of Improved Medicare for All should be to convince doctors to become a force for its enactment.
Physicians have been perhaps the hardest opponent to overcome in the past, because of the extremely close relationship they have had historically with their patients, who rely on their doctors when their lives are literally on the line. When doctors give patients advice, those words carry enormous weight, even if the advice is about whether universal health insurance would lead to better or worse health care. If physicians tell their patients the proposed legislation will harm their practice and therefore their patients’ health care, that is influential.
While attaining the support of the AMA can likely be achieved with concerted effort particularly and primarily by physicians themselves and would be extremely valuable, that support is not essential. After all, Medicare was enacted despite the AMA’s strong opposition. Moreover, while doctors historically have been extremely influential with their patients about health policy, and they remain so, the need to change doctors because they are no longer in-network and the increasing reliance on teams of healthcare providers, including nurses, nurse practitioners, and physicians’ assistants, have increased the influence of nonphysician providers.
Nurses are another key group, and fortunately they have been leading the fight for Improved Medicare for All. Unlike the AMA, National Nurses United (NNU), the largest professional association of registered nurses, with 225,000 members nationwide, has been advocating for Improved Medicare for All for decades, with determination and effectiveness.
Following the lead of the AMA, the American Hospital Association (AHA), which represents nearly 5,000 hospitals, has opposed the last century of efforts to enact national health insurance. Improved Medicare for All, with its guaranteed payments to providers, its ability to incentivize healthcare providers to practice where the need is highest, and its ability to use tax dollars to subsidize the most at-risk hospitals, is a solution. Though the AHA does not yet support Improved Medicare for All, advocates may be able to persuade individual hospital administrators and, over time, the AHA itself to recognize the advantages of Improved Medicare for All and join the effort.
Another powerful group that started as supportive in the early years but then quickly switched were employers, who worried about the cost to them and the potential government interference in what they considered their independent authority. Though they still oppose it today, they might be persuaded of its value to them because healthcare costs have grown so substantially, and the lack of universal national health insurance puts them at a competitive disadvantage to their foreign counterparts.
Most companies are primarily focused on the cost of health care and, therefore, should be open to Improved Medicare for All, if they are convinced it would reduce their costs. There are some industries, though, that have an overwhelmingly strong stake in the current inefficient, costly system. Pharmaceutical manufacturers, pharmacists, and their associations have been aggressive parts of the opposition from the beginning. Another opponent has been the insurance industry. Neither pharmaceutical companies nor health insurance companies are likely to be convinced to end their opposition to Improved Medicare for All. Pharmaceutical companies take advantage of the bloated system to make extraordinary profits. Under Improved Medicare for All, the pharmaceutical industry will still make profits. Price gouging, however, will stop. Similarly, health insurance companies, for which Improved Medicare for All is an existential threat, will fight as hard as possible.
Health care is a matter of life and death for virtually all of us at some point in our lives.
Those monied interests must be defeated – no easy task given their vast resources. As powerful as they are, history shows that they can be beaten. They can be defeated, if the electorate is engaged and determined. The way to defeat those stakeholders that cannot be convinced of the benefits of Improved Medicare for All is with ongoing motivated action at both the grassroots and grasstops levels. The strong antipathy to commercial health insurance, exposed by the murder of the UnitedHealthcare CEO, reveals that the public may be ready to fight persistently, relentlessly, and effectively for accessible, affordable, high-quality health care for all.
History reveals that Americans’ support for national health insurance is generally widespread and strong at the start of the public push, likely because the need is so great, but that support can easily be shaken. Polling shows that support for Improved Medicare for All is susceptible to opposition messaging that invokes fear of loss and danger. That is not surprising, because health care is a matter of life and death for virtually all of us at some point in our lives. The challenge will be to keep people motivated and not swayed by half-truths and lies, which history demonstrates opponents are willing to deploy. The uber-wealthy want to defeat anything that will increase their costs and reduce their wealth, even by a little. They will seek to scare the American people to retain the status quo. Obviously, fear of failing to obtain adequate health care when needed is an extremely powerful fear that can be exploited.
A key player in maintaining the active support of the American people is organized labor. Studies show that union members are more likely to vote, to volunteer for candidates, and to be influenced by their union leadership in political matters generally. Importantly, they remain a counterweight to the corrosive power of self-interested billionaires and multinational corporations. While organized labor can be counted on, it does have concerns that should be addressed. These include the fact that in negotiating for the generous healthcare plans their members enjoy, they had to trade away current compensation. Moreover, some workers involved in the administration of the current wasteful system will lose employment as a result of the greater efficiency of Improved Medicare for All. Both of those concerns should be addressed as part of the fight for Improved Medicare for All. Both issues are discussed in greater detail in the next chapter, which focuses on the counterattack.
A crucial part to winning the fight for Improved Medicare for All is extremely careful messaging to strengthen the commitment and effort of supporters and to win over those who may be skeptical.
As part of the effort to enact Improved Medicare for All, advocates must be an active part of the fight for workers’ rights to unionize and build union strength. In addition, advocates must employ a careful strategy, in addition to relying on unions, to convince the American people to fight for Improved Medicare for All.
Using the right messaging is key. While the majority of Americans favor Improved Medicare for All, polling indicates that the support can be shaken simply by the way the issue is framed. For example, while 63 percent have a positive reaction to the phrases “Medicare for all,” and “Universal health coverage,” that reaction drops to 49 percent when the phrase is “Single-payer health insurance system,” and 43 percent when the proposal is called “Socialized medicine.” People’s opinions can change dramatically depending on what is emphasized. When those polled are told that Medicare for All will increase their taxes, support drops to just 37 percent. When, though, they are told there will be no premiums and out-of-pocket costs will be reduced, support increases to 67 percent. Indeed, when those polled are told that the proposal guarantees health care as a right for all, support jumps to 71 percent.
This means that a crucial part to winning the fight for Improved Medicare for All is extremely careful messaging to strengthen the commitment and effort of supporters and to win over those who may be skeptical. While the facts are important and strongly on the side of advocates of Improved Medicare for All, history teaches that winning must include effective messaging that is repeated frequently.
Careful strategizing and messaging are especially crucial with respect to older Americans who are Medicare beneficiaries or are about to become so. Seniors have, on average, the greatest need for health care and are the most reliable voters. History shows that they generally pay keen attention to conversations about retirement security and health care. Older Americans were key to the enactment of Social Security in 1935 and its improvements ever since. They were also key to the enactment of Medicare in 1965. History also reveals, though, that the deployment of fear tactics targeted toward seniors can be effective, unfortunately. Consequently, it is vital that proponents of national health insurance have a systematic strategy with respect to seniors, including careful messaging.
In particular, the name Medicare for All may be a two-edged sword. The name presumably tests so well because Medicare, having completed its 61st year, is widely known and understood. Virtually all Americans know people who currently are covered by Medicare and appropriately expect to be covered themselves one day, if they aren’t currently. Consequently, it is harder to demonize as something scary, foreign, and potentially dangerous.
As important as the enactment of Medicare was, both in its own right and as a first big step toward Improved Medicare for All, its creation established a part of the population that might believe that they have something to lose by its expansion to others. Opponents can and have played on the fear that expanding Medicare to the entire population will dilute it and endanger it. For this reason, it may be prudent to always call the proposal, as this book does, Improved Medicare for All.
Starting with the word, “improved” subtly emphasizes that it will benefit those currently on Medicare. The improvements make the proposal a winner for current beneficiaries. It will eliminate all of their out-of-pocket costs. Its long-term care coverage will be a lifesaver for one out of every three seniors and their families. That coverage of long-term care will end the need for seniors to spend all of their assets to qualify for Medicaid and the care they need. Instead, it will allow seniors to pass on whatever savings they have accumulated to their children and grandchildren. Moreover, simply the knowledge of that coverage will provide everyone with greater peace of mind.
For those who today have traditional Medicare, Improved Medicare for All will provide them with hearing, vision, and dental services. And it will free everyone from the complicated sign-up process that current Medicare enrollees must wade through for prescription drug coverage, Medigap coverage, and, for increasing numbers, the erroneously-named Medicare Advantage. In that regard, though, supporters must have a strategy for those who are enrolled in Medicare Advantage. The ending of Medicare Advantage is particularly challenging to message, because it is extremely popular at least until people get seriously ill, when its extra benefits are of less concern and its narrow network of providers and deny/delay tactics are life-threatening. How to message Medicare Advantage, as well as messaging more generally to seniors, is dealt with in greater detail in the next chapter. The basic point, though, is that messaging specifically aimed at reassuring and enlisting seniors must be a key part of a winning strategy.
Fundamentally, advocates must be astute about employing the most effective messaging. The issue should be constantly polled and the messaging refined, as part of an overarching strategy and game plan. The bottom line, though, is that a winning strategy must include careful messaging that is snappy and compelling, but brief. The messaging must be used repeatedly, consistently, and widely.