

SUBSCRIBE TO OUR FREE NEWSLETTER
Daily news & progressive opinion—funded by the people, not the corporations—delivered straight to your inbox.
5
#000000
#FFFFFF
To donate by check, phone, or other method, see our More Ways to Give page.
Daily news & progressive opinion—funded by the people, not the corporations—delivered straight to your inbox.

"It is well past time that the United States joins the rest of the industrialized world and treats healthcare as a right, not a privilege, by improving traditional Medicare and expanding it to everyone."
News that top Medicare Advantage insurers are moving to cut benefits and drop some plans entirely in a bid to boost their profitability came as no surprise to critics of the for-profit US health insurance system, which enriches giant companies and their executives while leaving tens of millions of people in the lurch.
In recent public remarks, executives at Humana and UnitedHealthcare—two of the largest Medicare Advantage insurers in the US—have indicated that the companies plan to exit certain geographic markets and implement other changes deemed necessary to drive "margin expansion," corporate-speak for profits. The changes by the two companies are expected to impact more than a million seniors who receive coverage through the insurers' Medicare Advantage plans, which are privately run but funded by taxpayer dollars.
Wendell Potter, president of the Center for Health and Democracy and a former Cigna executive, told Common Dreams that companies like Humana and UnitedHealthcare "have long made clear they answer to their shareholders, not those they insure."
"These companies are not really in the healthcare business, they are in the business of making money for their shareholders and their executives," said Potter, who now advocates for a Medicare for All system. "They will cut any corner, deny any care, and cut any patient if it helps increase their bottom line."
UnitedHealth Group, UnitedHealthcare's parent company, reported $5.5 billion in profit during the second quarter of 2026, up from $3.4 billion the same time last year. Humana reported $694 million in second-quarter profits.
Recent research led by Mark Meiselbach, a healthcare economist at Johns Hopkins University estimates that "approximately one in 10 beneficiaries in HMO or PPO Medicare Advantage plans will be forced to disenroll from their current plan due to their plan exiting the market" this year. That amounts to around 3 million seniors who will be forced to find a different plan or switch to traditional Medicare during the open enrollment period, which begins next month.
Nancy Altman, president of Social Security Works and author of The Road to Medicare for All: A Call to Action, told Common Dreams that "misleadingly-named Medicare 'Advantage,' together with all private health insurance, is why our nation’s healthcare system is so dysfunctional."
"It mixes healthcare with the motive to make a profit, resulting in the most expensive system in the industrialized world with the worst health outcomes," said Altman. "The recent announcements by UnitedHealthcare and Humana that they plan to exit markets and cut benefits is just one symptom of the dysfunction."
"It is well past time that the United States joins the rest of the industrialized world and treats healthcare as a right, not a privilege, by improving traditional Medicare and expanding it to everyone," said Altman.
A Congressional Budget Office (CBO) analysis published in July found that federal spending per Medicare Advantage enrollee "is projected to be 7% higher, on average," than spending on traditional Medicare over the next 10 years.
The Committee for a Responsible Federal Budget noted that the CBO's analysis "suggests the federal government will spend about $1 trillion on MA overpayments over the next decade." Medicare Advantage plans are notorious for making patients appear sicker than they actually are, reaping larger federal payments.
President Donald Trump pledged during remarks earlier this week to the Republican midterm convention that his administration would "end all payments to big health insurance companies."
But Potter noted that Trump's administration is set to shell out over $13 billion in payments to Medicare Advantage plans this year along.
"If Trump were serious about lowering healthcare costs," Potter told Common Dreams, "he'd break up the monopolies and the for-profit healthcare system."

Humana said it is exiting plans covering roughly 600,000 seniors to "drive the intended margin expansion."
Two of the largest Medicare Advantage insurers in the US, UnitedHealthcare and Humana, have signaled in recent days that they plan to exit certain "underperforming" markets and curb benefits in an effort to boost their bottom lines, a strategy that's expected to kick more than a million seniors from their coverage.
On Thursday, Axios cited an analyst note published earlier this week indicating that UnitedHealthcare "has dropped around 13% of plans offered across 18 states." Healthcare Dive reported that the company "expects to end 2026 with up to 1.1 million fewer MA members than it had last year."
"UnitedHealthcare—the largest MA insurer in the US—offered plans in one fewer state and 109 fewer counties this year, cut allowances for certain over-the-counter health and wellness items, and prioritized plan designs with more limited provider networks," Healthcare Dive noted. "The company also shifted commissions to brokers to incentivize enrollment in more profitable plans."
As for Humana, the company's chief financial officer said during an earnings call in late July that its exit from certain markets and dropping of specific plans would "impact approximately 600,000 members" as the firm implements "the changes necessary to drive the intended margin expansion."
Seniors who lose their MA plans in response to the insurance giants' moves will have to either find a new plan during open enrollment, which begins next month, or switch to traditional Medicare. MA plans currently cover more than half of all eligible Medicare beneficiaries.
Mark Meiselbach, a healthcare economist at Johns Hopkins University, has estimated that nearly 3 million people enrolled in MA will be forced to switch coverage this year due to insurers canceling their plans—which Meiselbach describes as "forced disenrollments."
“For most enrollees, they will likely be able to still find a comparable MA plan,” Meiselbach told Investopedia last week. “However, no two plans are exactly the same. They may still have access to their same primary care provider, but have to undergo new prior authorization for a medication or lose a supplemental benefit they relied on.”
The companies laid out their profit-boosting strategies months after the Trump administration provided a substantial payment increase to Medicare Advantage plans, which are run by private companies and funded by taxpayer dollars. MA companies are notorious for denying necessary care and overbilling the federal government through practices such as upcoding, whereby patients are made to appear sicker than they are to reap a larger federal payment.
"President Trump, Dr. Oz, and leaders in Congress have talked a big game for two years about reining in waste, fraud, and abuse, but instead they increased insurer payment by multiple times more than what the administration originally proposed," Anthony Wright, executive director of Families USA, said in response to the April payment hike.
During his remarks to the GOP midterm convention on Wednesday, President Donald Trump vowed to "stop all government payments to big insurance companies"—an apparently inadvertent call for the elimination of privately run Medicare Advantage plans, which received over $534 billion from the federal government last year.

The pessimistic view that we are moving in the wrong direction sees only the waves at the surface. It misses the subterranean tremors underneath. If we fight, we can win.
As policy-wise and popular as Improved Medicare for All is, the nation may appear to be as far away from enacting Improved Medicare for All as possible. During his first term, Trump did what he could to accelerate the privatization of Medicare. Unfortunately, his thumb on the scale in favor of privatized Medicare is not only back, but is on steroids.
Adding to the sense that the nation may be as far away from Improved Medicare for All as possible, the Republicans enacted legislation that is projected to cause 15 million people to lose their health insurance. Adding to the sense that we are nowhere near enacting Improved Medicare for All, the two prior presidential elections, in 2016 and 2020, saw Senator Bernie Sanders (I-Vt.) and Senator Elizabeth Warren (D-Mass.), two leading champions of Medicare for All, lose in the primary to the more centrist candidate Hillary Clinton, in 2016, and Joe Biden, in 2020. Trump defeated Clinton and won a second term in 2024 against Vice President Kamala Harris. Though Harris did not mention the fact in her presidential campaign, she was an original cosponsor of the Sanders-authored Medicare for All Act.
Trump’s election to a second term, the Republican control of Congress (as these words are written), and a Supreme Court with two-thirds of the justices who are acting as Trump advocates rather than independent jurists appear to suggest that the nation is moving away from national health insurance. But it is crucial to recognize that today is only a snapshot in time. The pessimistic view that we are moving in the wrong direction sees only the waves at the surface. It misses the subterranean tremors underneath. The Republican cuts to health insurance are already putting a strain on rural and inner-city hospitals, as well as nursing homes. The nation is seeing hospitals close as a result of the enactment. Their closure, in turn, strains even those hospitals and nursing homes not directly affected by the cuts.
Improved Medicare for All won’t magically become a reality. It will take all of us who support it to fight for it, in small and large ways.
With the cost of health care rising and, with it, increased insecurity, a majority of the electorate are concluding that the nation is moving in the wrong direction. Perhaps even more significantly, it will become clearer and clearer that the current path is unsustainable.
Importantly, two action-forcing events requiring Congressional legislation are on the horizon. Social Security and Medicare Part A, by law, can only pay benefits if they have sufficient dedicated revenue to cover their costs. To avoid an automatic across-the-board reduction of around 20 percent of the monthly Social Security benefits received by more than 70 million beneficiaries, and to avoid hospitals no longer being reimbursed, Congress must act. However the precise dates shift over the next few years, Congress unquestionably will have to act in the next half decade or so, before the revenue is insufficient to continue to pay full benefits.
Those action-forcing events provide an opportunity. Because those action-forcing events will result in must-pass legislation, provisions that expand Medicare, as well as Social Security, could be included. To make that a reality, though, it is essential that those who support Improved Medicare for All are fully prepared.
Improved Medicare for All won’t magically become a reality. It will take all of us who support it to fight for it, in small and large ways. The wonderful news is that determined activists are currently working hard to make Improved Medicare for All the law of the land. Building a winning coalition and other steps are already underway.
It is imperative that a winning coalition is built strong enough to defeat those who will fight against Improved Medicare for All. Physicians have been extremely active politically since the United States first started to seriously debate universal health insurance at the start of the twentieth century. Initially, the American Medical Association, whose members in 1910 comprised more than half the doctors in the nation, endorsed the legislation under consideration. Individual doctors, however, strenuously objected and made those objections known through their state medical societies. As a result, in 1920, the AMA’s House of Delegates formally voted to reverse its support, and instead opposed the initiatives.
While the AMA has been a staunch opponent ever since, that may be changing. Though the AMA has opposed national health insurance for over a century, doctors have much to gain from it. The image of the self-employed family doctor who makes house calls is virtually an anachronistic image. Today, around four out of five physicians – 77.6 percent – work for corporations. Historically, doctors have expressed concern over government oversight and interference. More and more, though, physicians’ reality is that they now live under commercial insurance oversight and interference. Unlike elected officials for whom Americans vote and whose salaries are set and paid transparently from public funds, doctors have no say over who runs private insurance companies and how they are operated.
A survey of doctors conducted by the Chicago Medical Society found that 66.8 percent had favorable views of a single-payer system.
The doctors most active in support of Improved Medicare for All are the leaders and 25,000 members of Physicians for a National Health Program (PNHP). They have provided a clear and steady voice on the issue since their founding in 1987. In part because of PNHP’s sustained effort, doctors seem to be moving toward support for Improved Medicare for All. A survey of doctors conducted by the Chicago Medical Society found that 66.8 percent had favorable views of a single-payer system. In fact, when asked to choose between Medicare for All and an improved Affordable Care Act (colloquially known as Obamacare), the doctors chose Medicare for All by two to one!
The increasing support among doctors for Improved Medicare for All is likely in large part a response to how vexing and inadequate the current system is for all participants, including doctors. The increasing support for Improved Medicare for All may also reflect a more diversified pool of physicians. When Medicare was enacted in 1965, doctors were overwhelmingly white men, who tended to identify as Republicans. Accordingly, the AMA gave the majority of its campaign contributions to Republican candidates. Ninety-four percent of the medical students at that time were men. Only 2.5 percent of practicing physicians were African-American, generally having been trained in segregated settings. An even tinier 0.2 percent of medical students were Hispanic or indigenous at that time.
In contrast, women comprised 55.1 percent of the entering classes in accredited medical schools across the country for academic year 2024-25. That was the sixth year in a row that women made up the majority of medical school students. They comprised 54.9 percent of total enrollment. African-Americans comprised 10.3 percent of total enrollment, and Hispanics, 12.3 percent. In 2021, more than one out of four surgeons and other physicians – 26.5 percent – were foreign-born.
Led by PNHP, advocates of Improved Medicare for All must have a focused strategy geared toward physicians to solidify the support of doctors, with the goal of converting the AMA from a force in opposition to a force in support. With a focus on improving the quality of medical practice while compensating its providers adequately, along with improving Medicare and extending it to everyone, the goal for supporters of Improved Medicare for All should be to convince doctors to become a force for its enactment.
Physicians have been perhaps the hardest opponent to overcome in the past, because of the extremely close relationship they have had historically with their patients, who rely on their doctors when their lives are literally on the line. When doctors give patients advice, those words carry enormous weight, even if the advice is about whether universal health insurance would lead to better or worse health care. If physicians tell their patients the proposed legislation will harm their practice and therefore their patients’ health care, that is influential.
While attaining the support of the AMA can likely be achieved with concerted effort particularly and primarily by physicians themselves and would be extremely valuable, that support is not essential. After all, Medicare was enacted despite the AMA’s strong opposition. Moreover, while doctors historically have been extremely influential with their patients about health policy, and they remain so, the need to change doctors because they are no longer in-network and the increasing reliance on teams of healthcare providers, including nurses, nurse practitioners, and physicians’ assistants, have increased the influence of nonphysician providers.
Nurses are another key group, and fortunately they have been leading the fight for Improved Medicare for All. Unlike the AMA, National Nurses United (NNU), the largest professional association of registered nurses, with 225,000 members nationwide, has been advocating for Improved Medicare for All for decades, with determination and effectiveness.
Following the lead of the AMA, the American Hospital Association (AHA), which represents nearly 5,000 hospitals, has opposed the last century of efforts to enact national health insurance. Improved Medicare for All, with its guaranteed payments to providers, its ability to incentivize healthcare providers to practice where the need is highest, and its ability to use tax dollars to subsidize the most at-risk hospitals, is a solution. Though the AHA does not yet support Improved Medicare for All, advocates may be able to persuade individual hospital administrators and, over time, the AHA itself to recognize the advantages of Improved Medicare for All and join the effort.
Another powerful group that started as supportive in the early years but then quickly switched were employers, who worried about the cost to them and the potential government interference in what they considered their independent authority. Though they still oppose it today, they might be persuaded of its value to them because healthcare costs have grown so substantially, and the lack of universal national health insurance puts them at a competitive disadvantage to their foreign counterparts.
Most companies are primarily focused on the cost of health care and, therefore, should be open to Improved Medicare for All, if they are convinced it would reduce their costs. There are some industries, though, that have an overwhelmingly strong stake in the current inefficient, costly system. Pharmaceutical manufacturers, pharmacists, and their associations have been aggressive parts of the opposition from the beginning. Another opponent has been the insurance industry. Neither pharmaceutical companies nor health insurance companies are likely to be convinced to end their opposition to Improved Medicare for All. Pharmaceutical companies take advantage of the bloated system to make extraordinary profits. Under Improved Medicare for All, the pharmaceutical industry will still make profits. Price gouging, however, will stop. Similarly, health insurance companies, for which Improved Medicare for All is an existential threat, will fight as hard as possible.
Health care is a matter of life and death for virtually all of us at some point in our lives.
Those monied interests must be defeated – no easy task given their vast resources. As powerful as they are, history shows that they can be beaten. They can be defeated, if the electorate is engaged and determined. The way to defeat those stakeholders that cannot be convinced of the benefits of Improved Medicare for All is with ongoing motivated action at both the grassroots and grasstops levels. The strong antipathy to commercial health insurance, exposed by the murder of the UnitedHealthcare CEO, reveals that the public may be ready to fight persistently, relentlessly, and effectively for accessible, affordable, high-quality health care for all.
History reveals that Americans’ support for national health insurance is generally widespread and strong at the start of the public push, likely because the need is so great, but that support can easily be shaken. Polling shows that support for Improved Medicare for All is susceptible to opposition messaging that invokes fear of loss and danger. That is not surprising, because health care is a matter of life and death for virtually all of us at some point in our lives. The challenge will be to keep people motivated and not swayed by half-truths and lies, which history demonstrates opponents are willing to deploy. The uber-wealthy want to defeat anything that will increase their costs and reduce their wealth, even by a little. They will seek to scare the American people to retain the status quo. Obviously, fear of failing to obtain adequate health care when needed is an extremely powerful fear that can be exploited.
A key player in maintaining the active support of the American people is organized labor. Studies show that union members are more likely to vote, to volunteer for candidates, and to be influenced by their union leadership in political matters generally. Importantly, they remain a counterweight to the corrosive power of self-interested billionaires and multinational corporations. While organized labor can be counted on, it does have concerns that should be addressed. These include the fact that in negotiating for the generous healthcare plans their members enjoy, they had to trade away current compensation. Moreover, some workers involved in the administration of the current wasteful system will lose employment as a result of the greater efficiency of Improved Medicare for All. Both of those concerns should be addressed as part of the fight for Improved Medicare for All. Both issues are discussed in greater detail in the next chapter, which focuses on the counterattack.
A crucial part to winning the fight for Improved Medicare for All is extremely careful messaging to strengthen the commitment and effort of supporters and to win over those who may be skeptical.
As part of the effort to enact Improved Medicare for All, advocates must be an active part of the fight for workers’ rights to unionize and build union strength. In addition, advocates must employ a careful strategy, in addition to relying on unions, to convince the American people to fight for Improved Medicare for All.
Using the right messaging is key. While the majority of Americans favor Improved Medicare for All, polling indicates that the support can be shaken simply by the way the issue is framed. For example, while 63 percent have a positive reaction to the phrases “Medicare for all,” and “Universal health coverage,” that reaction drops to 49 percent when the phrase is “Single-payer health insurance system,” and 43 percent when the proposal is called “Socialized medicine.” People’s opinions can change dramatically depending on what is emphasized. When those polled are told that Medicare for All will increase their taxes, support drops to just 37 percent. When, though, they are told there will be no premiums and out-of-pocket costs will be reduced, support increases to 67 percent. Indeed, when those polled are told that the proposal guarantees health care as a right for all, support jumps to 71 percent.
This means that a crucial part to winning the fight for Improved Medicare for All is extremely careful messaging to strengthen the commitment and effort of supporters and to win over those who may be skeptical. While the facts are important and strongly on the side of advocates of Improved Medicare for All, history teaches that winning must include effective messaging that is repeated frequently.
Careful strategizing and messaging are especially crucial with respect to older Americans who are Medicare beneficiaries or are about to become so. Seniors have, on average, the greatest need for health care and are the most reliable voters. History shows that they generally pay keen attention to conversations about retirement security and health care. Older Americans were key to the enactment of Social Security in 1935 and its improvements ever since. They were also key to the enactment of Medicare in 1965. History also reveals, though, that the deployment of fear tactics targeted toward seniors can be effective, unfortunately. Consequently, it is vital that proponents of national health insurance have a systematic strategy with respect to seniors, including careful messaging.
In particular, the name Medicare for All may be a two-edged sword. The name presumably tests so well because Medicare, having completed its 61st year, is widely known and understood. Virtually all Americans know people who currently are covered by Medicare and appropriately expect to be covered themselves one day, if they aren’t currently. Consequently, it is harder to demonize as something scary, foreign, and potentially dangerous.
As important as the enactment of Medicare was, both in its own right and as a first big step toward Improved Medicare for All, its creation established a part of the population that might believe that they have something to lose by its expansion to others. Opponents can and have played on the fear that expanding Medicare to the entire population will dilute it and endanger it. For this reason, it may be prudent to always call the proposal, as this book does, Improved Medicare for All.
Starting with the word, “improved” subtly emphasizes that it will benefit those currently on Medicare. The improvements make the proposal a winner for current beneficiaries. It will eliminate all of their out-of-pocket costs. Its long-term care coverage will be a lifesaver for one out of every three seniors and their families. That coverage of long-term care will end the need for seniors to spend all of their assets to qualify for Medicaid and the care they need. Instead, it will allow seniors to pass on whatever savings they have accumulated to their children and grandchildren. Moreover, simply the knowledge of that coverage will provide everyone with greater peace of mind.
For those who today have traditional Medicare, Improved Medicare for All will provide them with hearing, vision, and dental services. And it will free everyone from the complicated sign-up process that current Medicare enrollees must wade through for prescription drug coverage, Medigap coverage, and, for increasing numbers, the erroneously-named Medicare Advantage. In that regard, though, supporters must have a strategy for those who are enrolled in Medicare Advantage. The ending of Medicare Advantage is particularly challenging to message, because it is extremely popular at least until people get seriously ill, when its extra benefits are of less concern and its narrow network of providers and deny/delay tactics are life-threatening. How to message Medicare Advantage, as well as messaging more generally to seniors, is dealt with in greater detail in the next chapter. The basic point, though, is that messaging specifically aimed at reassuring and enlisting seniors must be a key part of a winning strategy.
Fundamentally, advocates must be astute about employing the most effective messaging. The issue should be constantly polled and the messaging refined, as part of an overarching strategy and game plan. The bottom line, though, is that a winning strategy must include careful messaging that is snappy and compelling, but brief. The messaging must be used repeatedly, consistently, and widely.

Predictably, centrists are pushing the public option and “anything-but-single-payer” solutions before the midterms. Nothing short of taking control of the healthcare system and running it in the interest of the people instead of in the interest of profit will heal this nation.
On July 5, 1852, Frederick Douglass addressed the Rochester Ladies’ Anti-Slavery Society with an oration called, “What to the Slave Is the Fourth of July?” In 1852, the United States was a young country, only 76 years old, and given its youth, Douglass held out hope for the country that put him and 3 million Black men, women, and children in chains. He called Congress and judges “inhuman, disgraceful, and scandalous.” He accused the church of being the “bulwark of American slavery, and the shield of American slave-hunters.” Still, he held out hope. He admired the rebels of the American Colonies, respected their grit to side with the oppressed against the oppressor. He did not despair for America.
This year, as we celebrate the nation’s 250th anniversary, we find ourselves in dark times. We are heirs to a political system willing to promote wars, sanctions, occupation, slavery, and genocide around the globe, while accepting the mass suffering of a healthcare system that keeps many in chains in our own country. Violence abroad and austerity at home are part of the same ideological structure. Despair is understandable, but not inevitable.
On this 250th anniversary of the Declaration of Independence, we declare it is time for the people to rise up, organize, take control of the healthcare system, and run it in the interest of the people instead of in the interest of profit. It is time we declare our independence from the medical-industrial complex keeping us in chains.
What is the medical-industrial complex? A sprawling alliance of insurance companies and middlemen stealing from the public coffers, pharmaceutical companies holding us hostage, private equity and venture capital owning the delivery of care, profit-generating “nonprofit” health and hospital systems, compromised academic centers and endowed non-governmental organizations, unprincipled medical organizations that choose expediency over patients, and all politicians who accept financial contributions to work for the industry instead of for the people. Their profits depend on keeping healthcare commodified and the rest of us in chains.
Historic public support for a national health program, free from insurance companies and financed through progressive taxes, presents us with a new opening for National Single Payer Improved Medicare for All, free from profit.
Our lives depend on declaring our independence from their profits.
Historic public support for a national health program, free from insurance companies and financed through progressive taxes, presents us with a new opening for National Single Payer Improved Medicare for All, free from profit, guaranteeing all necessary medical coverage for everyone through community-governed delivery, permanently resolving our healthcare crises, lowering costs, and ending medical debt.
But instead of bold proposals, corporate Democrats and their allies are working overtime to come up with “anything-but-single-payer” solutions. Derailment by such Democrats might be a larger challenge than barriers posed by the rest of the medical-industrial complex.
Senate Finance Committee ranking member Ron Wyden (D-Ore.), and 11 Senate Democrats, announced a new initiative to lower the cost of healthcare and improve health coverage for American families. What is this “bold, meaningful change the American people seek”? First, blame Republicans for cost increases (as if Democrats were not also guilty); make healthcare simpler for families by keeping health insurance corporations still in charge of our healthcare; and then take on corporate greed by creating flimsy new guardrails, because naturally, corporations will suddenly decide to play by the rules!
The Center for Health and Democracy, which usually provides credible analysis, went off the rails, putting their money behind “Medicare by Choice,” a warmed-over version of the public option, which allows everyone the option of purchasing traditional Medicare regardless of age, and even allowing employers to select Medicare by Choice as their employees’ workplace benefit. Sadly (and somewhat opportunely) we have a natural experiment that shows us just how well a public option (i.e., traditional Medicare) would fare in the marketplace (i.e., Medicare Advantage). Spoiler alert: not well at all.
Any version of the public option would fail to reap administrative savings or control costs necessary to provide comprehensive universal coverage. A public option would preserve the Machiavellian system of thousands of private insurance plans; Medicaid; CHIP; the federal exchanges; Medicare Part A, B, and Dl MediGap; and Medicare Advantage—a hodgepodge system that has failed to either provide necessary health coverage for all or control costs.
A public option would add even greater complexity to this overwhelmingly complex system. Importantly, a public option would not lead to single payer, as magical thinking would have you believe, but toward a jaded triaging of patients according to their profitability, with profitable individuals going to the private plans and the unprofitable, chronically ill patients shunted to the public plan.
A profit-driven system cannot be repaired with incremental fixes. We have the hard facts from a century of failed attempts to prove it. Derailments offer Democrats an off-ramp in 2028, away from National Single Payer Improved Medicare for All, free from profit. These and similar proposals are guaranteed to set the burgeoning healthcare movement back another 15 years, just like the Affordable Care Act. In 2009, even the Congressional Progressive Caucus favored the public option over single payer. It makes no sense to replay this failure again.
These are the four bold demands we make to declare our independence from the medical-industrial complex:
If you wish to declare your independence from the medical-industrial complex, sign the Declaration as an individual or as an organization. We will inform your member of Congress that a constituent has signed the Declaration. Then join us October 14, 2026, for a virtual National Town Hall to hear how we will achieve our demands.
Let us not squander this opportunity to put national single payer on the nation’s agenda. Frederick Douglass did not despair, "The doom of slavery is certain. I therefore, leave off where I began, with hope.” Let us likewise use this opportunity to build an uncompromising movement capable of confronting the medical-industrial complex directly and achieving what we deserve and already pay for: National Single Payer Improved Medicare for All, Free From Profit.

Researchers found prior authorization—which allows insurers to overrule physicians and deny coverage—acts as a “corporate care veto” that drains tens of billions of dollars each year that could go toward patients.
A new report is making the case for ending a widely-hated and sometimes deadly tactic used by for-profit health insurers to deny needed care.
It's called "prior authorization," and it allows health insurance companies to override physicians and decide whether certain care is medically necessary before it is covered.
The policy brief, published Monday by the American Economic Liberties Project (AELP), an anti-monopoly think tank, argues that the system is a massive drag on the US healthcare system, draining doctors of their time, fueling hiring shortages, and—most importantly—worsening treatable health problems for millions of Americans.
"This practice has massive financial and human costs, as I know personally from my family’s own tragic experience,” said the report's author, Hannah Garden-Monheit—a senior fellow at the AELP, whose late father was denied rehab by UnitedHealthcare after cancer forced his leg to be amputated.
"Prior authorization may have started as a narrow cost-control tool," she explained. "But it’s mushroomed into private insurers’ strategy for diverting resources from care toward their own profits. It’s time to ban prior authorization as we know it.”
The report examines how prior authorization went from a tool used sparingly to prevent payment for unnecessary treatments to what Garden-Monheit and co-author, AELP senior healthcare fellow Emma Freer, described as a "corporate care veto."
Around 1 in 5 adults with private insurance report that they or a family member had experienced a coverage denial in the past year, with 28% reporting that it worsened their health problem, according to a June survey from the Commonwealth Fund.
While insurers claim that their decisions to deny care are "evidence-based," the authors say that "in reality, the practice empowers distant corporate entities with a financial conflict of interest to override the professional judgment of physicians with firsthand knowledge of patients’ medical needs."
"There is generally little to no transparency or accountability for these decisions," the authors wrote.
While insurers claim that denials are reviewed by qualified clinicians, one survey from the American Medical Association (AMA) found that only 16% of physicians participating in peer-to-peer reviews reported that the “peer” was often or always qualified.
Garden-Monheit said United denied her father's claim multiple times, first citing his cancer diagnosis—the reason his leg was amputated in the first place—then by claiming that he had made significant enough "progress" that paying for rehab was unnecessary. The "progress" was that he "had figured out how to hop on one leg from his hospital bed to a chair."
Garden-Monheit describes how she, her father, and their care team were forced to navigate a "bureaucratic maze" by United, which ultimately led them to give up.
"At least twice, I learned of a denial only after calling United to check on the status of their request. They hadn’t even bothered with a letter," she said. "While the lines of communication felt frustratingly unpredictable, the answers always led to the same place: 'no.'"
As she explained in a recent op-ed for MS NOW: "My family’s experience wasn’t a one-off glitch. For United, the system was working as designed."
Former United chief medical officer Dr.Archelle Georgiou estimated that across just two Medicare Advantage plans from United and Humana, the companies save an estimated $100 million per year by denying claims that never get appealed. She said that's a "conservative estimate." Across the two plans, 1.75 million people were denied care, even after appeal.
While insurers pad their profits, patients suffer, the researchers found. Among people reporting a prior authorization denial, 41% said it delayed their care and 28% said their health problem worsened, according to the Commonwealth survey.
"My family’s experience wasn’t a one-off glitch. For United, the system was working as designed."
Meanwhile, the AMA survey found that 95% of physicians said that prior authorization delays care, 79% said it causes patients to abandon recommended treatments, and more than 1 in 4 doctors said it has caused a serious adverse event, including hospitalization, permanent impairment, or death.
Denied timely treatments, many patients end up paying for costly and ineffective alternatives that only make their situations worse and cause the costs to increase down the line.
"It was extremely difficult to obtain authorizations for substance abuse treatment when I covered the emergency department as a practicing psychologist," one healthcare professional, identified in the report as Nancy, said. "Other times, in my private practice, I would get authorizations and later experience ‘clawbacks’ where Blue Cross, for example, would decide the treatment was not medically necessary and take back the money already paid."
"It is impossible at times to provide sound ethical treatment and extremely hard to make a living," she said, "when reimbursement rates kept going down, and the insurance companies could take back the money they had already paid for no obvious reason.”
Prior authorization doesn't just deny care to patients. It also creates piles of paperwork for their doctors, taking away precious time that could be dedicated to their care.
The report found that physicians and their teams now spend so much on prior authorization paperwork that it consumes the equivalent of nearly 100,000 full-time physician and advanced practice clinician workloads, plus more than 213,000 clinic staff, costing as much as $32.7 billion each year. If prior authorization were eliminated, they found, it would free up enough capacity to turn a national physician shortage into a surplus.
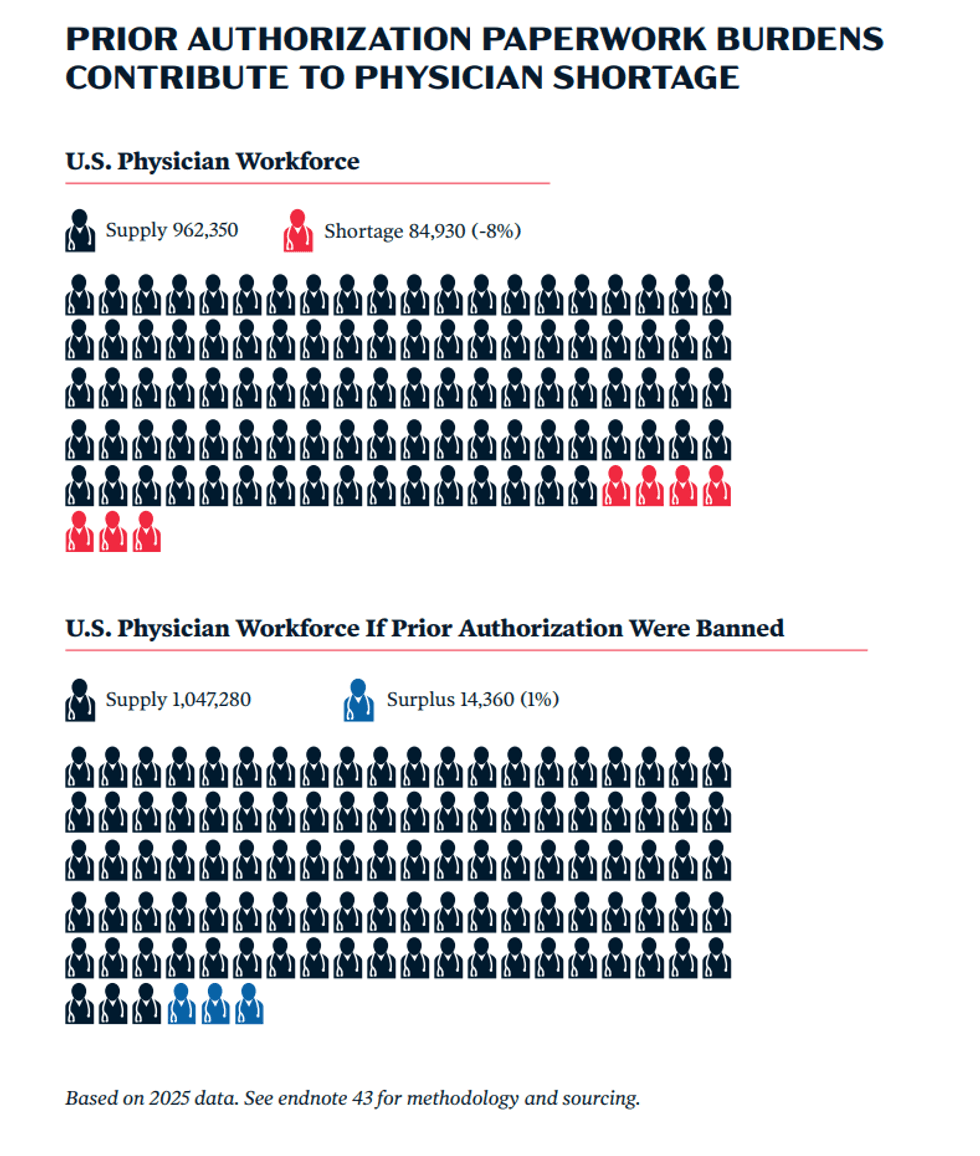 (Graphic: American Economic Liberties Project)
A YouGov poll for AELP found that more than two-thirds of voters in both parties want legislation banning prior authorization outright. But the researchers said both the Trump and Biden administrations have enacted only minor reforms that "fail to address the structural conflict of interest that underpins the corporate care veto strategy."
Meanwhile, the industry is making the denial process even more ruthlessly efficient, increasingly deploying artificial intelligence to deny requests en masse.
According to a 2023 class action lawsuit, United's NaviHealth system used a predictive AI model to determine whether Medicare Advantage patients should receive rehabilitation care despite knowing that the model had a 90% error rate.
President Donald Trump, meanwhile, has expanded prior authorization for traditional Medicare through a pilot program that allows AI models to adjudicate claims in some states. In July, Senate Republicans blocked Democrats' attempt to end the pilot program.
As part of a national pro-AI strategy, Trump has also sought to preempt state laws banning the use of AI to deny care.
The AELP researchers called for a series of reforms to end prior authorization as it currently exists. Among other changes, they said decisions to authorize treatments should be made by independent third parties without the incentive to deny care, that denials must be evidence-based, that the use of AI tools to deny claims should be banned, and that physicians should review patients in person before denying their claims.
“For too long, prior authorization has allowed insurance companies to put profits ahead of patients by overruling doctors and delaying and denying essential care,” Freer said. “This status quo is failing patients, ratcheting up costs, and undermining the basis of effective, expert-informed care. It’s time to end this ‘corporate care veto’ and put medical decisions back where they belong: with patients and their doctors.”

Trump and his allies in Congress have not so much dismantled these programs yet as chipped away at them; if this movement continues unabated, we may be left with the crumbling foundations of programs that were built to last.
There is reason to celebrate Medicare and Medicaid turning 61 years old. Both highly successful programs were signed into law by President Lyndon B. Johnson on July 30, 1965 as a cornerstone of his Great Society agenda. But this year, our celebration is tempered by grave concern over the future of both programs under the Trump regime.
Let’s compare the words of the two presidents:
LBJ:
No longer will older Americans be denied the healing miracle of modern medicine. No longer will illness crush and destroy the savings that they have so carefully put away over a lifetime. No longer will young families see their own incomes, and their own hopes, eaten away simply because they are carrying out their deep moral obligations to their parents.
It’s not possible for us to take care of… Medicaid, Medicare, all these individual things. They can do it on a state basis. You can’t do it on a federal. We have to take care of one thing: military protection. We have to guard the country.
The comparison speaks volumes. One is a leader who understood that the federal government has a crucial role in the protecting the health and well-being of our most vulnerable citizens—including the poor, disabled, and the elderly. The other is a president who claims to support Medicare and then says that the federal government can’t afford it because of his illegal war in Iran. So much for supporting Medicare.
But this goes deeper than Trump’s rhetoric. The Medicare program, like Social Security, is at a pivotal point in its history. The Part A hospital) trust fund must be fortified so that it doesn’t run dry in the 2030s. (There are reasonable solutions that Congress could enact without hurting seniors.) So far, though, we have heard no constructive ideas from Trump.
More urgently, though, the Trump administration is actively undermining the "traditional Medicare" program that LBJ signed into law. The administration has begun a pilot program to use AI bots to determine whether traditional Medicare patients will be covered for procedures their doctors have ordered. This appears to be an attempt to cut costs by erecting obstacles to medically necessary care—with decisions made by bots instead of human beings.
It could be the first step in a scheme to corrupt traditional Medicare and make it more like the privatized Medicare Advantage program run by for-profit insurers, which is a glorified HMO (with frequent denials of care, limited provider networks, and surprise out-of-pocket costs for beneficiaries). Unfortunately, thanks to deceptive but pervasive advertising, Medicare Advantage has now captured more than 51% of the market, leaving traditional Medicare with a shrinking share of enrollees.
The problem is that Medicare Advantage (MA) puts profits over patients. Participating insurance companies have been overbilling the federal government by billions of dollars a year. Ironically, this privatized program was supposed to save taxpayers money. Instead, Medicare Advantage plans cost the government an average of 14% more per patient than traditional Medicare. That translates into an additional $76 billion in federal spending this year alone.
The bottom line: Medicare Advantage puts taxpayers’ money into the hands of large insurance companies while failing to deliver superior or more cost-effective care. It is fair to say that this is not what LBJ had in mind when he created the public Medicare program. (Medicare Advantage arrived—in nascent form—in 1997, after considerable pressure from the insurance industry.)
When we talk about the financial shortfall facing the Medicare program, we must look at Medicare Advantage as an aggravating factor. Reining-in MA would go a long way toward restoring the overall program to fiscal health—along with other commonsense reforms. Unfortunately, the Trump administration has been inconsistent on this issue, initially floating strict curbs on MA overpayments but ultimately rewarding insurance companies with higher payouts.
Traditional Medicare is far from perfect. It should have caps on patients’ out-of-pocket medical costs. It should cover vision, dental, and hearing care. (President Joe Biden attempted to expand coverage in the ill-fated Build Back Better Act.) These are improvements that we have long urged Congress and the White House to enact.
Medicare also faces compound financial challenges—including the overall rise in healthcare costs and soaring prescription drug prices. The Biden administration and Democrats in Congress took a major step in the right direction with the Inflation Reduction Act, which empowered Medicare to negotiate drug prices with Big Pharma. This process is expected to save the government more than $230 billion by 2031.
For the most part, the Trump administration has adhered to the law and continued negotiating with drugmakers—but it also expanded the list of cancer drugs that won’t be eligible for negotiations. The president has largely relied on smoke and mirrors to make it appear that the administration is "tough on Big Pharma," using gimmicks like TrumpRx. Meanwhile, in a move that will make medications less affordable for seniors, the Trump administration has just announced it is ending Biden-era subsidies in the Medicare Part D prescription drug program.
Of course, it’s also Medicaid’s 61st anniversary. The damage that Trump and the Republicans have done to Medicare’s sister program would take up another entire article. Suffice it to say that more than 3 million Americans have already lost health coverage since Trump and the GOP enacted their Big, Ugly Bill, which slashed nearly $1 trillion from Medicaid. (This also hurts older people dually enrolled in both Medicare and Medicaid.) It was correctly labeled the biggest cut in healthcare in US history—to pay for tax cuts largely benefiting the wealthy.
The political right has always been wary of the New Deal and Great Society legacy programs that lifted people out of poverty and provided older and lower-income Americans with basic retirement and health security. Some on the right have outright committed themselves to dismantling these programs, despite their distinguished histories. Trump and his allies in Congress have not so much dismantled these programs yet as chipped away at them under the guise of fighting "fraud and abuse." If this movement continues unabated, we may be left with the crumbling foundations of programs that were built to last, for the good of the American people.

"They want to remove the guarantee of Medicare," one advocate said of the Trump administration's floated plan to automatically enroll seniors in Medicare Advantage.
The Trump administration is considering enacting a policy that would automatically funnel seniors into for-profit Medicare Advantage plans—which critics say would set Medicare on the path to full-scale privatization.
Chris Klomp, the Trump administration's director of Medicare and deputy administrator of the Centers for Medicare and Medicaid Services (CMS), told STAT last month that enrolling seniors in Medicare Advantage (MA) plans by default "is something that we're thinking through." MA plans are funded by the federal government and run by private insurance companies such as UnitedHealthcare and Humana, both of which have been accused of improperly denying necessary care to patients and overcharging taxpayers.
The default enrollment scheme was floated in the far-right Project 2025 agenda that President Donald Trump has repeatedly tried to disavow. Currently, older Americans who have received Social Security benefits for at least four months before they turn 65 are automatically enrolled in traditional Medicare, and they can choose to enroll in an MA plan as an alternative.
"Another bad idea straight from Project 2025," Rep. Mark Pocan (D-Wis.) said in response to Klomp's comments on the proposed default enrollment change. "Medicare Advantage is private, for-profit insurance that overcharges American taxpayers by billions every year and regularly denies seniors the care they need."
"Making Medicare Advantage the default option hurts patients and taxpayers," Pocan added, "but it will make insurance execs a lot of money."
"With Mehmet Oz running the agency, they can move incredibly quickly to make that happen, and they are."
Klomp said no plans have been finalized, but defenders of traditional Medicare warned that CMS—headed by Mehmet Oz, who during his 2022 US Senate run backed a plan entitled "Medicare Advantage for All"—could try to swiftly ram the change through without public input.
"With Mehmet Oz running the agency, they can move incredibly quickly to make that happen, and they are," Alex Lawson, executive director of the progressive advocacy group Social Security Works, told Common Dreams on Friday. "They will not explain it to the people, because the people hate the idea. Instead, they say 'change the default option' and other policy jargon to try and hide the fact of what they are doing, privatizing Medicare."
"They want to remove the guarantee of Medicare," warned Lawson, "and replace it with the same private insurance giants that make billions denying healthcare, especially to those who need it the most."
Experts say making Medicare Advantage plans the default enrollment option for seniors would likely decrease traditional Medicare enrollment dramatically.
Given massive overpayments to Medicare Advantage plans—potentially $1.2 trillion over the next decade, according to one independent estimate—a large increase in MA enrollment would be sure to drive up costs and monthly premiums across the board. A report released last month by the congressional Joint Economic Committee estimated that MA overpayments led to premium hikes of $212 per Medicare Part B enrollee last year.
"Since 2016, MA overpayments have added an estimated $82 billion to Part B premiums," the congressional report found. "[Traditional Medicare] beneficiaries, who are not enrolled in MA, bore roughly $6 billion of that burden."
Under one scheme floated last year by Rep. David Schweikert (R-Ariz.), eligible Medicare recipients would be automatically enrolled in the "MA plan with the lowest premium available," unless they actively decide to opt out. Once enrolled in an MA plan, individuals would be unable to switch plans for three years.
Wendell Potter, a former health insurance executive who now champions Medicare for All, warned Friday that under Schweikert's plan, "seniors would be locked in a plan that the government chose for them, that has a limited network of doctors and hospitals, that makes them pay the entire bill for services they might receive outside of that network, and that denies coverage for medically necessary care far more than traditional Medicare—for three years."
In addition to weighing the default enrollment change, the Trump administration has recently delivered smaller-scale but significant victories to MA insurers, including by boosting federal payment rates—bowing to a massive industry lobbying blitz—and easing rules around the marketing of MA plans.
David Lipschutz, co-director of law and policy at the Center for Medicare Advocacy, said Thursday that the latter move represents "a rollback of consumer protections, which gives in to pressures from the insurance industry and those who sell their products."

Our healthcare ‘system’—with or without the Affordable Care Act—is unsustainable: we have reached the end of the line.
Those without employer sponsored insurance (or Federal insurance like Medicare or the VA) in Red states, who signed up for the Affordable Care Act (aka Obamacare), are now learning what they voted for: higher premiums for health insurance, maybe unaffordable. Meanwhile, premiums continue to rise relentlessly for employers and employees.
Our healthcare "system" is unsustainable: we have reached the end of the line.
Americans pay more for healthcare (about18 percent of GDP) than any other developed country, with mediocre outcomes. Yet the other countries, with better outcomes, have universal coverage.
It is time for change. Extend traditional Medicare to all Americans (gradually, over the course of several years). Medicare is familiar; it works. Private for profit-health insurance, less than a century old, makes no sense today.
Sick and injured patients have turned to medicine—to healers—since time immemorial. Health insurance is new: Blue Cross started as a community non profit organization in 1929, to cover surgery in hospitals.
Private for profit-health insurance, less than a century old, makes no sense today.
Yes, we are a capitalist country, and markets are efficient at producing many things, like commodities: groceries, shoes, cars, even some insurance, when it is straightforward and highly regulated, like auto insurance. But for-profit health insurance does not work.
The idea of insurance is to spread risk over a maximum number of subscribers, each of whom is at the same low risk of unpredictable casualty, like fire. This was essentially the situation of Americans a century ago—illness and injury were acute and unpredictable, patients either recovered or died. Everyone was at similar risk, only surgery was expensive.
Today is different: illness is not only predictable, it can be chronic, even life long. Moreover, today’s scientific care is expensive. The social determinants of health—income security, education, adequate food and shelter, social support (your zip code, not your genetic code)—plus public health, keep healthy people healthy.
Medical care is for the sick.
For-profit health insurers maximize premiums, minimize cost (provider fees), keep the difference, and most important, avoid the sick. Insurers exclude those with “pre-existing” conditions whenever allowed (not under the ACA), deny "authorization" where they can. They tailor "plans" with carefully engineered restrictions you don’t discover until you file a claim. They are not even providing insurance: the payments from the Federal government are risk adjusted, so the insurers are paid more for riskier patients (and they are now illegally upcoding). The providers are not. Making this happen entails huge administrative expense, which adds no value for patients or providers, only massive returns to investors. United Health Group is the third largest company in the Fortune 500.
Healthy people don’t know what plan is "right for them"; they hate the annual "choice." They only know what they can afford. (Sick people know what they need.) They do want to choose their doctor.
Traditional Medicare eliminates these problems for its beneficiaries: by law, everything medically necessary is covered. The Federal government determines fees for doctors and hospitals based on cost, as it did historically when markets didn’t work. Beneficiaries pay premiums based on income.
Fee-for-service works when we pay the right fees for the right services. Today, based on 1950’s medicine, Medicare pays too little for office visits, so-called ‘cognitive’ services (versus procedures) both primary and specialized, so there are too few providers, especially as Medicare rolls expand with retiring
Boomers. No office doctor can make a living from Medicare anymore. That is, however, easy to fix: pay providers more to care for the sickest people, who need the services only highly skilled, experienced physicians can provide. Pay surgeons less.
Best of all, Medicare is simple—ask your grandmother.
But where will the money come from?
Start by eliminating Medicare Advantage (MA) and Part D, while updating Medicare to cover prescription drugs, along with vision, hearing aids, etc. MA was supposed to save taxpayers money by providing care more efficiently. Instead, Medicare pays MA companies 20 percent more than traditional Medicare for comparable patients.
Then, require all employers (including those who currently don’t provide insurance) to pay premiums to Medicare based on payroll. Require employees to pay Medicare premiums based on wages. Just like Social Security (of which Medicare is technically a provision). The Federal government continues to pay a share.
Everyone pays, everyone gets the care they need and nobody is left out. People can choose any qualified provider. Providers remain private, and are paid enough to attract and sustain the clinicians we want and need.
We have tried every kind of private for profit health insurance there is: employer sponsored, government subsidized, market based, capitation, value-based, catastrophic, health savings accounts—it no longer works for employers, taxpayers, or the sick. This year premiums will go up, coverage will go down.
Americans’ health will suffer.
Americans need care, not coverage. We clinicians have dedicated our lives to providing it. Medicare has served millions of us well for 60 years. We cannot allow opportunistic capitalists to stand in the way for the rest.
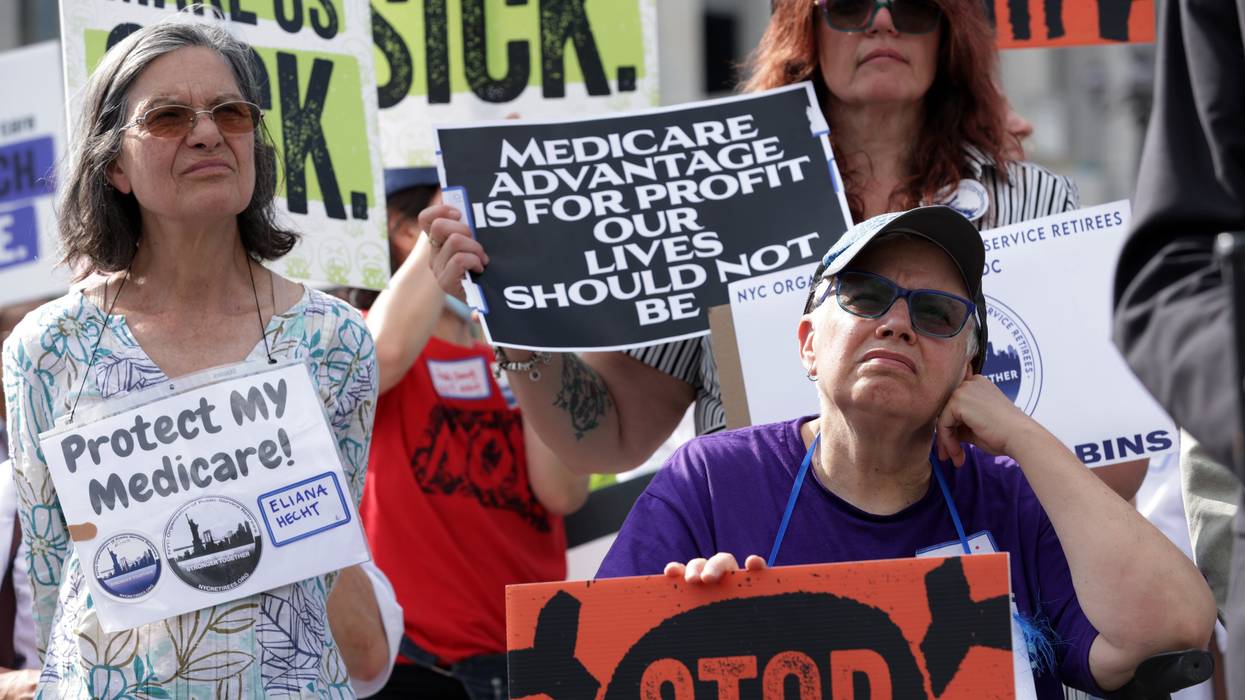
"We don't allow banks to call themselves the U.S. Treasury Investment Fund," said Rep. Mark Pocan. "We don't allow anyone to call themselves USPS Plus. So why allow insurance companies to call private insurance Medicare Advantage?"
A group of Democratic lawmakers on Wednesday reintroduced legislation aimed at reining in for-profit insurance companies who use the Medicare name to market their plans.
The "Save Medicare Act," being reintroduced by US Reps. Mark Pocan (D-Wis.), Ro Khanna (D-Calif.), and Jan Schakowsky (D-Ill.), bars private insurers from using the word "Medicare" in marketing their plans, imposing "significant fines" for any insurer that doesn't comply.
At issue, the lawmakers said, is that insurers are flooding the airwaves with ads for Medicare Advantage plans during open enrollment periods. The ads are deceiving Americans into thinking their plans are just variations of Medicare services offered by the federal government, they said.
"Let’s be clear: Medicare Advantage is not Medicare," said Schakowsky. "These private insurance plans use Medicare’s trusted name while too often denying medically necessary care, restricting providers, and overcharging taxpayers by billions. That is unacceptable. We have seen insurers exploit the system to boost profits at the expense of seniors."
Khanna noted that Medicare Advantage is "a private insurance program that too often boosts profits by limiting coverage," even as it "misleads seniors into thinking it's traditional Medicare."
"That's wrong," Khanna emphasized. "This legislation will stop private insurers from cashing in on the Medicare name. We should be working to protect and expand real Medicare instead."
Pocan declared that "only Medicare is Medicare," adding that Medicare Advantage plans "often leave patients without the benefits they need while overcharging the federal government for corporate profit."
"This bill makes clear what is—and what is not—Medicare," added Pocan, "and ensures this essential program will continue to serve seniors and other Americans for generations to come."
Pocan also posted a video on social media where he talked about his elderly mother being unable to see the physician that came to her assisted living home because she relied on Medicare Advantage and the doctor in question was out of network.
"She would have had to go all the way across town to get that care," Pocan explained. "The problem is, she wasn't very mobile and she never got the medical care."
We don't allow banks to call themselves the U.S. Treasury Investment Fund. We don't allow anyone to call themselves USPS Plus.
So why allow insurance companies to call private insurance Medicare Advantage?
I’m reintroducing the Save Medicare Act with @RepRoKhanna and… pic.twitter.com/c6dAXpEJqY
— Rep. Mark Pocan (@RepMarkPocan) March 4, 2026
"We don't allow banks to call themselves the U.S. Treasury Investment Fund," said Pocan. "We don't allow anyone to call themselves USPS Plus. So why allow insurance companies to call private insurance Medicare Advantage?"
Many progressive critics have for years pointed to Medicare Advantage as a legitimate example of wasteful spending by the federal government.
A report released in January by the Medicare Payment Advisory Commission (MedPAC), an independent congressional agency that advises lawmakers on Medicare, estimated that overpayments to Medicare Advantage plans could total $76 billion in 2026.
One major factor in the overpayments is that patients using Medicare Advantage plans tend to be healthier than patients on traditional Medicare, with the result being that private insurers charge the government more than is necessary to meet these patients' needs.
On Wednesday, Schakowsky said that the "crucial legislation" she joined Khanna and Pocan in introducing "will end deceptive marketing and ensure beneficiaries understand the difference between traditional Medicare and private insurance plans."
"Seniors deserve transparency, accountability, and the full benefits they have earned," she said.
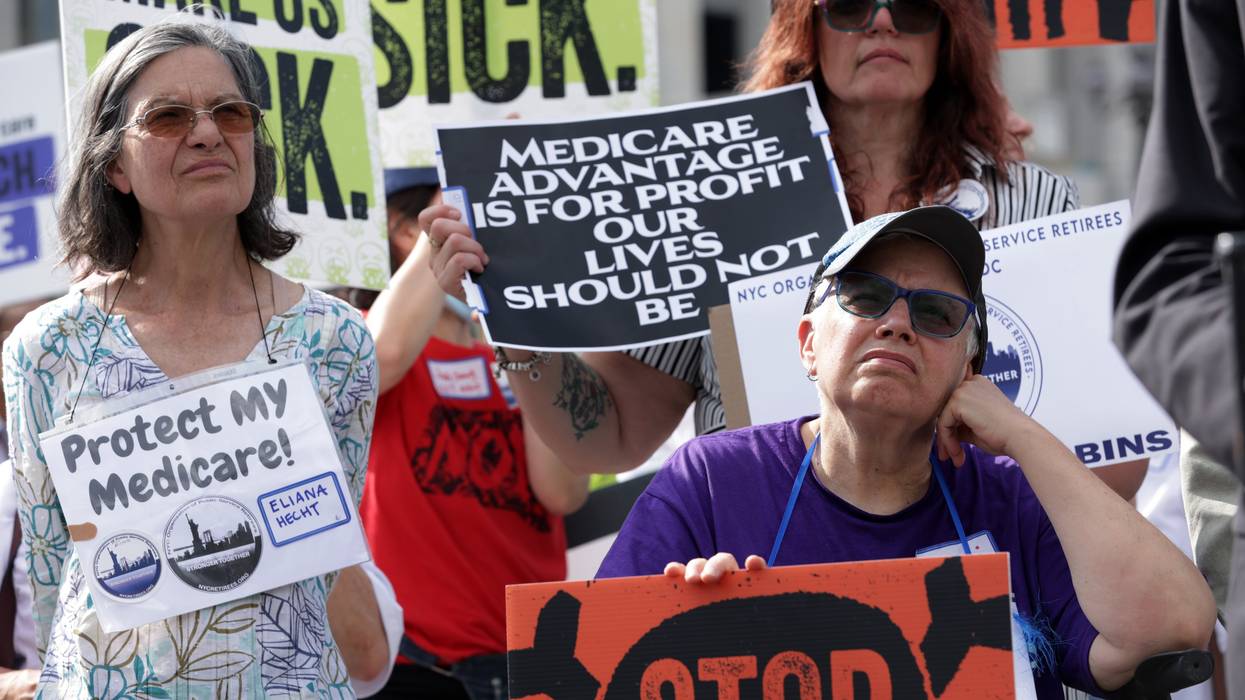
"These private insurer-run plans are more expensive AND lead to worse outcomes for patients," said Rep. Pramila Jayapal. "It’s time to rein in Medicare DisAdvantage and protect traditional Medicare."
A report released earlier this month to little fanfare estimated that federal overpayments to privately run Medicare Advantage plans could total $76 billion this year—or potentially a staggering $1.2 trillion over the next decade if current trends persist.
The Medicare Payment Advisory Commission (MedPAC), an independent congressional agency that advises lawmakers on Medicare, calculates overpayments by comparing spending on Medicare Advantage (MA) plans to what the federal government would have spent if MA enrollees were on traditional fee-for-service Medicare.
In a report published earlier this month, MedPAC showed that overpayments to MA plans this year are projected to be around $76 billion. Roughly $22 billion of that total is due to coding practices by MA providers, which are notorious for making patients appear sicker than they are to receive larger payments from the federal government. MA plans are paid lump sums to cover expected future healthcare services for patients based on their risk scores.
Another factor driving overpayments to MA plans—which now cover 55% of eligible Medicare beneficiaries—is a phenomenon known as favorable selection. MA enrollees tend to be healthier on average than recipients of traditional Medicare, resulting in higher payments to Medicare Advantage plans than are necessary based on patients' healthcare needs.
According to MedPAC, favorable selection will account for $57 billion of the expected overpayments to MA plans this year. The Trump administration gave Medicare Advantage plans a more than $25 billion boost in federal payments for 2026, even amid mounting bipartisan concerns about fraud in the program.
The National Committee to Preserve Social Security and Medicare (NCPSSM) said the MedPAC analysis "confirms that these private plans are bleeding taxpayers for billions of dollars more than traditional Medicare would cost for comparable enrollees."
US Rep. Pramila Jayapal (D-Wash.) wrote in response to the MedPAC findings that "Medicare DisAdvantage will rip off American taxpayers to the tune of $76 billion in 2026."
"These private insurer-run plans are more expensive AND lead to worse outcomes for patients," Jayapal, a leading supporter of Medicare for All legislation in the House, wrote in a social media post. "It’s time to rein in Medicare DisAdvantage and protect traditional Medicare."
The MedPAC analysis was released days after Republicans on the Senate Judiciary Committee published a report revealing how UnitedHealth Group, the largest provider of MA plans in the US, "has turned risk adjustment into a major profit-centered strategy," reaping massive payments from the federal government through upcoding.
NCPSSM noted that "while UnitedHealth... has emerged as the worst offender, it’s abundantly clear that many MA insurers are engaged in these shady practices."
"Look no further than insurers’ reliance on prior authorizations for procedures and treatments that normally would be automatically covered in traditional Medicare," the group said. "This includes denying skilled nursing care that jeopardizes older patients who have nowhere else to turn."