

SUBSCRIBE TO OUR FREE NEWSLETTER
Daily news & progressive opinion—funded by the people, not the corporations—delivered straight to your inbox.
5
#000000
#FFFFFF
To donate by check, phone, or other method, see our More Ways to Give page.
Daily news & progressive opinion—funded by the people, not the corporations—delivered straight to your inbox.

"He’s so completely full of shit, and voters across the country know it," said one patient advocate.
US President Donald Trump, who signed into law the largest Medicaid cuts in history last year and allowed private insurance premiums to skyrocket, assured supporters gathered at a rally in Wasilla, Alaska on Tuesday that he intends to enact "a truly great healthcare plan" if Republicans retain control of Congress in next month's midterm elections.
As with his earlier empty promises of a forthcoming overhaul of the US healthcare system, Trump offered virtually no detail on what his proposal would entail, saying vaguely that he wants to "stop all payments to big insurance companies" and "give the money directly to you, the people," to "go out and buy better healthcare."
While Trump's supporters in Wasilla applauded his promise—"clapping like seals," as one critic put it—patient advocates noted that Republicans have done nothing but make the country's healthcare system even more brutal and expensive over the past two years.
"All they did was cut Medicaid by $1 trillion to give tax cuts to billionaires and kick 3 million off of [Affordable Care Act] insurance," Dr. Rob Davidson, executive director of the Committee to Protect Healthcare, wrote in a social media post late Tuesday.
"He’s so completely full of shit," said Davidson, "and voters across the country know it."
Watch Trump's comments:
The advocacy group Protect Our Care noted ahead of Tuesday's rally that more than 34,000 Alaskans have health insurance coverage during Trump's second White House term. Brad Woodhouse, the group's president, said in a statement that “Trump has miserably failed Alaskans on healthcare, and now, with Election Day closing in, he has the audacity to waltz back into the state and act like none of it ever happened?"
"Make no mistake, this is a healthcare election, and Republicans have a whole lot to answer for," said Woodhouse. "With just weeks left until voters head to the polls, Trump is pulling out all the stops, from flashy rallies to desperate bribes. But the fallout from his healthcare cuts isn’t going anywhere. Families across Alaska are stretching their medications, skipping checkups, and crossing their fingers that nobody in the family gets sick enough to send them spiraling into debt."
"So Trump can put on his little show all he wants," Woodhouse added, "but eventually the stage lights will go out, the cameras will leave, and Alaskans will still be stuck paying the price."
Trump's rally came a week after the health policy organization KFF released a survey showing that 66% of Americans strongly or somewhat favor Medicare for All—the highest rate of approval since the group began asking about Medicare for All in 2017.
Separate Axios polling published Tuesday showed that a plurality of Americans support Medicare for All—and that Medicare for All's supporters outnumber its opponents nearly two to one.
Despite widespread and growing support for the proposal—which would guarantee comprehensive health coverage to everyone in the US at a lower overall cost than the status quo—Trump has openly attacked Medicare for All, falsely claiming it would cost "the entire budget of the whole country."

Republicans' cuts to Medicaid and their refusal to extend enhanced Affordable Care Act subsidies are key factors in the coverage drop.
Independent healthcare analyst Charles Gaba on Thursday published an updated analysis estimating that up to 12 million Americans have lost their insurance coverage since the start of President Donald Trump's second term.
Gaba based his new estimate on updated data he compiled from recent reports for Medicare, Medicaid, and the Children's Health Insurance Program (CHIP), as well as some state enrollment data for Affordable Care Act (ACA) insurance exchanges.
In total, Gaba found that enrollment in Medicaid and CHIP has dropped by 6.2 million people since the start of Trump's second term, while enrollment in ACA exchanges is down by anywhere from 4.6 million to 6.1 million people, and enrollment in Basic Health Plans (BHP) is down by nearly 275,000 people over the same period.
While there are around 1.8 million more people enrolled in Medicare now than there were at the start of Trump's term, Gaba noted that this isn't nearly enough to make up for the loss of enrollment in other programs.
Adding everything up, Gaba estimated that "between 10.88 million and 12.40 million fewer Americans enrolled in a public healthcare coverage program as of June 2026 than in were as of January 2025."
As in prior analyses, Gaba examined the possibility that some of the people who lost coverage through these programs transitioned to employer-sponsored insurance, but deemed it "extremely unlikely... since unemployment is higher than it was in January 2025."
Over the last two years, Trump and congressional Republicans have taken a number of actions that have made healthcare less affordable and pushed people off coverage.
First, they cut spending on Medicaid by an estimated $900 billion over a 10-year period when they enacted the One Big Beautiful Bill Act in 2025. The Congressional Budget Office projects these cuts will leave more than 10 million fewer people enrolled in the program by 2034.
GOP lawmakers last year also refused to extend enhanced subsidies for insurance plans purchased through the ACA, even as insurers raised premiums on those plans by an average of 26% this year, according to an analysis published by KFF.
In a Thursday article published by Time, scholars Neale Mahoney and Abigail Sanchez of the Stanford Institute for Economic Research warned that the costs of private health insurance are set to spike even further in 2027.
"Employer health plan costs are projected to rise 8 to 10% next year," Mahoney and Sanchez explained, "the largest increase in more than 20 years and double the average increase of the 2010s."
The two researchers said there are three major reasons for the surge in insurance costs: The expiration of the enhanced ACA subsidies, an increase in premiums and out-of-pocket costs for employer-based insurance plans, and the upcoming Medicaid work requirements projected to push millions of people off the program.

"Medicaid work reporting requirements are a flawed policy if the goal really is to incentivize work, but they are very effective at taking Medicaid coverage away by tangling folks up in red tape," said one expert.
Human rights organizations said Thursday that Nebraska should be seen as a bright red warning sign of what's to come for states across the US as they implement the draconian Medicaid work requirements included in the budget legislation that President Donald Trump signed into law last year.
In early May, Nebraska became the first state to implement the new work reporting mandates, which require certain Medicaid recipients to document at least 80 hours of work or other qualifying activities per month to remain enrolled in the program. Republican Gov. Jim Pillen, announced the state's fast-tracked implementation of the requirements at a celebratory press conference late last year alongside Mehmet Oz, head of the Centers for Medicare and Medicaid Services.
Human Rights Watch (HRW), Oxfam America, and Nebraska Appleseed said in a joint report released Thursday that the rush to impose the mandates has had the predicted results of mass confusion and bureaucratic chaos, previewing what millions of Medicaid recipients across the country can expect in the months ahead.
“Nebraska is the canary in the coal mine for issues that most states will face when they begin implementing these work requirements,” said Matt McConnell, a US researcher on economic, social, and cultural rights at HRW. "As they do, they should make sure red tape doesn’t strip people of healthcare."
The trio of advocacy groups interviewed a dozen Nebraskans who have directly experienced or witnessed the unruly rollout of the expanded work requirements. One 64-year-old man "said he lost his Medicaid coverage while undergoing treatment for kidney cancer and multiple chronic health conditions," the groups noted.
"He said a representative of the health plan that managed his Medicaid coverage informed him he lost access because he was not working, even though he is unable to work due to his condition," the groups added. The man said the loss of Medicaid coverage disrupted his care, including an appointment with a cancer specialist.
The Trump administration has said even people with terminal cancer are not necessarily exempt from the new work reporting requirements.
One Medicaid eligibility worker from the Nebraska Department of Health and Human Services told HRW, Oxfam, and Nebraska Appleseed that "poor training, vague and inconsistent guidance, and technical issues, including unprepared software systems, had caused stress and uncertainty for applicants and for state employees."
“We just sometimes don’t know what we’re doing,” the worker said. "I wish the people who make policies knew what they were doing."
It's unclear exactly how many people have lost Medicaid in Nebraska as a result of the new requirements. Sarah Maresh, healthcare access program director at Nebraska Appleseed, said Thursday that obtaining data from the state has been "like pulling teeth."
"Nebraskans deserve access to this information," said Maresh. "You can’t fix problems you refuse to measure."
Earlier this week, following relentless pressure from advocates, Nebraska's health department released preliminary data showing that more than 1,000 Nebraskans have been deprived of Medicaid coverage due to the expanded work requirements—a figure that's believed to be a significant undercount.
"I have been saying for years that Medicaid work reporting requirements are a flawed policy if the goal really is to incentivize work, but they are very effective at taking Medicaid coverage away by tangling folks up in red tape," Joan Alker, executive director of Georgetown University's Center for Children and Families, wrote in a blog post earlier this week. "Unfortunately, Nebraska’s data only reinforces this point."
Nationwide, millions of people have lost Medicaid coverage since Trump signed the GOP budget package, which includes around $800 billion in cuts to Medicaid over the next decade.
States face a January 1, 2027 deadline to implement the expanded work requirements—though states are allowed to move more quickly. Montana and Arkansas have joined Nebraska in implementing the mandates ahead of the federal deadline, resulting in similar chaos and confusion.

"Everyone, no matter who they are, where they live, how much money they make, or how they get their insurance, deserves access to abortion care without barriers."
On Wednesday, reproductive rights groups marked half a century of abortion care being "baselessly set apart from all other healthcare," with coverage for abortions blocked in government-funded healthcare plans like Medicaid, which about 16 million women of reproductive age rely on.
"Our constituents have suffered the consequences," said the Congressional Reproductive Freedom Caucus, chaired by Reps. Diana DeGette (D-Colo.) and Ayanna Pressley (D-Mass.).
For 50 years, the Hyde Amendment—proposed by the late Rep. Henry Hyde (D-Ill.), who expressed his wish to prevent "anybody having an abortion" and said blocking federal funds within the Medicaid program from being used for care was the best way to do so—has stopped hundreds of thousands of people from obtaining abortion care, and has been called by anti-abortion groups "one of the greatest achievements of the pro-life movement to date."
The Reproductive Freedom Caucus denounced the budget rider that has been reeimplemented in appropriations bills every year since 1976 as "a dangerous, racist, and classist abortion ban. An abortion ban for the working class and people of color, who disproportionately receive health insurance through the federal government."
The caucus noted that more than 200 House Democrats have supported efforts to repeal the amendment, and advocacy groups on Wednesday called on Congress to pass the Equal Access to Abortion Coverage in Health Insurance (EACH) Act, which would permanently repeal the Hyde Amendment.
"Without solutions like the EACH Act, the Hyde Amendment will continue to force people with low incomes to struggle for the care they need or carry a pregnancy against their will," said the National Women's Law Center (NWLC). "Everyone, no matter who they are, where they live, how much money they make, or how they get their insurance, deserves access to abortion care without barriers."
In addition to low-income people who rely on Medicaid, said the National Network of Abortion Funds (NNAF), the Hyde Amendment blocks abortion care for Indigenous people who use the Indian Health Service, people in federal prisons, disabled people, military service members and their families, and federal employees, among others.
Twenty-nine states follow Hyde Amendment restrictions, which include "exceptions" for pregnancies resulting from rape or incest or cases in which a pregnant person's life is at risk. Twenty-one states use state funds to cover abortion care, but nearly half of US women of reproductive age who use Medicaid live in states that either ban abortion care or bar them from getting abortions using the federally funded healthcare plan.
NNAF highlighted the network's decades of work to counter the Hyde Amendment by ensuring people who need abortions can access funding, which abortion funds across the country obtain through grassroots donations as they also advocate to end the Hyde Amendment.
"By the 1990s—less than two decades after Hyde first passed—28 abortion funds had formed across the country. Twenty-two of those funds started the National Network of Abortion Funds (NNAF) in 1993," said NNAF. "We joined together to build strategic power and end the Hyde Amendment. Today, our network has nearly 100 member abortion funds, and our fight against Hyde continues."
"The fierce abortion funds in our network have raised money, arranged travel, connected folks to clinics, provided practical support, and fought restrictions in their states and communities," the group added. "Despite endless challenges, their tireless work has built power for our collective goal: Make abortion accessible for all."
Abortion funds have helped people obtain care across the country, but the NWLC emphasized that the Hyde Amendment has still left hundreds of thousands of women with no choice but to pay for abortions out of pocket—often pushing them to delay care while they gather funds or to carry a pregnancy to term when they don't want to or can't afford to become a parent.
"While abortion costs vary by location, facility, and stage of pregnancy, the median out-of-pocket costs in 2023 were $563 for medication abortion, $650 for first-trimester procedural abortion, and $1,000 for second-trimester abortion care," said NWLC. "Those costs account for just the procedure itself, not additional expenses. And yet, nearly half of American families cannot afford the true cost of living... So, when the Hyde Amendment denies someone abortion care, the compounding costs can push people further into a struggle to survive and meet basic needs."
Dr. Jamila Perritt, president and CEO of Physicians for Reproductive Health, remembered Rosie Jimenez, a 27-year-old mother and aspiring teacher who died in 1977, almost exactly a year after the Hyde Amendment was passed, after being denied Medicaid coverage for an abortion.
“Hyde has harmed generations of people seeking abortion care," said Perritt. "Women like Rosie Jimenez, the first known person to die because of Hyde Amendment restrictions, should still be here. No one, no matter what insurance they have access to or who they are, should be denied abortion care, full stop."
Stateline reported Tuesday that with weeks to go until the midterm elections and President Donald Trump's approval rating plummeting to record lows, anti-abortion groups are increasingly concerned that a Democratic majority could repeal the amendment, which it came close to doing in 2022.
“If there becomes a pro-abortion majority in Congress, then Hyde is going to be one of the first things to go, probably, especially because it’s been in the spotlight more recently,” Gavin Oxley, spokesperson for Americans United for Life, told Stateline. Particularly since Trump told Republicans to be "a little flexible" on the Hyde Amendment when the party was pushing to end subsidies under the Affordable Care Act, Oxley said "there are some Republicans who may not be as committed to protecting Hyde.”
Perritt expressed hope that Congress could pass the EACH Act, which now "has the highest amount of support... ever seen with over 200 co-sponsors."
"As a DC-based OB-GYN and abortion provider, I see patients burdened with the cost of abortion care, forcing them to choose between basic living needs and lifesaving healthcare," she said. "The Hyde Amendment is a zero-sum constraint that is not about patients’ health and autonomy, but instead about punishing people for making informed decisions about their bodies, families, and futures. Enough is enough."
"We do not need another Hyde Amendment anniversary," said Perritt. "We need to repeal the Hyde Amendment for good.”

At long last, the nation’s healthcare plan will guarantee that not only is everyone covered for care, free at the point of service, but that there is a place within reasonable distance to find that care.
After a century of providing healthcare to this rural, southeast Michigan community, Sturgis Hospital closed in June with only 70 hours warning.
The hospital was not on the at-risk-of-closing list that had been published by Sen. Ed Markey (D-Mass.) a year earlier.
Over 300 Sturgis Hospital employees are scrambling to find work. Registered nurse Beth Kelley, who had worked at Sturgis for 32 years, described the meeting room as filled with “shock” and “devastation” when management announced that the hospital was closing.
Nationwide more than 700 rural hospitals are at risk of closing, over half at immediate risk within the next two to three years. The 700 hospitals represent about one-third of all rural hospitals.
The termination of care at Sturgis Hospital overloads the city’s emergency medical services. Director of public safety Ryan Banaszak said, “What was once approximately a 2-mile transport for patients has now become closer to 25 miles, which takes ambulance personnel and equipment out of service for a much longer period of time.”
The impact is great on Michigan Medicaid patients, who cannot use the closest hospital because it is across the state line in Indiana.
“Rural hospital closures lead to significant increases in mortality, and birthing outcomes and obstetric care suffer following closures,” said Michael Shepherd, University of Michigan health policy researcher. The risk increases with every additional mile for emergencies like strokes and heart attacks.
A few weeks later the rural River District Hospital in St. Clair County northeast of Detroit announced the closing of its inpatient and emergency services. Four more rural Michigan hospitals—in Mt. Pleasant, Carson City, Ontonagon, and Dowagiac—are in danger of closing with the upcoming Medicaid cuts.
Rural Americans live sicker and die younger than those in urban areas. Life expectancy is about three years shorter in rural communities. When a rural hospital closes, the mortality rate rises by 5.9%. Rural hospital closures increase mortality for emergencies such as heart attacks and strokes by about 10%.
“There are two kinds of Americans: those who live 12 minutes from an emergency department and those who live 72,” writes Ayla Ellison who grew up in Carmi in southern Illinois. “Whether you survive a heart attack, deliver a healthy baby, or die from something entirely treatable increasingly depends not on the severity of your illness, but on the distance to the nearest hospital,” she continues. She explores the consequences of rural hospitals folding in a country where no one is responsible for assuring help is close enough for a chance at life. The hospital in Carmi closed 20 years ago. Nine more Illinois hospitals are at risk of closure, most of them in southern Illinois.
Other states are worse off. In Mississippi, 51% of the rural hospitals are at risk of closing; in Alabama, 52%; in Arkansas, 68%.
Dr. Kenneth Williams battled for decades to sustain the hospital (Alliance Healthcare System) in Holly Springs, Mississippi. Rapid expansion of Medicare Advantage plans reduced reimbursement and increased denials of payment to the hospital. In 2023, facing financial desperation, the hospital converted to Rural Emergency Hospital status, a federal program designed to stabilize struggling rural hospitals. The Center for Medicare and Medicaid Services (CMS) later removed that designation, leaving the hospital again fighting to stay open.
Nationwide more than 700 rural hospitals are at risk of closing, over half at immediate risk within the next two to three years. The 700 hospitals represent about one-third of all rural hospitals. That report was prior to the passage of HR 1, the “One Big Beautiful Bill” that slashes $1 trillion from Medicaid. The crisis escalates from grim to disastrous with the looming Medicaid cuts.
Federal efforts to save our rural hospitals have been pitifully inadequate in the face of the towering problem.
Critical Access Hospitals, created by Congress in 1997, allow small rural hospitals to receive cost-based Medicare reimbursement. The plan was designed to stem the tide of closures.
Between 2010 and 2025, 152 rural hospitals closed. Of these, 52 were Critical Access Hospitals.
In 2021 Congress created Rural Emergency Hospitals. This designation provides for enhanced Medicare payments allowing rural hospitals to continue with outpatient and emergency services only, instead of closing.
In 2023, Sturgis hospital was “saved” by conversion to a Rural Emergency Hospital, delaying its shutdown by three years.
Neither these nor any other federal plans are big enough or thorough enough to work.
CMS Director Mehmet Oz recently visited Kentucky, home of 35 rural at-risk hospitals. He touted the $50 billion in Rural Health Transformation Funds as the solution. The assertion is absurd.
At best, Kentucky will get $1 billion from the rural transformation funds as it loses $21 billion in Medicaid funds. Not even a wizard can turn that into a winner.
As Boston University professor Alan Sager notes, no US entity is responsible for sustaining or building or financing hospitals based on community need.
“The whole Appalachian area has been abandoned, but its hospitals should be funded and improved, as a necessity of life—like the post office,” says Dare Cima, who is from southeastern Kentucky.
With passage of H R 3069, Improved Medicare for All, finally, the nation will take responsibility for assuring that rural areas have adequate facilities. Hospitals will be paid quarterly, in advance, with a global budget that provides operating expenses.
The allocation to hospitals ensures proper staffing with safe nurse-to-patient ratios and optimal staffing for physicians and other healthcare workers. Physician salaries can be included in the global budget. Adjustments to the operating budget will be made “to decrease healthcare disparities in rural or medically underserved areas.”
Special projects funds will be used to end discrimination based on race or other underserved categories including geography. Funds will be allocated for construction of new facilities where needed. At long last, the nation’s healthcare plan will guarantee that not only is everyone covered for care, free at the point of service, but that there is a place within reasonable distance to find that care.
The late Dr. Ewell Scott, Medical Staff president of St. Clair Regional Medical Center in Morehead in the mountains of eastern Kentucky, predicted that if current policy continued, it was just a matter of time until all of Kentucky’s hospitals east of I-75 would be closed.
Sadly, that prediction is breathtakingly close as 16 of east Kentucky’s hospitals in the 5th Congressional District, including Dr. Scott’s beloved St. Clair hospital, are on the list of those endangered with closing by the passage of HR 1.
But Dr. Scott was fighting for a different future. He persuaded the City of Morehead to pass a resolution supporting Improved Medicare for All, a national single-payer plan that would cover us all and fund the hospitals.
Dr. Scott urged all who would listen to tell their congresspersons: “We know the solution. You’ve got to have the guts to stand up and do it.”

We need to hold lawmakers who make working people suffer to enrich the already wealthy accountable.
My mom worked harder than anyone I know. She wanted a good life for us. It was a hard life—I remember the Christmas she had to pawn our gifts to pay the light bill—but she made it special for us.
Now I have two kids of my own, and I want them to have every opportunity that other children have.
The landscape is tough out there. Like many Americans, I can’t afford childcare, and finding work that accommodates my need to care for my young children is hard. With inflation, the little income I have doesn’t go nearly as far as it used to.
I’m grateful to have assistance with food, housing, and healthcare through our social safety net programs.
Food programs like SNAP (also known as “food stamps”) and WIC (that’s the Special Supplemental Nutrition Program for Women, Infants, and Children) have literally saved our lives when we’ve been hungry. I wouldn’t be able to feed my children without them. And thanks to Medicaid, we have healthcare.
But I’m sick with worry about the cuts to SNAP and Medicaid that are barreling my way. The so-called “Big Beautiful Bill” slashed these programs last year so lawmakers could slash taxes for corporations and the wealthy, and some of the worst cuts will take place after this year’s midterms.
The uncertainty is causing so much stress. The first change I noticed is they cut off my eyeglasses subsidy. What’s next? Meanwhile, the cost of living keeps going up and up, outpacing wage gains for me and countless others. Our SNAP benefits cover much less than they did a year ago, and that’s before potential cuts take effect.
I feel like I’m waiting for a bomb to drop on me and my kids, and I’m not the only one.
“The average minimum-wage worker must work nearly 116 hours per week, nearly three full-time jobs, to afford a two-bedroom rental home,” the National Low Income Housing Coalition reports. That’s the truth—my own sister works three jobs and still has to live with roommates.
Lawmakers are telling us we can’t have healthcare now unless we work, even in areas with low wages. Yet those making the laws enjoy free government-socialized healthcare and high wages.
They say SNAP benefits can’t be used for a cake or soda for my child’s birthday. Yet no one would stop the wealthy from using their $1 trillion in tax cuts under the “Big Beautiful Bill” to buy their kid a yacht.
Poor and low-income people deserve to be happy too. We deserve healthcare, food, housing, and even a child’s small birthday party. It feels like we’re being punished for working regular jobs—and like lawmakers want to keep us down so we don’t fight back against this inequality.
But we are fighting back.
I’ve started attending our local town hall meetings and hearing the stories of injustice and poverty. I started volunteering with a non-profit organization in my community. I help get goods to people in need, even as I am also in need, because that’s what we do. Poor and low-income people help each other out, because we understand what it’s like to see our kids go without while we work our fingers to the bone.
But we can’t do it alone. We need to demand from lawmakers that instead of cutting our healthcare, food, and housing benefits, we need to expand them to meet the great need in this country. We need a livable wage so we can afford market rent and rising food prices.
And we need to hold lawmakers who make working people suffer to enrich the already wealthy accountable.

"Over half the provisions of the Big Ugly Bill have already gone into effect, and the negative results are already devastating."
Independent healthcare analyst Charles Gaba on Thursday published a detailed report estimating that up to 10 million people living in the US have lost their healthcare coverage since the start of President Donald Trump's second term.
In his analysis, Gaba brought together the most recent enrollment data for Medicaid, the Children's Health Insurance Program (CHIP), Medicare, and the Affordable Care Act (ACA).
Breaking things down by program, Gaba estimated there are 5.9 million fewer people enrolled in Medicaid and CHIP, as well as at least 4.5 million fewer people enrolled in the ACA, since Trump returned to power in January 2025.
These losses in coverage are somewhat mitigated by Medicare, whose enrollment has increased by around 1.6 million people during Trump's second term.
Losing access to these programs doesn't mean that the people were on them have gotten well paying jobs and are receiving insurance from their employer, Gaba wrote. Given that the unemployment rate has risen during Trump's second term, Gaba suggested it is highly unlikely that there are now more people who get employer-sponsored coverage now than in January 2025.
Depending on a number of variables, Gaba concluded, somewhere between 8.8 million to 10.3 million fewer people now have healthcare coverage.
Adjusting for population growth, Gaba added, "you get a grand total of between 10.27 million and 11.75 million more Americans not enrolled in a public healthcare coverage program as of May 2026 than in were as of January 2025."
The healthcare analyst noted that "this isn't quite the same thing as counting how many lost coverage, but not having healthcare sucks regardless of how you slice it."
He also pointed out that the lost in healthcare coverage all came before the Medicaid work requirements from the GOP's 2025 budget law are put into effect.
"Over half the provisions of the Big Ugly Bill have already gone into effect," wrote Gaba, "and the negative results are already devastating."
Gaba's analysis was published just days after the Georgetown University Center for Children and Families released a report estimating that nearly 2.5 million children in the US have lost access to Medicaid or CHIP during Trump's second term.
Trump and congressional Republicans have taken a number of actions that have made healthcare less affordable.
First, they cut spending on Medicaid by an estimated $900 billion over a 10-year period when they enacted the One Big Beautiful Bill Act in 2025. The Congressional Budget Office projects these cuts will leave more than 10 million fewer people enrolled in the program by 2034.
GOP lawmakers last year also refused to extend enhanced subsidies for insurance plans purchased through the ACA, even as insurers raised premiums on those plans by an average of 26% this year, according to an analysis published by KFF.
According to Wednesday reporting by Politico, hospitals are sounding the alarm about new regulations being proposed by the Centers for Medicare and Medicaid Services that they say would cost hundreds of billions of dollars in lost revenue.
"If the rules are finalized and they lose hundreds of billions on top of Congress’ funding cuts," Politico reported, "hospitals say they’ll be forced to reduce services, lay off workers, consolidate operations or shutter entirely."
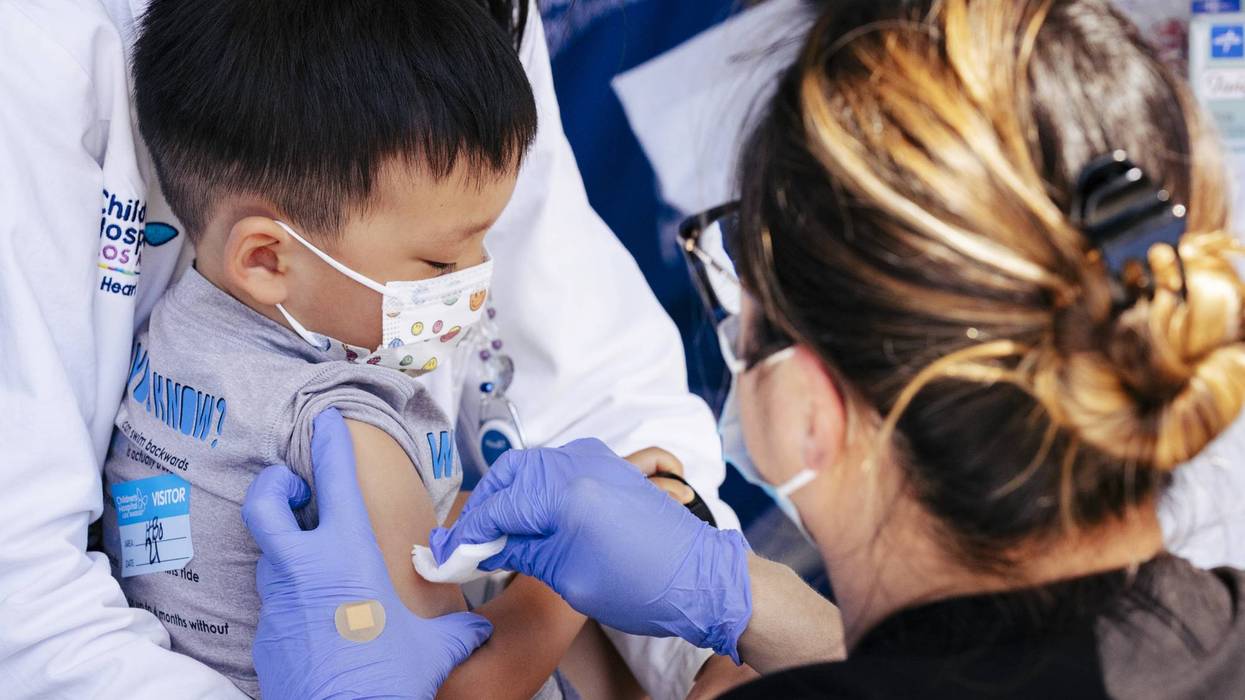
The drop in children covered by Medicaid comes before the most draconian changes to the program made by Republicans' 2025 budget law are set to take effect next year.
Nearly 2.5 million children living in the US have lost access to Medicaid or Children's Health Insurance Program coverage during President Donald Trump's second term, according to data published on Monday by the Georgetown University Center for Children and Families.
In total, five states have seen children's enrollment in Medicaid and CHIP fall by 10% or higher since January 2025, with Indiana seeing a drop in enrollment in those programs of more than 23%.
Colorado and Hawaii were the only two states to see a net increase in children in Medicaid or CHIP over that same period.
Joan Alker, executive director of the Center for Children and Families, described the drop in children enrolled in the programs as "a lot," and said it was important to track because "when Medicaid child enrollment declines, the number of uninsured kids typically goes up."
President Donald Trump and congressional Republicans cut spending on Medicaid by an estimated $900 billion over a 10-year period when they enacted the One Big Beautiful Bill Act in 2025. The Congressional Budget Office projects these cuts will leave more than 10 million fewer people enrolled in the program by 2034.
One way the GOP budget law is projected to kick people off Medicaid has been to add extra administrative burdens and paperwork for people who qualify for the program.
As explained by a Scripps News report published last week, Medicaid starting next year will make beneficiaries enroll twice a year instead of just once, while also mandating adults who "earn above a typical income cutoff and do not have children... work or volunteer at least 80 hours a month, or enroll in school."
Eileen Appelbaum, co-director of the Center for Economic and Policy Research, told Scripps News that this will result in many people not receiving Medicaid coverage despite being qualified for it.
"The best guesses from the experts are that two-thirds of the people that will be disqualified will actually be eligible, but they just couldn't handle the paperwork," Appelbaum explained.
In an op-ed published by Stat on Monday, Brown University epidemiologists Abdullah Shihipar and Brandon DL Marshall highlighted how getting out of the new Medicaid work requirements by proving yourself "medically frail" is shaping up to be a "nightmare scenario for millions of Americans."
"Let’s say you are undergoing cancer treatment, but you don’t have the right paperwork for your renewal," Shihipar and Marshall wrote. "As a result, you’re disenrolled from Medicaid. You desperately try to fix the mistake, but you are faced with long wait times and no answers, so you cease treatment altogether... Paperwork here is not merely an annoyance, it is a matter of life or death for millions with Medicaid coverage."
The Centers for Medicare and Medicaid Services' implementation of the One Big Beautiful Bill narrows the very protections Congress included to prevent vulnerable people nationwide from losing the health coverage they need.
The biggest Medicaid fight today isn't happening in Congress—it's happening inside the Centers for Medicare and Medicaid Services.
Now, a year after H.R. 1’s passage (the 2025 federal reconciliation bill enacting significant cuts and changes to Medicaid), CMS’ recently issued interim final rule (IFR) implementing the law’s work-reporting requirements in the program narrows the very protections Congress included to prevent vulnerable people nationwide from losing the health coverage they need.
The Congressional Budget Office previously estimated that more than 5 million people will lose Medicaid coverage because of these requirements. Already a conservative estimate as other organizations estimated over 10 million people are at risk of losing coverage, the number will surely be higher given CMS' IFR goes beyond the statutory language of the law.
The clearest example of this is the IFR's treatment of the medically frail exemption.
If the goal is really healthier communities and greater workforce participation, making it harder for medically vulnerable people to keep their health insurance is exactly the wrong approach.
Congress recognized that people living with complex medical conditions, disabilities, and chronic illnesses, including substance use disorder (SUD), should be protected from burdensome work-reporting requirements. As such, H.R. 1 specifically includes “medically frail” individuals among those exempt from the new requirements.
Yet CMS has added a new hurdle, putting millions of eligible Americans at dire risk of losing access to essential healthcare.
Under the IFR, people with SUD and other qualifying health conditions must also demonstrate that their condition "significantly impairs" their ability to satisfy the requirement before they can qualify for the exemption. This additional standard does not appear in the statute and will inevitably reduce the number of people who can secure the exemption.
For people living with SUD, the consequences could be profound.
While SUD is a chronic but treatable medical condition, pervasive stigma and discriminatory barriers have led to fewer than 1 in 5 people who need treatment actually receiving it. Amid persistent addiction and overdose crises, we should be making it easier for people to access the services and supports they need to become and stay well, not erecting additional barriers to lifesaving care.
Moreover, while CMS' rule relies heavily on Medicaid claims data and provider documentation to identify individuals who qualify as medically frail, the administration’s approach overlooks the reality that many people with SUD have never entered treatment due to the above-mentioned stigma and discrimination. Requiring additional documentation will not "motivate" people to seek care, as CMS suggests. Instead, it creates yet another barrier for people who are already among the hardest to reach.
When people are deprived of Medicaid access, their ability to engage in preventive care, behavioral health services, medications, and treatment that keep chronic conditions under control is also lost. And it doesn’t take a rocket scientist to understand how untreated health conditions can not just impede a person’s capacity to work but quickly lead to costly emergency services.
These are not only personal tragedies—they are costly public policy failures.
Taking away health coverage does not eliminate health needs. It just shifts and raises costs while undermining public health and safety. Access to healthcare is precisely what enables many people to work, care for their families, and be productive community members, so why are we erecting so many barriers?
If the goal is really healthier communities and greater workforce participation, making it harder for medically vulnerable people to keep their health insurance is exactly the wrong approach.
Last month, both our organizations, along with many other leading advocates nationwide, explicitly articulated these concerns and submitted comments urging the agency to reverse course and faithfully reinforce the protections Congress included in the law. While CMS' public comment period on the IFR is now closed, all those who share the same perspective can still take action by calling their members of Congress to share their concerns about the impact of H.R. 1 and specifically, how the administration is planning to implement the law.
A year after H.R. 1’s passage, the question is no longer simply about what Congress enacted—it is whether the regulations that make the law real will preserve purposeful protections or quietly erode them through administrative action.

New fact sheets detail how people in every US state are suffering from the Republican Party's assault on Medicaid and the Affordable Care Act.
The unprecedented healthcare cuts that President Donald Trump and the Republican Party enacted last summer have impacted people in all 50 US states, stripping insurance coverage from around 8 million Americans total and wreaking havoc on hospitals and other providers nationwide.
The advocacy group Protect Our Care on Tuesday released state-by-state fact sheets detailing how many people have lost Medicaid, Children's Health Insurance Program (CHIP), and Affordable Care Act coverage due to Republican policy decisions, including the party's roughly $900 billion in cuts to Medicaid and decision to let enhanced ACA subsidies expire, sending premiums skyrocketing.
“Eight million Americans have lost their health care because Donald Trump and Republicans decided they would rather hand out tax breaks to billionaires than protect working families," said Brad Woodhouse, the president of Protect Our Care. "Every day that healthcare becomes more expensive, a family is forced to make an impossible choice between putting food on the table and staying covered, a senior is forced to ration their medication, and an expectant mother has to travel farther to access maternity care."
In Maine, where Democrats are looking to finally unseat vulnerable Sen. Susan Collins, more than 18,700 people have lost Medicaid, CHIP, or ACA coverage under the Republican budget law. Included in that total are the more than 7,500 Mainers who dropped ACA marketplace coverage after premiums soared due to the lapse of enhanced subsidies at the end of 2025.
Collins voted to advance GOP budget legislation that included the devastating Medicaid cuts, but voted against final passage.
Protect Our Care noted that "Maine hospitals and clinics are facing a $38 million loss in funding and a 6.7% spike in uncompensated care demand that will affect their ability to keep their doors open."
"As of August 2026, 20 Maine healthcare providers are at-risk, announced cuts, are closing, or have closed," the group added.
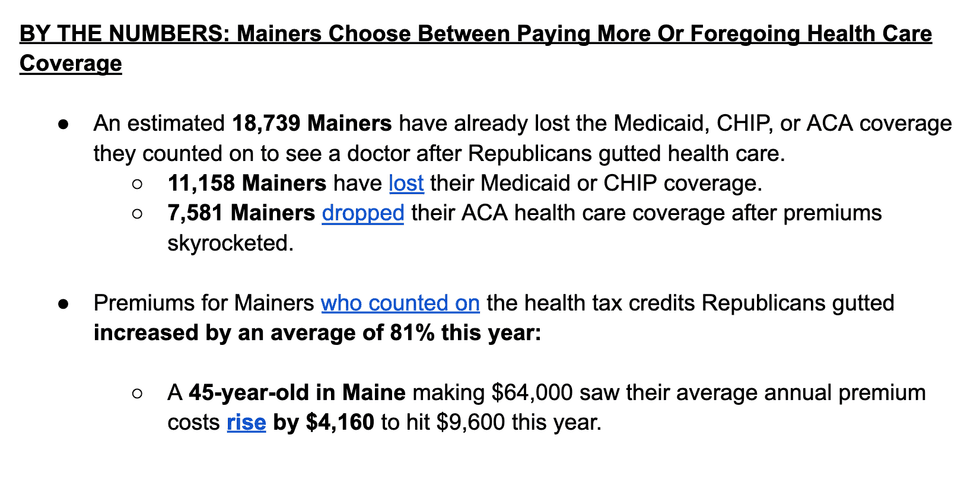
More than 25,600 Alaskans have lost health coverage under the Republican budget law and premiums have surged by an average of 346% this year, according to Protect Our Care's fact sheets.
US Sen. Dan Sullivan (R-Alaska), who along with Collins is seen as one of the most vulnerable Republicans this election cycle, voted for the more than $900 billion in Medicaid cuts.
"From Alaska to Florida, these people are our neighbors, our parents, our kids, and they’re sick of paying the price for Republicans’ greed," Woodhouse said on Tuesday. "They deserve better, and in November they will demand it at the ballot box.”