5
#000000
#FFFFFF
To donate by check, phone, or other method, see our More Ways to Give page.
Daily news & progressive opinion—funded by the people, not the corporations—delivered straight to your inbox.
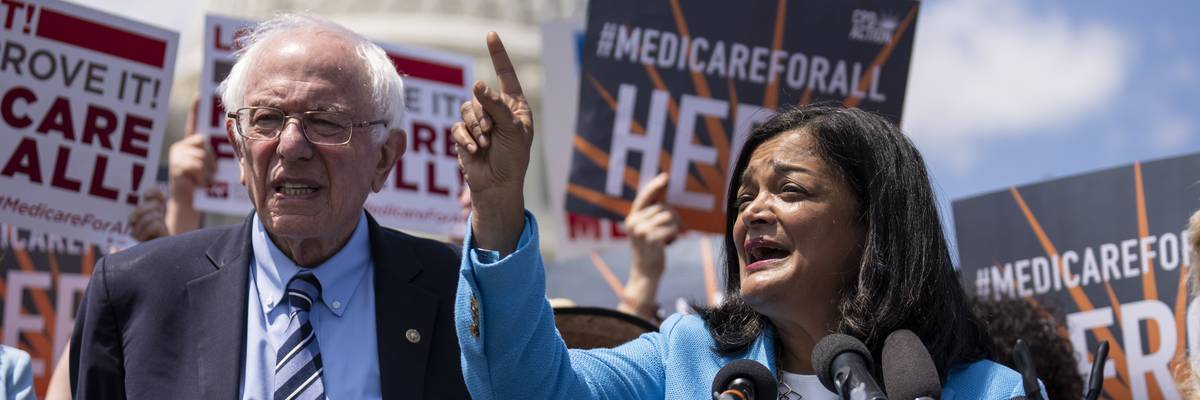
Sen. Bernie Sanders (I-Vt) looks on as Rep. Pramila Jayapal (D-Wash.) during a news conference to announce the re-introduction of the Medicare For All Act of 2023, outside the U.S. Capitol May 17, 2023 in Washington, DC. On the House side, the proposal will have 112 co-sponsors from the House Democratic caucus, more than they have ever had at the introduction of the bill.
Because Improved Medicare for All is such a winning policy, powerful forces opposed to it must rely on fear, division, and lies to prevail. Knowing their lines of attack will help assure our ultimate victory.
To move forward toward Improved Medicare for All, the supporters must be strategic, persistent, and patient. In addition, supporters must be ready to neutralize the counterattacks from the opponents who are rich, formidable, and devious.
Because Improved Medicare for All is such a winning policy, those powerful forces must rely on fear, division, and lies to prevail. They succeed not by convincing us with reason but rather by tricking us into working against our own best interests. President Roosevelt exposed this dynamic in 1936, as he fought for our Social Security. “It is an old strategy of tyrants to delude their victims into fighting their battles for them,” he warned us.
As a first step, it is imperative to recognize who the “tyrants” are. They include some of the largest, most profitable, multinational corporations in the world, the ones that profit so enormously from the current healthcare system. The “tyrants” also include billionaires who are determined to amass more and pay as little as possible toward the common good. These wealthiest people in the history of the world have no intention of paying their fair share.
In addition to them are their surrogates, some of whom may be disguised. They include those we elect, who are supposed to work for us, but want to keep open and flowing the pipeline to campaign contributions and other benefits the wealthy “tyrants” provide. Some of the surrogate-politicians are obvious. They seek unabashedly and openly to rip away even the inadequate health insurance Americans currently have. They are the ones working toward the further privatization of Medicare.
Some, though, whether they rationalize to themselves or simply are confused and don’t realize that they are doing the bidding of the “tyrants,” claim that they support national health insurance, but argue that it’s not practical. They not only don’t fight for Improved Medicare for All, they muddy the debate and even may subtly throw up roadblocks to its enactment. Another group of surrogates are some journalists and editors who often work for publications owned by the billionaire “tyrants.”
All of these surrogates are highly influential and may convince your family, friends, neighbors, and even you, that Improved Medicare for All is something to be feared – notwithstanding that virtually every other industrialized country has their own form of Improved Medicare for All, systems that cover their entire populations less expensively and have better health outcomes than the United States.
To understand how the “tyrants” and their surrogates delude their victims – the rest of us – into fighting among ourselves and working against our own best interests, it is essential to keep in mind the Powell memo of the 1970s and the Gingrich memo of the 1990s. Underlying both was the retreat from honest policy discussions and instead a power struggle backed by huge amounts of money. Their views represent a small minority, so their method of prevailing is to divide and instill fear.
Supporters must be hyper-vigilant against the monied interests tricking the American people into succumbing to this “old strategy of tyrants.” Those who want to enact Improved Medicare for All must understand the facts and the ploys.
Perhaps the oldest line of attack is simply to call Improved Medicare for All “socialized medicine.” The phrase “socialized medicine” has become the proverbial four-letter curse word to many Americans. Opponents are quick to label any health proposals they don’t like, “socialized medicine.”
One might think that the phrase, “socialized medicine,” has lost its bite. After all, the Soviet Union and the Cold War officially ended decades ago, on December 25, 1991, when the hammer-and-sickle flag last flew over the Kremlin in Moscow. The phrase appears to be effective because it invokes irrational fears of change and the unknown. It is, in essence, shorthand for something that is foreign, dangerous, and scary.
Because the charge plays on people’s fears, the lie that Improved Medicare for All is socialized medicine can’t be defeated with logical explanations. Rather, it makes sense to address quickly the epithet but then immediately pivot to what people like about Improved Medicare for All.
Another powerful lie is that Improved Medicare for All will hurt the people who are currently on Medicare. This is a deeply cynical stratagem, but, unfortunately, it is effective. Because seniors and people with disabilities, on average, have the greatest health care needs, they are, as a group, particularly susceptible to this kind of fearmongering. It is therefore imperative that advocates of Improved Medicare for All have a honed, well thought-through strategy aimed toward current Medicare beneficiaries and those close to turning age 65.
In fact, those currently on Medicare will be much better off with Improved Medicare for All. Their benefit package will be more comprehensive, their out-of-pocket costs will drop to zero, and the security of the program will increase, since everyone will have a personal stake in seeing it expanded and not cut.
Moreover, it will be simpler. Gone will be all premiums, deductibles, co-insurance, and co-pays. Those who today have their Medicare premiums automatically deducted from their Social Security benefits will see those benefits increased. Gone also will be the impossible tasks of deciding what prescription drug plan best covers one’s future needs, whether to go with so-called Medicare Advantage, and if so, which one, and if not, whether to buy a supplemental plan and if so, which one.
It is important to recognize that there is a thread of a concern that vaguely connects the “socialized medicine” charge and the accusation that current beneficiaries will be hurt. Today, Medicare and Social Security are accurately recognized as earned benefits. To qualify for those benefits, a worker has to have worked and contributed for long enough to be insured, in the case of Social Security and Medicare’s Part A hospital insurance. Workers contribute to the cost of those benefits throughout their working lives, underscoring their earned-benefit nature. Supporters of Improved Medicare for All can and must deal with the sense of current beneficiaries that they earned their Medicare, while it will just be “given” to everyone else, when it is expanded.
The reality is that unlike retirement income, which replaces earned wages, everyone needs health care. The nation has some means-tested programs, like Temporary Assistance for Needy Families, which are designed to alleviate poverty, some earned-benefit programs, like Social Security, which are designed to replace earnings, and some universal benefits, like public parks, freeways, and the police, which are designed to safeguard and improve the lives of all of us.
As much as the American image is one of individualism, virtually all Americans recognize the importance of some communal activities. While Americans differ about whether there should be a military draft, virtually everyone accepts the need for a military paid for collectively. Similarly, public libraries, local fire departments, and public roads and bridges are all seen as public goods appropriately paid for with tax dollars and available to all of us.
With health insurance so tied to employment, it often has to be earned – but it shouldn’t. Having guaranteed high-quality health insurance with no out-ot-pocket costs as a benefit to all Americans is what it means for it to be a right, not a privilege.
It is important to be especially aware of how this subtle attack on national health insurance paid through taxes is perceived not just by Medicare beneficiaries but also by union members. Many unionized workers have been successful in negotiating for excellent health insurance. To obtain the plans, the workers generally had to trade away higher cash compensation. Consequently, it is not surprising that they are reluctant to give them up.
The message to the workers is that, as excellent as their current plans may be, the new coverage will be even better. Union members should be assured, and the Improved Medicare for All legislation should require, that their employers continue to pay what they have been paying in total compensation. Instead of paying that compensation in the form of health care premiums to health insurance corporations, though, the payments will now be in the form of increased current compensation and non-health care benefits.
A related fear tactic to the claim that current Medicare beneficiaries, union members, and others will be worse off is for opponents to tell you that you will lose your current health insurance. The implication is that either it won’t be replaced or the replacement will leave you worse off. It is effective not because people so love their current health insurance, but because the fear of losing even the inadequate coverage you may now have is literally a matter of life and death. It is a classic deployment of people’s aversion to loss. It is another tactic aimed at division.
As a related matter, opponents seek to play on the fear of loss by emphasizing that people will lose choice. Importantly, the choice that people will lose is trivial – to which insurance company their hard-earned money goes.
Most Americans will gain choice in what matters: who their health providers will be. Indeed, Improved Medicare for All will improve people’s ability to get the care they want from the doctors and hospitals they want anywhere in the country and ensure continuity of care.
Another way that opponents have sought to turn people away from Improved Medicare for All is with a sleight of hand. They emphasize that federal expenses will increase resulting in increased taxes or borrowing. Indeed, this same sleight of hand is used to convince too many Americans that today’s Medicare is unaffordable. By focusing on the money going into the government’s coffers and out to providers, opponents seek to convince Americans that Improved Medicare for All will produce “big government,” which is somehow scary and negative.
The truth is that in the modern world, no one is truly opposed to “big” government; it is just that progressives and conservatives have different views of what a big, powerful, modern government should do. Conservatives want a big government military and a big brother government, limiting what women can do with their own bodies, what schools can teach, what museums can display, what kind of gender-affirming care parents, doctors, and children can utilize, how immigrants should be treated, and so on. Progressives want all of us, collectively through government, to ensure every American has economic security in the form of expanded Social Security, health care as a matter of right, a living wage, and more.
If the nation once again has a truly progressive tax system, we can have much greater economic security for everyone. If multimillionaires, billionaires, and multinational corporations were simply required to pay their fair share and the revenue raised dedicated to Improved Medicare for All, that would be sufficient to cover the costs. Even if some revenue were to come from working families, though, their out-of-pocket costs would be considerably lower than today. It is just that the payments would go to the federal government, rather than UnitedHealthcare and other private health insurance companies.
At base, the issue isn’t big government versus small government or increased taxes. It is one of values. That is what supporters should emphasize. Not only will Improved Medicare for All cost less, the money will be spent more productively. Instead of wasteful time spent on the phone appealing denials and seeking pre-authorizations, most of the monies will be spent on paying doctors, hospitals, and other providers.
Another fear tactic is to selectively point to other countries and claim that the quality of care will decrease, at least for the very wealthy, and people will have to wait for inordinately long periods of time for basic care. Importantly, both parts of that framing are untrue. They are both well-cultivated myths. As many people know, the United States is worse than its counterparts in terms of health care outcomes and affordability of care. What is generally not known is that it measures around average or worse in terms of timeliness of care.
The truth is that wait times to see a primary care doctor or a specialist vary among countries that have mandatory, universal health care plans, as do wait times for urgent and non-urgent surgery. Some are longer wait times than patients experience in the United States and some are shorter. Indeed, doctors in other countries are much better at providing care after hours and even make house calls!
What is of legitimate concern are the people who will lose their jobs as our health care system becomes more efficient. That is an issue that proponents of Improved Medicare for All must address. Indeed, proponents not only recognize this responsibility; they include, in their Improved Medicare for All proposals, ways to address it.
Every single job loss is generally a destabilizing event for working families. it is essential that the workers who are displaced are properly treated. Systematic, planned, and consistent outreach should be made to those workers.
One way to alleviate the many fears and concerns that Roosevelt’s “tyrants” are sure to exploit is through an incremental approach, so that Americans will see that they are no worse off, and, in fact, are better off, when Medicare is improved and expanded. Ideally, the incremental steps should combine expansion to additional groups with improvements for current beneficiaries. In that way, current beneficiaries will see clearly the advantage to them. As more Americans receive the benefit, along with an active campaign to assure people additional expansions will leave them better off, not worse off, this natural fear of change should dissipate, and support for expansion increase, like a snowball rolling down a snowy hill.
As long as the final destination remains in mind and is continually invoked, steps that are truly along the way help, but supporters must be wary of disguised alternatives and incremental steps that will hurt the effort. Numerous polls reveal that Medicare for All is an extremely popular idea. Unfortunately, those who oppose the idea of Improved Medicare for All or simply don’t completely understand its striking advantages, have put forward proposals that are decidedly not Improved Medicare for All and, indeed, would not lead us to our desired destination.
The far right is not the only source of these similar-sounding alternatives. Some Democrats have advanced these confusing alternatives. They do so, while seeking to persuade supporters that Improved Medicare for All is not practical, not politically realistic. The assertion that Improved Medicare for All is somehow not able to be enacted may be simply a misguided perception, or it may be a product of the work of the monied interests. In either event, it is destructive and must be taken seriously.
At base, advocates must be wary of steps that appear to point in the right direction, but carry significant risks of derailing the effort. Anything short of a universal, mandated Improved Medicare for All has to be clearly understood as simply a stop along the way, not the final destination. That final destination cannot have an opt in or an opt out, nor include a competing commercial alternative. Just as Social Security is and indeed must be mandatory and virtually universal to work so well, Improved Medicare for All must be, also.
An important lesson from history is that even when victory is achieved, particularly if the victory is incremental, the fight continues. It should be celebrated. It should not be seen, though, that the fight is over. The enactments of Social Security and Medicare were hard fought. Once they were well established and popular, the monied interests sought to prevent their expansion and undermine them from within. Indeed, there are many who today seek to undermine public education with vouchers and charter schools, illustrating that these fights never end.
Dear Common Dreams reader, It’s been nearly 30 years since I co-founded Common Dreams with my late wife, Lina Newhouser. We had the radical notion that journalism should serve the public good, not corporate profits. It was clear to us from the outset what it would take to build such a project. No paid advertisements. No corporate sponsors. No millionaire publisher telling us what to think or do. Many people said we wouldn't last a year, but we proved those doubters wrong. Together with a tremendous team of journalists and dedicated staff, we built an independent media outlet free from the constraints of profits and corporate control. Our mission has always been simple: To inform. To inspire. To ignite change for the common good. Building Common Dreams was not easy. Our survival was never guaranteed. When you take on the most powerful forces—Wall Street greed, fossil fuel industry destruction, Big Tech lobbyists, and uber-rich oligarchs who have spent billions upon billions rigging the economy and democracy in their favor—the only bulwark you have is supporters who believe in your work. But here’s the urgent message from me today. It's never been this bad out there. And it's never been this hard to keep us going. At the very moment Common Dreams is most needed, the threats we face are intensifying. We need your support now more than ever. We don't accept corporate advertising and never will. We don't have a paywall because we don't think people should be blocked from critical news based on their ability to pay. Everything we do is funded by the donations of readers like you. When everyone does the little they can afford, we are strong. But if that support retreats or dries up, so do we. Will you donate now to make sure Common Dreams not only survives but thrives? —Craig Brown, Co-founder |
Nancy Altman is president of Social Security Works and chair of the Strengthen Social Security Coalition. She is co-author of two books and author of three, including her most recent, The Road to Medicare for All: A Call to Action.
To move forward toward Improved Medicare for All, the supporters must be strategic, persistent, and patient. In addition, supporters must be ready to neutralize the counterattacks from the opponents who are rich, formidable, and devious.
Because Improved Medicare for All is such a winning policy, those powerful forces must rely on fear, division, and lies to prevail. They succeed not by convincing us with reason but rather by tricking us into working against our own best interests. President Roosevelt exposed this dynamic in 1936, as he fought for our Social Security. “It is an old strategy of tyrants to delude their victims into fighting their battles for them,” he warned us.
As a first step, it is imperative to recognize who the “tyrants” are. They include some of the largest, most profitable, multinational corporations in the world, the ones that profit so enormously from the current healthcare system. The “tyrants” also include billionaires who are determined to amass more and pay as little as possible toward the common good. These wealthiest people in the history of the world have no intention of paying their fair share.
In addition to them are their surrogates, some of whom may be disguised. They include those we elect, who are supposed to work for us, but want to keep open and flowing the pipeline to campaign contributions and other benefits the wealthy “tyrants” provide. Some of the surrogate-politicians are obvious. They seek unabashedly and openly to rip away even the inadequate health insurance Americans currently have. They are the ones working toward the further privatization of Medicare.
Some, though, whether they rationalize to themselves or simply are confused and don’t realize that they are doing the bidding of the “tyrants,” claim that they support national health insurance, but argue that it’s not practical. They not only don’t fight for Improved Medicare for All, they muddy the debate and even may subtly throw up roadblocks to its enactment. Another group of surrogates are some journalists and editors who often work for publications owned by the billionaire “tyrants.”
All of these surrogates are highly influential and may convince your family, friends, neighbors, and even you, that Improved Medicare for All is something to be feared – notwithstanding that virtually every other industrialized country has their own form of Improved Medicare for All, systems that cover their entire populations less expensively and have better health outcomes than the United States.
To understand how the “tyrants” and their surrogates delude their victims – the rest of us – into fighting among ourselves and working against our own best interests, it is essential to keep in mind the Powell memo of the 1970s and the Gingrich memo of the 1990s. Underlying both was the retreat from honest policy discussions and instead a power struggle backed by huge amounts of money. Their views represent a small minority, so their method of prevailing is to divide and instill fear.
Supporters must be hyper-vigilant against the monied interests tricking the American people into succumbing to this “old strategy of tyrants.” Those who want to enact Improved Medicare for All must understand the facts and the ploys.
Perhaps the oldest line of attack is simply to call Improved Medicare for All “socialized medicine.” The phrase “socialized medicine” has become the proverbial four-letter curse word to many Americans. Opponents are quick to label any health proposals they don’t like, “socialized medicine.”
One might think that the phrase, “socialized medicine,” has lost its bite. After all, the Soviet Union and the Cold War officially ended decades ago, on December 25, 1991, when the hammer-and-sickle flag last flew over the Kremlin in Moscow. The phrase appears to be effective because it invokes irrational fears of change and the unknown. It is, in essence, shorthand for something that is foreign, dangerous, and scary.
Because the charge plays on people’s fears, the lie that Improved Medicare for All is socialized medicine can’t be defeated with logical explanations. Rather, it makes sense to address quickly the epithet but then immediately pivot to what people like about Improved Medicare for All.
Another powerful lie is that Improved Medicare for All will hurt the people who are currently on Medicare. This is a deeply cynical stratagem, but, unfortunately, it is effective. Because seniors and people with disabilities, on average, have the greatest health care needs, they are, as a group, particularly susceptible to this kind of fearmongering. It is therefore imperative that advocates of Improved Medicare for All have a honed, well thought-through strategy aimed toward current Medicare beneficiaries and those close to turning age 65.
In fact, those currently on Medicare will be much better off with Improved Medicare for All. Their benefit package will be more comprehensive, their out-of-pocket costs will drop to zero, and the security of the program will increase, since everyone will have a personal stake in seeing it expanded and not cut.
Moreover, it will be simpler. Gone will be all premiums, deductibles, co-insurance, and co-pays. Those who today have their Medicare premiums automatically deducted from their Social Security benefits will see those benefits increased. Gone also will be the impossible tasks of deciding what prescription drug plan best covers one’s future needs, whether to go with so-called Medicare Advantage, and if so, which one, and if not, whether to buy a supplemental plan and if so, which one.
It is important to recognize that there is a thread of a concern that vaguely connects the “socialized medicine” charge and the accusation that current beneficiaries will be hurt. Today, Medicare and Social Security are accurately recognized as earned benefits. To qualify for those benefits, a worker has to have worked and contributed for long enough to be insured, in the case of Social Security and Medicare’s Part A hospital insurance. Workers contribute to the cost of those benefits throughout their working lives, underscoring their earned-benefit nature. Supporters of Improved Medicare for All can and must deal with the sense of current beneficiaries that they earned their Medicare, while it will just be “given” to everyone else, when it is expanded.
The reality is that unlike retirement income, which replaces earned wages, everyone needs health care. The nation has some means-tested programs, like Temporary Assistance for Needy Families, which are designed to alleviate poverty, some earned-benefit programs, like Social Security, which are designed to replace earnings, and some universal benefits, like public parks, freeways, and the police, which are designed to safeguard and improve the lives of all of us.
As much as the American image is one of individualism, virtually all Americans recognize the importance of some communal activities. While Americans differ about whether there should be a military draft, virtually everyone accepts the need for a military paid for collectively. Similarly, public libraries, local fire departments, and public roads and bridges are all seen as public goods appropriately paid for with tax dollars and available to all of us.
With health insurance so tied to employment, it often has to be earned – but it shouldn’t. Having guaranteed high-quality health insurance with no out-ot-pocket costs as a benefit to all Americans is what it means for it to be a right, not a privilege.
It is important to be especially aware of how this subtle attack on national health insurance paid through taxes is perceived not just by Medicare beneficiaries but also by union members. Many unionized workers have been successful in negotiating for excellent health insurance. To obtain the plans, the workers generally had to trade away higher cash compensation. Consequently, it is not surprising that they are reluctant to give them up.
The message to the workers is that, as excellent as their current plans may be, the new coverage will be even better. Union members should be assured, and the Improved Medicare for All legislation should require, that their employers continue to pay what they have been paying in total compensation. Instead of paying that compensation in the form of health care premiums to health insurance corporations, though, the payments will now be in the form of increased current compensation and non-health care benefits.
A related fear tactic to the claim that current Medicare beneficiaries, union members, and others will be worse off is for opponents to tell you that you will lose your current health insurance. The implication is that either it won’t be replaced or the replacement will leave you worse off. It is effective not because people so love their current health insurance, but because the fear of losing even the inadequate coverage you may now have is literally a matter of life and death. It is a classic deployment of people’s aversion to loss. It is another tactic aimed at division.
As a related matter, opponents seek to play on the fear of loss by emphasizing that people will lose choice. Importantly, the choice that people will lose is trivial – to which insurance company their hard-earned money goes.
Most Americans will gain choice in what matters: who their health providers will be. Indeed, Improved Medicare for All will improve people’s ability to get the care they want from the doctors and hospitals they want anywhere in the country and ensure continuity of care.
Another way that opponents have sought to turn people away from Improved Medicare for All is with a sleight of hand. They emphasize that federal expenses will increase resulting in increased taxes or borrowing. Indeed, this same sleight of hand is used to convince too many Americans that today’s Medicare is unaffordable. By focusing on the money going into the government’s coffers and out to providers, opponents seek to convince Americans that Improved Medicare for All will produce “big government,” which is somehow scary and negative.
The truth is that in the modern world, no one is truly opposed to “big” government; it is just that progressives and conservatives have different views of what a big, powerful, modern government should do. Conservatives want a big government military and a big brother government, limiting what women can do with their own bodies, what schools can teach, what museums can display, what kind of gender-affirming care parents, doctors, and children can utilize, how immigrants should be treated, and so on. Progressives want all of us, collectively through government, to ensure every American has economic security in the form of expanded Social Security, health care as a matter of right, a living wage, and more.
If the nation once again has a truly progressive tax system, we can have much greater economic security for everyone. If multimillionaires, billionaires, and multinational corporations were simply required to pay their fair share and the revenue raised dedicated to Improved Medicare for All, that would be sufficient to cover the costs. Even if some revenue were to come from working families, though, their out-of-pocket costs would be considerably lower than today. It is just that the payments would go to the federal government, rather than UnitedHealthcare and other private health insurance companies.
At base, the issue isn’t big government versus small government or increased taxes. It is one of values. That is what supporters should emphasize. Not only will Improved Medicare for All cost less, the money will be spent more productively. Instead of wasteful time spent on the phone appealing denials and seeking pre-authorizations, most of the monies will be spent on paying doctors, hospitals, and other providers.
Another fear tactic is to selectively point to other countries and claim that the quality of care will decrease, at least for the very wealthy, and people will have to wait for inordinately long periods of time for basic care. Importantly, both parts of that framing are untrue. They are both well-cultivated myths. As many people know, the United States is worse than its counterparts in terms of health care outcomes and affordability of care. What is generally not known is that it measures around average or worse in terms of timeliness of care.
The truth is that wait times to see a primary care doctor or a specialist vary among countries that have mandatory, universal health care plans, as do wait times for urgent and non-urgent surgery. Some are longer wait times than patients experience in the United States and some are shorter. Indeed, doctors in other countries are much better at providing care after hours and even make house calls!
What is of legitimate concern are the people who will lose their jobs as our health care system becomes more efficient. That is an issue that proponents of Improved Medicare for All must address. Indeed, proponents not only recognize this responsibility; they include, in their Improved Medicare for All proposals, ways to address it.
Every single job loss is generally a destabilizing event for working families. it is essential that the workers who are displaced are properly treated. Systematic, planned, and consistent outreach should be made to those workers.
One way to alleviate the many fears and concerns that Roosevelt’s “tyrants” are sure to exploit is through an incremental approach, so that Americans will see that they are no worse off, and, in fact, are better off, when Medicare is improved and expanded. Ideally, the incremental steps should combine expansion to additional groups with improvements for current beneficiaries. In that way, current beneficiaries will see clearly the advantage to them. As more Americans receive the benefit, along with an active campaign to assure people additional expansions will leave them better off, not worse off, this natural fear of change should dissipate, and support for expansion increase, like a snowball rolling down a snowy hill.
As long as the final destination remains in mind and is continually invoked, steps that are truly along the way help, but supporters must be wary of disguised alternatives and incremental steps that will hurt the effort. Numerous polls reveal that Medicare for All is an extremely popular idea. Unfortunately, those who oppose the idea of Improved Medicare for All or simply don’t completely understand its striking advantages, have put forward proposals that are decidedly not Improved Medicare for All and, indeed, would not lead us to our desired destination.
The far right is not the only source of these similar-sounding alternatives. Some Democrats have advanced these confusing alternatives. They do so, while seeking to persuade supporters that Improved Medicare for All is not practical, not politically realistic. The assertion that Improved Medicare for All is somehow not able to be enacted may be simply a misguided perception, or it may be a product of the work of the monied interests. In either event, it is destructive and must be taken seriously.
At base, advocates must be wary of steps that appear to point in the right direction, but carry significant risks of derailing the effort. Anything short of a universal, mandated Improved Medicare for All has to be clearly understood as simply a stop along the way, not the final destination. That final destination cannot have an opt in or an opt out, nor include a competing commercial alternative. Just as Social Security is and indeed must be mandatory and virtually universal to work so well, Improved Medicare for All must be, also.
An important lesson from history is that even when victory is achieved, particularly if the victory is incremental, the fight continues. It should be celebrated. It should not be seen, though, that the fight is over. The enactments of Social Security and Medicare were hard fought. Once they were well established and popular, the monied interests sought to prevent their expansion and undermine them from within. Indeed, there are many who today seek to undermine public education with vouchers and charter schools, illustrating that these fights never end.
Nancy Altman is president of Social Security Works and chair of the Strengthen Social Security Coalition. She is co-author of two books and author of three, including her most recent, The Road to Medicare for All: A Call to Action.
To move forward toward Improved Medicare for All, the supporters must be strategic, persistent, and patient. In addition, supporters must be ready to neutralize the counterattacks from the opponents who are rich, formidable, and devious.
Because Improved Medicare for All is such a winning policy, those powerful forces must rely on fear, division, and lies to prevail. They succeed not by convincing us with reason but rather by tricking us into working against our own best interests. President Roosevelt exposed this dynamic in 1936, as he fought for our Social Security. “It is an old strategy of tyrants to delude their victims into fighting their battles for them,” he warned us.
As a first step, it is imperative to recognize who the “tyrants” are. They include some of the largest, most profitable, multinational corporations in the world, the ones that profit so enormously from the current healthcare system. The “tyrants” also include billionaires who are determined to amass more and pay as little as possible toward the common good. These wealthiest people in the history of the world have no intention of paying their fair share.
In addition to them are their surrogates, some of whom may be disguised. They include those we elect, who are supposed to work for us, but want to keep open and flowing the pipeline to campaign contributions and other benefits the wealthy “tyrants” provide. Some of the surrogate-politicians are obvious. They seek unabashedly and openly to rip away even the inadequate health insurance Americans currently have. They are the ones working toward the further privatization of Medicare.
Some, though, whether they rationalize to themselves or simply are confused and don’t realize that they are doing the bidding of the “tyrants,” claim that they support national health insurance, but argue that it’s not practical. They not only don’t fight for Improved Medicare for All, they muddy the debate and even may subtly throw up roadblocks to its enactment. Another group of surrogates are some journalists and editors who often work for publications owned by the billionaire “tyrants.”
All of these surrogates are highly influential and may convince your family, friends, neighbors, and even you, that Improved Medicare for All is something to be feared – notwithstanding that virtually every other industrialized country has their own form of Improved Medicare for All, systems that cover their entire populations less expensively and have better health outcomes than the United States.
To understand how the “tyrants” and their surrogates delude their victims – the rest of us – into fighting among ourselves and working against our own best interests, it is essential to keep in mind the Powell memo of the 1970s and the Gingrich memo of the 1990s. Underlying both was the retreat from honest policy discussions and instead a power struggle backed by huge amounts of money. Their views represent a small minority, so their method of prevailing is to divide and instill fear.
Supporters must be hyper-vigilant against the monied interests tricking the American people into succumbing to this “old strategy of tyrants.” Those who want to enact Improved Medicare for All must understand the facts and the ploys.
Perhaps the oldest line of attack is simply to call Improved Medicare for All “socialized medicine.” The phrase “socialized medicine” has become the proverbial four-letter curse word to many Americans. Opponents are quick to label any health proposals they don’t like, “socialized medicine.”
One might think that the phrase, “socialized medicine,” has lost its bite. After all, the Soviet Union and the Cold War officially ended decades ago, on December 25, 1991, when the hammer-and-sickle flag last flew over the Kremlin in Moscow. The phrase appears to be effective because it invokes irrational fears of change and the unknown. It is, in essence, shorthand for something that is foreign, dangerous, and scary.
Because the charge plays on people’s fears, the lie that Improved Medicare for All is socialized medicine can’t be defeated with logical explanations. Rather, it makes sense to address quickly the epithet but then immediately pivot to what people like about Improved Medicare for All.
Another powerful lie is that Improved Medicare for All will hurt the people who are currently on Medicare. This is a deeply cynical stratagem, but, unfortunately, it is effective. Because seniors and people with disabilities, on average, have the greatest health care needs, they are, as a group, particularly susceptible to this kind of fearmongering. It is therefore imperative that advocates of Improved Medicare for All have a honed, well thought-through strategy aimed toward current Medicare beneficiaries and those close to turning age 65.
In fact, those currently on Medicare will be much better off with Improved Medicare for All. Their benefit package will be more comprehensive, their out-of-pocket costs will drop to zero, and the security of the program will increase, since everyone will have a personal stake in seeing it expanded and not cut.
Moreover, it will be simpler. Gone will be all premiums, deductibles, co-insurance, and co-pays. Those who today have their Medicare premiums automatically deducted from their Social Security benefits will see those benefits increased. Gone also will be the impossible tasks of deciding what prescription drug plan best covers one’s future needs, whether to go with so-called Medicare Advantage, and if so, which one, and if not, whether to buy a supplemental plan and if so, which one.
It is important to recognize that there is a thread of a concern that vaguely connects the “socialized medicine” charge and the accusation that current beneficiaries will be hurt. Today, Medicare and Social Security are accurately recognized as earned benefits. To qualify for those benefits, a worker has to have worked and contributed for long enough to be insured, in the case of Social Security and Medicare’s Part A hospital insurance. Workers contribute to the cost of those benefits throughout their working lives, underscoring their earned-benefit nature. Supporters of Improved Medicare for All can and must deal with the sense of current beneficiaries that they earned their Medicare, while it will just be “given” to everyone else, when it is expanded.
The reality is that unlike retirement income, which replaces earned wages, everyone needs health care. The nation has some means-tested programs, like Temporary Assistance for Needy Families, which are designed to alleviate poverty, some earned-benefit programs, like Social Security, which are designed to replace earnings, and some universal benefits, like public parks, freeways, and the police, which are designed to safeguard and improve the lives of all of us.
As much as the American image is one of individualism, virtually all Americans recognize the importance of some communal activities. While Americans differ about whether there should be a military draft, virtually everyone accepts the need for a military paid for collectively. Similarly, public libraries, local fire departments, and public roads and bridges are all seen as public goods appropriately paid for with tax dollars and available to all of us.
With health insurance so tied to employment, it often has to be earned – but it shouldn’t. Having guaranteed high-quality health insurance with no out-ot-pocket costs as a benefit to all Americans is what it means for it to be a right, not a privilege.
It is important to be especially aware of how this subtle attack on national health insurance paid through taxes is perceived not just by Medicare beneficiaries but also by union members. Many unionized workers have been successful in negotiating for excellent health insurance. To obtain the plans, the workers generally had to trade away higher cash compensation. Consequently, it is not surprising that they are reluctant to give them up.
The message to the workers is that, as excellent as their current plans may be, the new coverage will be even better. Union members should be assured, and the Improved Medicare for All legislation should require, that their employers continue to pay what they have been paying in total compensation. Instead of paying that compensation in the form of health care premiums to health insurance corporations, though, the payments will now be in the form of increased current compensation and non-health care benefits.
A related fear tactic to the claim that current Medicare beneficiaries, union members, and others will be worse off is for opponents to tell you that you will lose your current health insurance. The implication is that either it won’t be replaced or the replacement will leave you worse off. It is effective not because people so love their current health insurance, but because the fear of losing even the inadequate coverage you may now have is literally a matter of life and death. It is a classic deployment of people’s aversion to loss. It is another tactic aimed at division.
As a related matter, opponents seek to play on the fear of loss by emphasizing that people will lose choice. Importantly, the choice that people will lose is trivial – to which insurance company their hard-earned money goes.
Most Americans will gain choice in what matters: who their health providers will be. Indeed, Improved Medicare for All will improve people’s ability to get the care they want from the doctors and hospitals they want anywhere in the country and ensure continuity of care.
Another way that opponents have sought to turn people away from Improved Medicare for All is with a sleight of hand. They emphasize that federal expenses will increase resulting in increased taxes or borrowing. Indeed, this same sleight of hand is used to convince too many Americans that today’s Medicare is unaffordable. By focusing on the money going into the government’s coffers and out to providers, opponents seek to convince Americans that Improved Medicare for All will produce “big government,” which is somehow scary and negative.
The truth is that in the modern world, no one is truly opposed to “big” government; it is just that progressives and conservatives have different views of what a big, powerful, modern government should do. Conservatives want a big government military and a big brother government, limiting what women can do with their own bodies, what schools can teach, what museums can display, what kind of gender-affirming care parents, doctors, and children can utilize, how immigrants should be treated, and so on. Progressives want all of us, collectively through government, to ensure every American has economic security in the form of expanded Social Security, health care as a matter of right, a living wage, and more.
If the nation once again has a truly progressive tax system, we can have much greater economic security for everyone. If multimillionaires, billionaires, and multinational corporations were simply required to pay their fair share and the revenue raised dedicated to Improved Medicare for All, that would be sufficient to cover the costs. Even if some revenue were to come from working families, though, their out-of-pocket costs would be considerably lower than today. It is just that the payments would go to the federal government, rather than UnitedHealthcare and other private health insurance companies.
At base, the issue isn’t big government versus small government or increased taxes. It is one of values. That is what supporters should emphasize. Not only will Improved Medicare for All cost less, the money will be spent more productively. Instead of wasteful time spent on the phone appealing denials and seeking pre-authorizations, most of the monies will be spent on paying doctors, hospitals, and other providers.
Another fear tactic is to selectively point to other countries and claim that the quality of care will decrease, at least for the very wealthy, and people will have to wait for inordinately long periods of time for basic care. Importantly, both parts of that framing are untrue. They are both well-cultivated myths. As many people know, the United States is worse than its counterparts in terms of health care outcomes and affordability of care. What is generally not known is that it measures around average or worse in terms of timeliness of care.
The truth is that wait times to see a primary care doctor or a specialist vary among countries that have mandatory, universal health care plans, as do wait times for urgent and non-urgent surgery. Some are longer wait times than patients experience in the United States and some are shorter. Indeed, doctors in other countries are much better at providing care after hours and even make house calls!
What is of legitimate concern are the people who will lose their jobs as our health care system becomes more efficient. That is an issue that proponents of Improved Medicare for All must address. Indeed, proponents not only recognize this responsibility; they include, in their Improved Medicare for All proposals, ways to address it.
Every single job loss is generally a destabilizing event for working families. it is essential that the workers who are displaced are properly treated. Systematic, planned, and consistent outreach should be made to those workers.
One way to alleviate the many fears and concerns that Roosevelt’s “tyrants” are sure to exploit is through an incremental approach, so that Americans will see that they are no worse off, and, in fact, are better off, when Medicare is improved and expanded. Ideally, the incremental steps should combine expansion to additional groups with improvements for current beneficiaries. In that way, current beneficiaries will see clearly the advantage to them. As more Americans receive the benefit, along with an active campaign to assure people additional expansions will leave them better off, not worse off, this natural fear of change should dissipate, and support for expansion increase, like a snowball rolling down a snowy hill.
As long as the final destination remains in mind and is continually invoked, steps that are truly along the way help, but supporters must be wary of disguised alternatives and incremental steps that will hurt the effort. Numerous polls reveal that Medicare for All is an extremely popular idea. Unfortunately, those who oppose the idea of Improved Medicare for All or simply don’t completely understand its striking advantages, have put forward proposals that are decidedly not Improved Medicare for All and, indeed, would not lead us to our desired destination.
The far right is not the only source of these similar-sounding alternatives. Some Democrats have advanced these confusing alternatives. They do so, while seeking to persuade supporters that Improved Medicare for All is not practical, not politically realistic. The assertion that Improved Medicare for All is somehow not able to be enacted may be simply a misguided perception, or it may be a product of the work of the monied interests. In either event, it is destructive and must be taken seriously.
At base, advocates must be wary of steps that appear to point in the right direction, but carry significant risks of derailing the effort. Anything short of a universal, mandated Improved Medicare for All has to be clearly understood as simply a stop along the way, not the final destination. That final destination cannot have an opt in or an opt out, nor include a competing commercial alternative. Just as Social Security is and indeed must be mandatory and virtually universal to work so well, Improved Medicare for All must be, also.
An important lesson from history is that even when victory is achieved, particularly if the victory is incremental, the fight continues. It should be celebrated. It should not be seen, though, that the fight is over. The enactments of Social Security and Medicare were hard fought. Once they were well established and popular, the monied interests sought to prevent their expansion and undermine them from within. Indeed, there are many who today seek to undermine public education with vouchers and charter schools, illustrating that these fights never end.