

SUBSCRIBE TO OUR FREE NEWSLETTER
Daily news & progressive opinion—funded by the people, not the corporations—delivered straight to your inbox.
5
#000000
#FFFFFF
To donate by check, phone, or other method, see our More Ways to Give page.
Daily news & progressive opinion—funded by the people, not the corporations—delivered straight to your inbox.

Gen Z women refuse to have our bodies and reproductive agency pressed into service in some futile attempt to balance the books of a chaotic economy.
Gen Z women like me are having fewer babies. That shouldn’t be a surprise—with prices for everything going up, our parents’ steady jobs, white picket fences, and retirement packages feel much less attainable for us.
But the government wants to make us change that. In the US and elsewhere, anxiety over aging populations and shrinking labor forces has been woven into the claim that women in their 20s somehow owe the economy more babies.
Our fertility becomes an asset on a balance sheet to counteract falling birth and marriage rates. Women who choose to put our own lives and interests first get branded “childless cat ladies,” as Vice President JD Vance once called us. But if being in no rush to get pregnant means I’m a selfish cat lady, I’m proud to claim the title.
A better path would be to pass policies that support women who do want to have children but can’t afford it: like paid leave, affordable and reliable childcare, and making family planning and perinatal care accessible for all.
Half of all pregnancies worldwide are unintended, reflecting a broad pattern where women’s power to choose when and whether to have children is compromised, contested, and unequally distributed. Pro-natalism—a set of policies or attitudes designed to pressure women into having more children—is part of that pattern. It stigmatizes those who resist as selfish.
To me at age 21, being “selfish” means finishing my degree before even thinking about starting a family. It means refusing to take on a dependent while still outgrowing my own dependency. It means treating my body and my reproductive choices as my own rather than as a budget line item or labor input. It means doing what I have to do to navigate an economy where costs are skyrocketing.
Today, the average cost of raising a child from birth to 18, including daycare ($17,264 annually for five years), food ($4,208 a year), and transportation ($4,422 a year) comes to over $300,000 and counting.
Under the so-called Big Beautiful Bill, Congress created $1,000 “Trump Accounts” as a “baby bonus” to encourage women to have more babies. But in that case, they’re missing a few zeroes. And since money is kept in a stock market index fund until the babies turn 18, it won’t help parents with the high costs of raising kids.
So much for the carrot. Then there’s the stick—attacking reproductive healthcare so pregnancy is harder to avoid. For starters, abortion bans have spread across the country since the Trump administration’s hand-picked Supreme Court justices overthrew Roe v. Wade.
Meanwhile, the Trump administration has removed federal funding for teen pregnancy prevention programs, opting for abstinence-focused, fertility-tracking curricula instead—which studies show result in higher teen pregnancy rates.
The administration has also undermined Title X, the only federal program providing family planning services to low-income people. Historically there has been bipartisan support for it. But last year, funding for 22 Title X grants was frozen, putting 834,000 people at risk of losing access to birth control, cancer screenings, STI testing, and more. That funding was later restored thanks to a lawsuit, but next year’s budget proposes to eliminate it again.
A better path would be to pass policies that support women who do want to have children but can’t afford it: like paid leave, affordable and reliable childcare, and making family planning and perinatal care accessible for all. These should be consistently funded, reliable commitments that don’t get yanked back when administrations change.
Rejecting these attacks doesn’t mean I don’t want a family or child someday. It means the choice belongs to me and to every woman, on her own terms. Gen Z women refuse to have our bodies and reproductive agency pressed into service in some futile attempt to balance the books of a chaotic economy.
No recycled misogynist insults about cat ladies, no performative “baby bonus” bribes, no motherhood medals are going to override my own power to choose when or whether I have a child. If that makes me selfish, it’s a label I accept happily.

At long last, the nation’s healthcare plan will guarantee that not only is everyone covered for care, free at the point of service, but that there is a place within reasonable distance to find that care.
After a century of providing healthcare to this rural, southeast Michigan community, Sturgis Hospital closed in June with only 70 hours warning.
The hospital was not on the at-risk-of-closing list that had been published by Sen. Ed Markey (D-Mass.) a year earlier.
Over 300 Sturgis Hospital employees are scrambling to find work. Registered nurse Beth Kelley, who had worked at Sturgis for 32 years, described the meeting room as filled with “shock” and “devastation” when management announced that the hospital was closing.
Nationwide more than 700 rural hospitals are at risk of closing, over half at immediate risk within the next two to three years. The 700 hospitals represent about one-third of all rural hospitals.
The termination of care at Sturgis Hospital overloads the city’s emergency medical services. Director of public safety Ryan Banaszak said, “What was once approximately a 2-mile transport for patients has now become closer to 25 miles, which takes ambulance personnel and equipment out of service for a much longer period of time.”
The impact is great on Michigan Medicaid patients, who cannot use the closest hospital because it is across the state line in Indiana.
“Rural hospital closures lead to significant increases in mortality, and birthing outcomes and obstetric care suffer following closures,” said Michael Shepherd, University of Michigan health policy researcher. The risk increases with every additional mile for emergencies like strokes and heart attacks.
A few weeks later the rural River District Hospital in St. Clair County northeast of Detroit announced the closing of its inpatient and emergency services. Four more rural Michigan hospitals—in Mt. Pleasant, Carson City, Ontonagon, and Dowagiac—are in danger of closing with the upcoming Medicaid cuts.
Rural Americans live sicker and die younger than those in urban areas. Life expectancy is about three years shorter in rural communities. When a rural hospital closes, the mortality rate rises by 5.9%. Rural hospital closures increase mortality for emergencies such as heart attacks and strokes by about 10%.
“There are two kinds of Americans: those who live 12 minutes from an emergency department and those who live 72,” writes Ayla Ellison who grew up in Carmi in southern Illinois. “Whether you survive a heart attack, deliver a healthy baby, or die from something entirely treatable increasingly depends not on the severity of your illness, but on the distance to the nearest hospital,” she continues. She explores the consequences of rural hospitals folding in a country where no one is responsible for assuring help is close enough for a chance at life. The hospital in Carmi closed 20 years ago. Nine more Illinois hospitals are at risk of closure, most of them in southern Illinois.
Other states are worse off. In Mississippi, 51% of the rural hospitals are at risk of closing; in Alabama, 52%; in Arkansas, 68%.
Dr. Kenneth Williams battled for decades to sustain the hospital (Alliance Healthcare System) in Holly Springs, Mississippi. Rapid expansion of Medicare Advantage plans reduced reimbursement and increased denials of payment to the hospital. In 2023, facing financial desperation, the hospital converted to Rural Emergency Hospital status, a federal program designed to stabilize struggling rural hospitals. The Center for Medicare and Medicaid Services (CMS) later removed that designation, leaving the hospital again fighting to stay open.
Nationwide more than 700 rural hospitals are at risk of closing, over half at immediate risk within the next two to three years. The 700 hospitals represent about one-third of all rural hospitals. That report was prior to the passage of HR 1, the “One Big Beautiful Bill” that slashes $1 trillion from Medicaid. The crisis escalates from grim to disastrous with the looming Medicaid cuts.
Federal efforts to save our rural hospitals have been pitifully inadequate in the face of the towering problem.
Critical Access Hospitals, created by Congress in 1997, allow small rural hospitals to receive cost-based Medicare reimbursement. The plan was designed to stem the tide of closures.
Between 2010 and 2025, 152 rural hospitals closed. Of these, 52 were Critical Access Hospitals.
In 2021 Congress created Rural Emergency Hospitals. This designation provides for enhanced Medicare payments allowing rural hospitals to continue with outpatient and emergency services only, instead of closing.
In 2023, Sturgis hospital was “saved” by conversion to a Rural Emergency Hospital, delaying its shutdown by three years.
Neither these nor any other federal plans are big enough or thorough enough to work.
CMS Director Mehmet Oz recently visited Kentucky, home of 35 rural at-risk hospitals. He touted the $50 billion in Rural Health Transformation Funds as the solution. The assertion is absurd.
At best, Kentucky will get $1 billion from the rural transformation funds as it loses $21 billion in Medicaid funds. Not even a wizard can turn that into a winner.
As Boston University professor Alan Sager notes, no US entity is responsible for sustaining or building or financing hospitals based on community need.
“The whole Appalachian area has been abandoned, but its hospitals should be funded and improved, as a necessity of life—like the post office,” says Dare Cima, who is from southeastern Kentucky.
With passage of H R 3069, Improved Medicare for All, finally, the nation will take responsibility for assuring that rural areas have adequate facilities. Hospitals will be paid quarterly, in advance, with a global budget that provides operating expenses.
The allocation to hospitals ensures proper staffing with safe nurse-to-patient ratios and optimal staffing for physicians and other healthcare workers. Physician salaries can be included in the global budget. Adjustments to the operating budget will be made “to decrease healthcare disparities in rural or medically underserved areas.”
Special projects funds will be used to end discrimination based on race or other underserved categories including geography. Funds will be allocated for construction of new facilities where needed. At long last, the nation’s healthcare plan will guarantee that not only is everyone covered for care, free at the point of service, but that there is a place within reasonable distance to find that care.
The late Dr. Ewell Scott, Medical Staff president of St. Clair Regional Medical Center in Morehead in the mountains of eastern Kentucky, predicted that if current policy continued, it was just a matter of time until all of Kentucky’s hospitals east of I-75 would be closed.
Sadly, that prediction is breathtakingly close as 16 of east Kentucky’s hospitals in the 5th Congressional District, including Dr. Scott’s beloved St. Clair hospital, are on the list of those endangered with closing by the passage of HR 1.
But Dr. Scott was fighting for a different future. He persuaded the City of Morehead to pass a resolution supporting Improved Medicare for All, a national single-payer plan that would cover us all and fund the hospitals.
Dr. Scott urged all who would listen to tell their congresspersons: “We know the solution. You’ve got to have the guts to stand up and do it.”

"Over half the provisions of the Big Ugly Bill have already gone into effect, and the negative results are already devastating."
Independent healthcare analyst Charles Gaba on Thursday published a detailed report estimating that up to 10 million people living in the US have lost their healthcare coverage since the start of President Donald Trump's second term.
In his analysis, Gaba brought together the most recent enrollment data for Medicaid, the Children's Health Insurance Program (CHIP), Medicare, and the Affordable Care Act (ACA).
Breaking things down by program, Gaba estimated there are 5.9 million fewer people enrolled in Medicaid and CHIP, as well as at least 4.5 million fewer people enrolled in the ACA, since Trump returned to power in January 2025.
These losses in coverage are somewhat mitigated by Medicare, whose enrollment has increased by around 1.6 million people during Trump's second term.
Losing access to these programs doesn't mean that the people were on them have gotten well paying jobs and are receiving insurance from their employer, Gaba wrote. Given that the unemployment rate has risen during Trump's second term, Gaba suggested it is highly unlikely that there are now more people who get employer-sponsored coverage now than in January 2025.
Depending on a number of variables, Gaba concluded, somewhere between 8.8 million to 10.3 million fewer people now have healthcare coverage.
Adjusting for population growth, Gaba added, "you get a grand total of between 10.27 million and 11.75 million more Americans not enrolled in a public healthcare coverage program as of May 2026 than in were as of January 2025."
The healthcare analyst noted that "this isn't quite the same thing as counting how many lost coverage, but not having healthcare sucks regardless of how you slice it."
He also pointed out that the lost in healthcare coverage all came before the Medicaid work requirements from the GOP's 2025 budget law are put into effect.
"Over half the provisions of the Big Ugly Bill have already gone into effect," wrote Gaba, "and the negative results are already devastating."
Gaba's analysis was published just days after the Georgetown University Center for Children and Families released a report estimating that nearly 2.5 million children in the US have lost access to Medicaid or CHIP during Trump's second term.
Trump and congressional Republicans have taken a number of actions that have made healthcare less affordable.
First, they cut spending on Medicaid by an estimated $900 billion over a 10-year period when they enacted the One Big Beautiful Bill Act in 2025. The Congressional Budget Office projects these cuts will leave more than 10 million fewer people enrolled in the program by 2034.
GOP lawmakers last year also refused to extend enhanced subsidies for insurance plans purchased through the ACA, even as insurers raised premiums on those plans by an average of 26% this year, according to an analysis published by KFF.
According to Wednesday reporting by Politico, hospitals are sounding the alarm about new regulations being proposed by the Centers for Medicare and Medicaid Services that they say would cost hundreds of billions of dollars in lost revenue.
"If the rules are finalized and they lose hundreds of billions on top of Congress’ funding cuts," Politico reported, "hospitals say they’ll be forced to reduce services, lay off workers, consolidate operations or shutter entirely."
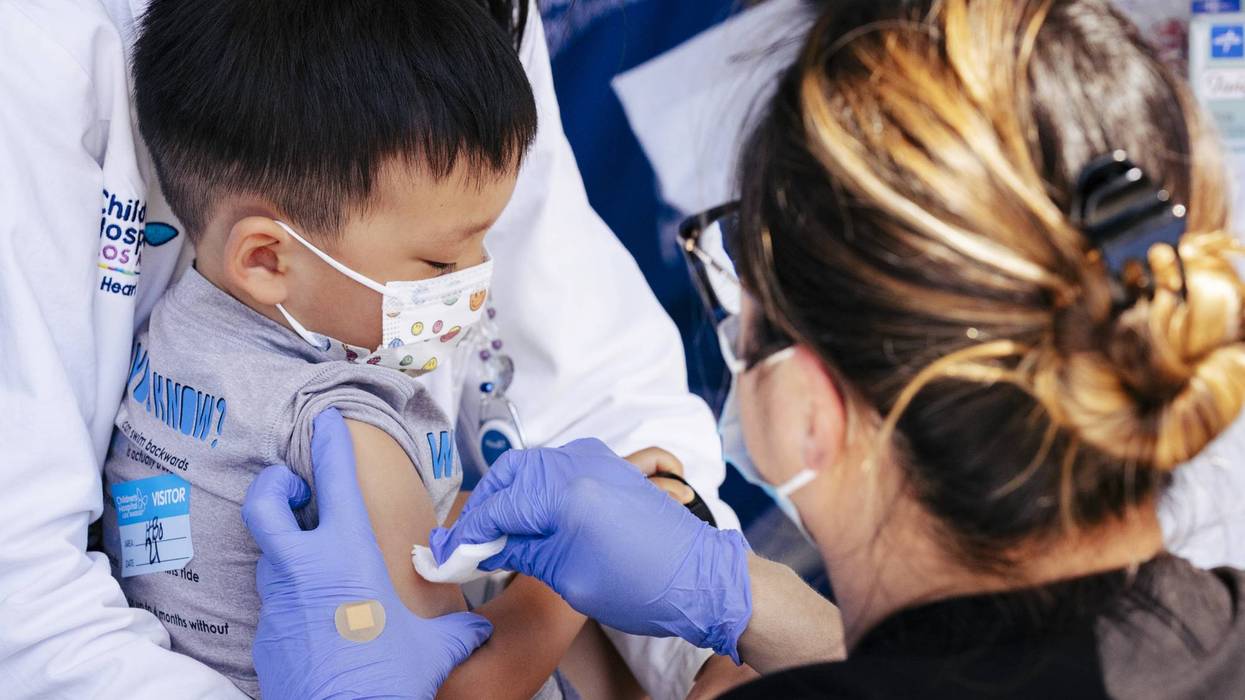
The drop in children covered by Medicaid comes before the most draconian changes to the program made by Republicans' 2025 budget law are set to take effect next year.
Nearly 2.5 million children living in the US have lost access to Medicaid or Children's Health Insurance Program coverage during President Donald Trump's second term, according to data published on Monday by the Georgetown University Center for Children and Families.
In total, five states have seen children's enrollment in Medicaid and CHIP fall by 10% or higher since January 2025, with Indiana seeing a drop in enrollment in those programs of more than 23%.
Colorado and Hawaii were the only two states to see a net increase in children in Medicaid or CHIP over that same period.
Joan Alker, executive director of the Center for Children and Families, described the drop in children enrolled in the programs as "a lot," and said it was important to track because "when Medicaid child enrollment declines, the number of uninsured kids typically goes up."
President Donald Trump and congressional Republicans cut spending on Medicaid by an estimated $900 billion over a 10-year period when they enacted the One Big Beautiful Bill Act in 2025. The Congressional Budget Office projects these cuts will leave more than 10 million fewer people enrolled in the program by 2034.
One way the GOP budget law is projected to kick people off Medicaid has been to add extra administrative burdens and paperwork for people who qualify for the program.
As explained by a Scripps News report published last week, Medicaid starting next year will make beneficiaries enroll twice a year instead of just once, while also mandating adults who "earn above a typical income cutoff and do not have children... work or volunteer at least 80 hours a month, or enroll in school."
Eileen Appelbaum, co-director of the Center for Economic and Policy Research, told Scripps News that this will result in many people not receiving Medicaid coverage despite being qualified for it.
"The best guesses from the experts are that two-thirds of the people that will be disqualified will actually be eligible, but they just couldn't handle the paperwork," Appelbaum explained.
In an op-ed published by Stat on Monday, Brown University epidemiologists Abdullah Shihipar and Brandon DL Marshall highlighted how getting out of the new Medicaid work requirements by proving yourself "medically frail" is shaping up to be a "nightmare scenario for millions of Americans."
"Let’s say you are undergoing cancer treatment, but you don’t have the right paperwork for your renewal," Shihipar and Marshall wrote. "As a result, you’re disenrolled from Medicaid. You desperately try to fix the mistake, but you are faced with long wait times and no answers, so you cease treatment altogether... Paperwork here is not merely an annoyance, it is a matter of life or death for millions with Medicaid coverage."

"These cuts are not filtering out 'waste, fraud, and abuse'... they are parents deciding between paying the electric bill and putting food on the table, or skipping meals."
Participation in the Supplemental Nutrition Assistance Program is now at its lowest point in 17 years thanks to cuts made in the Republican Party's One Big Beautiful Bill Act.
The Center for Budget and Policy Priorities (CBPP) on Wednesday published the latest update to its series of reports tracking the impact of SNAP cuts, and it found that there are roughly 5 million fewer people participating in SNAP thanks in large part to the cuts made in the 2025 GOP budget law.
Since the law's passage, enrollment in SNAP has decreased in every US state except Alaska.
While enrollment has fallen by an average of 12% across the US over the last year, eight states have seen participation plummet by 20% or higher. Arizona has seen the largest overall drop in participation, with 45% fewer people enrolled in the program over the last year.
"The declines started before the harmful 2025 Republican reconciliation law’s enactment, suggesting factors at play in addition to that law," CBPP explained. "But in almost all states, declines in SNAP participation accelerated after the 2025 Republican reconciliation law, and we expect that trend to continue."
CBPP also projected participation would fall even further in the next year given that the biggest changes made to SNAP funding won't fully kick in until 2027, when "most states will have to pay between 5% and 15% of SNAP benefit costs, totaling hundreds of millions of dollars a year in many states."
"The amount a state will have to pay will be based on current error rates, factoring in errors that states are making today," CBPP emphasized. "The magnitude of the cost shift and the urgency surrounding error rates may incentivize states to take drastic measures to reduce their payment error rates quickly and cut program costs, even if it means delaying or improperly denying benefits to eligible people."
CBPP's latest report on SNAP cuts comes after ParentsTogether Action released a survey of SNAP beneficiaries on Tuesday finding that two-thirds of families who rely on the program have already seen benefits decrease over the last year.
The survey shows 75% of SNAP beneficiaries also report that affording food is one of their biggest economic challenges, echoing earlier surveys showing that buying groceries has become a major source of stress for Americans overall.
SNAP recipients described to ParentsTogether Action how the SNAP cuts have impacted their finances.
"They took over $120 off our SNAP," said a Kansas mother named Brandi. "We have a hard time keeping up with bills. I get [Supplemental Security Income], and that is my only income for my daughter and myself."
An Oregon woman named Amanda, meanwhile, described seeing her benefits cut by more than half after she found a job.
"We were receiving $400 a month, but after I reported my new income and reapplied, our benefits dropped to just under $200," she said. "We also didn’t receive any benefits for one month during the process."
Ailen Arreaza, executive director of ParentsTogether Action, said the SNAP cuts are forcing families to make an "impossible choice" on whether to prioritize paying for food, healthcare, or their utility bills.
"These cuts are not filtering out 'waste, fraud, and abuse' like the administration would like us to believe," Arreaza explained, "they are parents deciding between paying the electric bill and putting food on the table, or skipping meals so their kids can eat. Families should not have to make these choices."
The Centers for Medicare and Medicaid Services' implementation of the One Big Beautiful Bill narrows the very protections Congress included to prevent vulnerable people nationwide from losing the health coverage they need.
The biggest Medicaid fight today isn't happening in Congress—it's happening inside the Centers for Medicare and Medicaid Services.
Now, a year after H.R. 1’s passage (the 2025 federal reconciliation bill enacting significant cuts and changes to Medicaid), CMS’ recently issued interim final rule (IFR) implementing the law’s work-reporting requirements in the program narrows the very protections Congress included to prevent vulnerable people nationwide from losing the health coverage they need.
The Congressional Budget Office previously estimated that more than 5 million people will lose Medicaid coverage because of these requirements. Already a conservative estimate as other organizations estimated over 10 million people are at risk of losing coverage, the number will surely be higher given CMS' IFR goes beyond the statutory language of the law.
The clearest example of this is the IFR's treatment of the medically frail exemption.
If the goal is really healthier communities and greater workforce participation, making it harder for medically vulnerable people to keep their health insurance is exactly the wrong approach.
Congress recognized that people living with complex medical conditions, disabilities, and chronic illnesses, including substance use disorder (SUD), should be protected from burdensome work-reporting requirements. As such, H.R. 1 specifically includes “medically frail” individuals among those exempt from the new requirements.
Yet CMS has added a new hurdle, putting millions of eligible Americans at dire risk of losing access to essential healthcare.
Under the IFR, people with SUD and other qualifying health conditions must also demonstrate that their condition "significantly impairs" their ability to satisfy the requirement before they can qualify for the exemption. This additional standard does not appear in the statute and will inevitably reduce the number of people who can secure the exemption.
For people living with SUD, the consequences could be profound.
While SUD is a chronic but treatable medical condition, pervasive stigma and discriminatory barriers have led to fewer than 1 in 5 people who need treatment actually receiving it. Amid persistent addiction and overdose crises, we should be making it easier for people to access the services and supports they need to become and stay well, not erecting additional barriers to lifesaving care.
Moreover, while CMS' rule relies heavily on Medicaid claims data and provider documentation to identify individuals who qualify as medically frail, the administration’s approach overlooks the reality that many people with SUD have never entered treatment due to the above-mentioned stigma and discrimination. Requiring additional documentation will not "motivate" people to seek care, as CMS suggests. Instead, it creates yet another barrier for people who are already among the hardest to reach.
When people are deprived of Medicaid access, their ability to engage in preventive care, behavioral health services, medications, and treatment that keep chronic conditions under control is also lost. And it doesn’t take a rocket scientist to understand how untreated health conditions can not just impede a person’s capacity to work but quickly lead to costly emergency services.
These are not only personal tragedies—they are costly public policy failures.
Taking away health coverage does not eliminate health needs. It just shifts and raises costs while undermining public health and safety. Access to healthcare is precisely what enables many people to work, care for their families, and be productive community members, so why are we erecting so many barriers?
If the goal is really healthier communities and greater workforce participation, making it harder for medically vulnerable people to keep their health insurance is exactly the wrong approach.
Last month, both our organizations, along with many other leading advocates nationwide, explicitly articulated these concerns and submitted comments urging the agency to reverse course and faithfully reinforce the protections Congress included in the law. While CMS' public comment period on the IFR is now closed, all those who share the same perspective can still take action by calling their members of Congress to share their concerns about the impact of H.R. 1 and specifically, how the administration is planning to implement the law.
A year after H.R. 1’s passage, the question is no longer simply about what Congress enacted—it is whether the regulations that make the law real will preserve purposeful protections or quietly erode them through administrative action.

"This is an extraordinary concentration of tax benefits among some of the biggest and most profitable companies in the world," said an ITEP senior fellow.
As with the GOP's 2017 tax legislation, experts warned that big businesses and ultrarich individuals would benefit from President Donald Trump signing the One Big Beautiful Bill Act last year, while everyday Americans would suffer, and a Monday analysis identifies some of the companies now paying billions of dollars less in taxes.
The Institute on Taxation and Economic Policy (ITEP) "has tracked $204 billion in federal tax breaks disclosed by publicly traded US companies so far for 2025," the report says. "But those benefits were not spread evenly across the corporate sector: Six companies alone accounted for $83 billion of them."
The publication points out that "the stunning size of the federal income tax breaks corporations claimed this year dwarfs past corporate tax breaks, themselves sizeable. Microsoft received $18.7 billion in federal income tax breaks, a record high for single-year federal tax breaks for one publicly traded company. Alphabet claimed a staggering $18.4 billion, and Amazon walked away with $17.4 billion in tax breaks. Meta received $13.7 billion, JPMorgan Chase received $8.3 billion, and Nvidia received $6.8 billion."
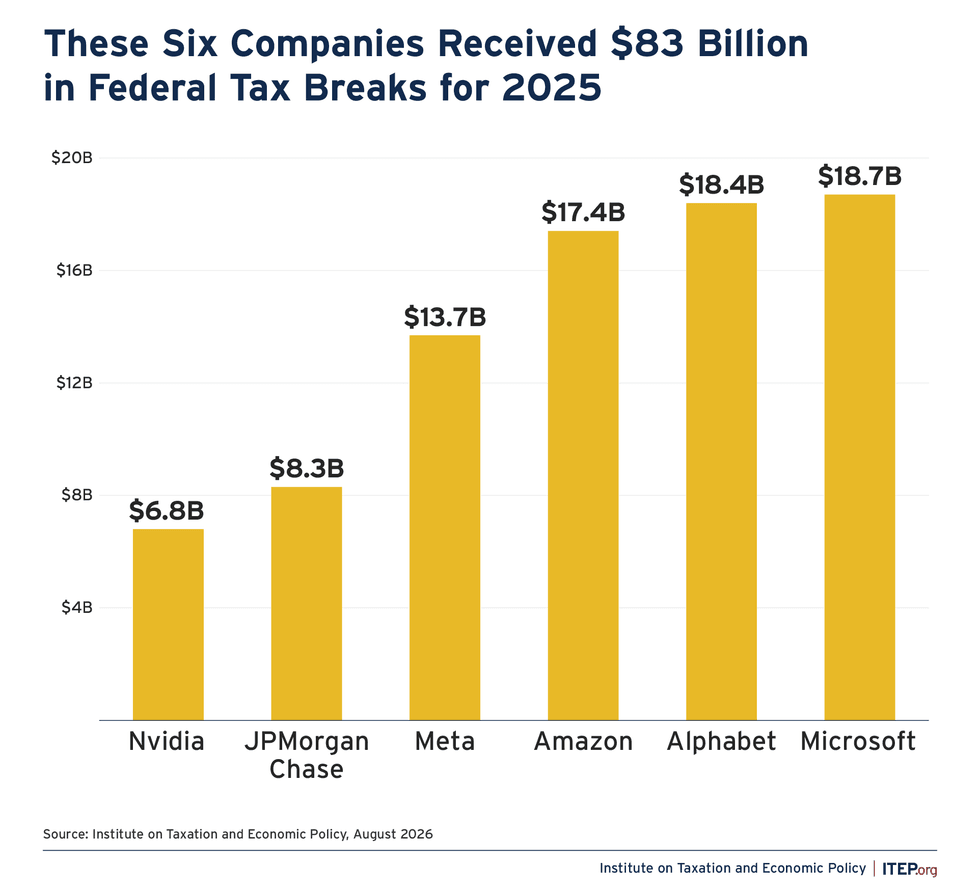
To put that $83 billion into context, the report highlights that it "represents nearly 18%, or almost $1 out of ever $5, of total federal corporation tax collections according to the Congressional Budget Office." It also "exceeds the entire annual discretionary budget of the US Department of Education," which Trump is notably aiming to eliminate as part of a broader mission to gut the federal government in his second term.
"This is an extraordinary concentration of tax benefits among some of the biggest and most profitable companies in the world," report co-author and ITEP senior fellow Matthew Gardner said in a statement. "When six companies can collect tax breaks equal to nearly one-fifth of what the federal government raises from the corporate income tax altogether, policymakers should be asking whether these provisions are serving the public interest or simply rewarding companies that are already enormously profitable and politically influential."
Gardner and his co-author, ITEP intern Sarah Buttikofer, emphasized that the top four firms featured in their analysis are tech giants: "Microsoft, Alphabet, Amazon, and Meta collectively received $68 billion in federal income tax breaks—which represents roughly 33% of the overall total."
"These figures show what Americans intuitively know: Corporate profits and economic power are increasingly concentrated among a relatively small number of extremely large companies," the pair wrote. "The presence of half a dozen tech CEOs at Donald Trump's January 2025 inauguration was a stark reminder that the economic leverage these companies are gaining is being translated into political power as well. That makes the tax treatment of these companies especially important."
Amazon founder Jeff Bezos and Meta CEO Mark Zuckerberg were among the Big Tech executives with prime seating at the inauguration. There was also the world's richest man, Elon Musk, who went on to help Trump rip apart the federal workforce as the de facto leader of the so-called Department of Government Efficiency.
To put these enormous tax breaks in context, the largest single-year tax break we've documented for any corporation before 2025 was J.P. Morgan’s $5.2 billion haul in 2024.itep.org/six-companie...
[image or embed]
— ITEP (@itep.org) August 14, 2026 at 12:18 PM
Musk leads various businesses, including Tesla, which was among 88 companies that paid no federal income tax last year, despite making almost $5.7 billion, according to an April analysis from ITEP. The others range from airlines and banks to energy, entertainment, and tech companies, such as Citigroup, Edison International, Palantir, United, and Walt Disney.
Meanwhile, near the end of last year, as Trump dismissed affordability concerns, an Associated Press-NORC Center for Public Affairs Research poll found that only 31% of voters approved of Trump's handling of the economy, the survey's lowest figure for his two terms.
Then, a January analysis by Democrats on the Joint Economic Committee revealed that the average American family paid $1,625 in higher costs last year as his policies drove up prices.
That was followed by a February warning from the Economic Policy Institute that Trump's economic agenda "will make ordinary families reliably poorer in the future." EPI's chief economist, Josh Bivens, pointed to the president's anti-labor policies, cuts to federal spending and jobs, mass deportation efforts, and tariffs—as well as the OBBBA, which gave tax breaks to the rich while stripping healthcare and food assistance from Americans in need.
With the US now enduring the consequences of Trump's war of choice on Iran, inflation remains high. Americans are struggling with the cost of gasoline, groceries, healthcare, housing, and more. After the latest figures were released last week, Alex Jacquez, a former Obama administration official who is now senior vice president of policy and advocacy at Groundwork Collaborative, said that "prices started climbing again in July, and Trump's catastrophic mismanagement of our economy means more spikes in the months ahead."
Under a new policy the administration is defending in court, low-income people with cancer, HIV, Parkinson's, and other life-threatening illnesses must prove they're too sick to work or risk losing their health insurance.
A federal judge on Thursday denied a request by more than two dozen Democratic states to halt a Trump administration policy announced last month that would require Medicaid recipients with terminal diseases to prove they are too sick to work in order to be exempt from new work requirements that go into effect this coming January.
While introducing over $1 trillion in tax cuts for the wealthiest 1% of Americans, last year's massive GOP tax and budget bill also imposed new 80-hour-per-month work requirements that states must implement for Medicaid expansion recipients, who receive government-subsidized insurance coverage at or below 138% of the poverty line.
The law specified that those who are “medically frail or otherwise have special medical needs” are excluded from the work requirement, and specifically listed people with a “serious or complex medical condition.” But it remained unclear what exact conditions met these criteria.
Earlier this month, the Centers for Medicare and Medicaid Services (CMS) introduced a new rule stating that even if a person receives a terminal diagnosis for a disease like cancer, HIV/AIDS, or Parkinson's, that is still not enough for them to be exempt from the work requirements.
Beginning on January 1, 2028, it says they must also demonstrate to states that their condition “significantly impairs” their ability to meet the work requirement.
Democratic attorneys general in 25 states and the District of Columbia filed a preliminary injunction over the rule late last month, arguing that CMS had rewritten the law to introduce a vague and needlessly restrictive new hurdle that vulnerable people will face in obtaining desperately needed care.
“This is one of those cases where it’s really hard to overstate how dire the consequences could be,” North Carolina’s Democratic attorney general, Jeff Jackson, told Politico. “You’re going to have 50 states doing 50 different things, and we’re all going to have to create a whole new bureaucracy... You are talking about a lot more paperwork, more evaluations, more doctor visits, and a lot more work for doctors themselves.”
The Democratic AGs argued that implementation of the work requirements should be paused because they lacked the staff or capacity to meet the timeline set by CMS, which requires states to communicate to enrollees how they'll be affected by the changes by the end of August.
US District Judge Richard Stearns on Thursday denied their initial request to immediately halt the implementation of the requirements while the lawsuit proceeds, but also did not rule on the lawsuit's merits, which are scheduled to be decided before the requirements go into effect on January 1.
Several medical associations, including the American Medical Association, the American College of Physicians, and the American Academy of Pediatrics, have come out against the rule, arguing that it would have dire consequences for people who suffer from severe illness.
"One of the most significant factors in whether someone survives a cancer diagnosis is whether they have health insurance coverage," Lisa Lacasse, president of the American Cancer Society Cancer Action Network, explained in June.
"The new restrictions link the definition of medical frailty to a person’s ability to work," she continued. "This would mean cancer patients and survivors who are suffering from debilitating side effects of the disease or treatment would have to officially prove they can’t work, in a process that is likely to be difficult and take a long time."
The nonpartisan Congressional Budget Office has projected that over the coming decade, changes to healthcare policy introduced by Republicans would increase the number of uninsured Americans by about 11.8 million.
Around 5.7 million of them are projected to be Medicaid recipients who either do not meet the 80-hour work requirement or are otherwise eligible but tripped up by one of the newly imposed paperwork hurdles.
Taya Graham and Stephen Janis argued earlier this week in a piece for The Real News Network that eligible people losing coverage is not an unfortunate side effect of the law, but a goal of the Republicans who passed it, who sought a way to thin the ranks of those who qualify for Medicaid without having to take the politically unpopular step of actually clawing back benefits.
They wrote that what has happened to recipients of the Supplemental Nutrition Assistance Program (SNAP) illustrates how burdensome these new requirements may become.
As The New York Times reported earlier this month, in Arizona, 440,000 people have already been dropped from SNAP after it enacted a formidable regime of paperwork for low-income recipients to prove eligibility, including requiring some people with panhandling income to obtain documentation from donors who drop them a buck on the street.
"If this is what people receiving SNAP benefits have been subjected to," Graham and Janis wrote, "imagine what’s going to happen to people who will need to navigate the new [Medicaid] requirements while struggling with a debilitating or terminal illness."
Medical issues are a leading cause of bankruptcy in the US. According to one study, over 4 in 10 cancer patients over 50 had depleted all their assets within two years of diagnosis.
Melanie D’Arrigo, a campaigner for single-payer healthcare in New York, said that President Donald Trump "cut cancer research, cut healthcare,” and with new Medicaid restrictions, “wants to make sure Americans continue to work as they go broke battling cancer.”

Trump and his allies in Congress have not so much dismantled these programs yet as chipped away at them; if this movement continues unabated, we may be left with the crumbling foundations of programs that were built to last.
There is reason to celebrate Medicare and Medicaid turning 61 years old. Both highly successful programs were signed into law by President Lyndon B. Johnson on July 30, 1965 as a cornerstone of his Great Society agenda. But this year, our celebration is tempered by grave concern over the future of both programs under the Trump regime.
Let’s compare the words of the two presidents:
LBJ:
No longer will older Americans be denied the healing miracle of modern medicine. No longer will illness crush and destroy the savings that they have so carefully put away over a lifetime. No longer will young families see their own incomes, and their own hopes, eaten away simply because they are carrying out their deep moral obligations to their parents.
It’s not possible for us to take care of… Medicaid, Medicare, all these individual things. They can do it on a state basis. You can’t do it on a federal. We have to take care of one thing: military protection. We have to guard the country.
The comparison speaks volumes. One is a leader who understood that the federal government has a crucial role in the protecting the health and well-being of our most vulnerable citizens—including the poor, disabled, and the elderly. The other is a president who claims to support Medicare and then says that the federal government can’t afford it because of his illegal war in Iran. So much for supporting Medicare.
But this goes deeper than Trump’s rhetoric. The Medicare program, like Social Security, is at a pivotal point in its history. The Part A hospital) trust fund must be fortified so that it doesn’t run dry in the 2030s. (There are reasonable solutions that Congress could enact without hurting seniors.) So far, though, we have heard no constructive ideas from Trump.
More urgently, though, the Trump administration is actively undermining the "traditional Medicare" program that LBJ signed into law. The administration has begun a pilot program to use AI bots to determine whether traditional Medicare patients will be covered for procedures their doctors have ordered. This appears to be an attempt to cut costs by erecting obstacles to medically necessary care—with decisions made by bots instead of human beings.
It could be the first step in a scheme to corrupt traditional Medicare and make it more like the privatized Medicare Advantage program run by for-profit insurers, which is a glorified HMO (with frequent denials of care, limited provider networks, and surprise out-of-pocket costs for beneficiaries). Unfortunately, thanks to deceptive but pervasive advertising, Medicare Advantage has now captured more than 51% of the market, leaving traditional Medicare with a shrinking share of enrollees.
The problem is that Medicare Advantage (MA) puts profits over patients. Participating insurance companies have been overbilling the federal government by billions of dollars a year. Ironically, this privatized program was supposed to save taxpayers money. Instead, Medicare Advantage plans cost the government an average of 14% more per patient than traditional Medicare. That translates into an additional $76 billion in federal spending this year alone.
The bottom line: Medicare Advantage puts taxpayers’ money into the hands of large insurance companies while failing to deliver superior or more cost-effective care. It is fair to say that this is not what LBJ had in mind when he created the public Medicare program. (Medicare Advantage arrived—in nascent form—in 1997, after considerable pressure from the insurance industry.)
When we talk about the financial shortfall facing the Medicare program, we must look at Medicare Advantage as an aggravating factor. Reining-in MA would go a long way toward restoring the overall program to fiscal health—along with other commonsense reforms. Unfortunately, the Trump administration has been inconsistent on this issue, initially floating strict curbs on MA overpayments but ultimately rewarding insurance companies with higher payouts.
Traditional Medicare is far from perfect. It should have caps on patients’ out-of-pocket medical costs. It should cover vision, dental, and hearing care. (President Joe Biden attempted to expand coverage in the ill-fated Build Back Better Act.) These are improvements that we have long urged Congress and the White House to enact.
Medicare also faces compound financial challenges—including the overall rise in healthcare costs and soaring prescription drug prices. The Biden administration and Democrats in Congress took a major step in the right direction with the Inflation Reduction Act, which empowered Medicare to negotiate drug prices with Big Pharma. This process is expected to save the government more than $230 billion by 2031.
For the most part, the Trump administration has adhered to the law and continued negotiating with drugmakers—but it also expanded the list of cancer drugs that won’t be eligible for negotiations. The president has largely relied on smoke and mirrors to make it appear that the administration is "tough on Big Pharma," using gimmicks like TrumpRx. Meanwhile, in a move that will make medications less affordable for seniors, the Trump administration has just announced it is ending Biden-era subsidies in the Medicare Part D prescription drug program.
Of course, it’s also Medicaid’s 61st anniversary. The damage that Trump and the Republicans have done to Medicare’s sister program would take up another entire article. Suffice it to say that more than 3 million Americans have already lost health coverage since Trump and the GOP enacted their Big, Ugly Bill, which slashed nearly $1 trillion from Medicaid. (This also hurts older people dually enrolled in both Medicare and Medicaid.) It was correctly labeled the biggest cut in healthcare in US history—to pay for tax cuts largely benefiting the wealthy.
The political right has always been wary of the New Deal and Great Society legacy programs that lifted people out of poverty and provided older and lower-income Americans with basic retirement and health security. Some on the right have outright committed themselves to dismantling these programs, despite their distinguished histories. Trump and his allies in Congress have not so much dismantled these programs yet as chipped away at them under the guise of fighting "fraud and abuse." If this movement continues unabated, we may be left with the crumbling foundations of programs that were built to last, for the good of the American people.

While America’s current healthcare system is painfully vulnerable to Republican attacks, there is an opportunity to create a better future where all Americans can rely on guaranteed healthcare.
Sixty-one years ago, President Lyndon Johnson signed Medicare and Medicaid into law, while former President and long-time national health insurance champion Harry Truman watched. What Johnson and Truman understood was that the fight for guaranteed healthcare for everyone has been a generations-long struggle. The creation of Medicare and Medicaid was a key victory in that struggle. Importantly, though, Medicare and Medicaid are—to paraphrase what President Franklin Roosevelt said about the signing of Social Security into law—“a cornerstone in a structure which is being built but is by no means complete.”
After President Truman was unable to achieve his goal of guaranteed healthcare for all Americans, healthcare advocates decided to move incrementally. They began by pushing to cover seniors. Older Americans have the highest medical costs, the hardest time affording private health insurance, and need care the most often. The signing of Medicare achieved this important milestone, alongside the creation of Medicaid to cover healthcare for low-income Americans.
In 1972, Medicare was expanded to cover people with disabilities. But that is where progress stopped. It is well past time that we expand Medicare to cover children and everyone in between. We must also improve Medicare to cover such vital services as hearing, vision, dental and, perhaps most importantly, long-term care. And we must, in this age of abhorrent income and wealth inequality, require the wealthiest to contribute more while eliminating all premiums, co-payments, co-insurance, and deductibles.
Currently, we are at a crossroads. While America’s current healthcare system is painfully vulnerable to Republican attacks, there is an opportunity to create a better future where all Americans can rely on guaranteed healthcare.
With Republicans doing everything they can to disrupt and dismantle the current healthcare system, it is the perfect time to fight for a more durable and universal alternative.
Shamefully, Republicans are chipping away at both Medicare and Medicaid. The attacks take many forms. They include the effort to confuse Americans with the inferior, propagandistically named “Medicare Advantage;” the Trump administration giving AI the power to overrule doctors and block care for Medicare patients; the $1 trillion in cuts to Medicaid and the Affordable Care Act in the so-called Big Beautiful Bill (beautiful for billionaires, ugly for everyone else) passed by Republicans; and new Republican rules for Medicaid that would force cancer patients to get back to work and would cause millions of Americans to lose their healthcare coverage. Though Republican politicians would deny it, their hostility to Medicare and Medicaid is overwhelming.
Meanwhile, Democrats are working to expand and improve Medicare and Medicaid. They have taken concrete steps to lower prescription drug prices. The Inflation Reduction Act, which gives Medicare the power to negotiate for lower prices, was signed into law by a Democratic president, Joe Biden. Democrats are fighting to provide those same savings to those with commercial insurance and lower prices in other ways as well. Importantly, a growing number of Democrats are supporting and fighting for improved and expanded Medicare for All.
It may seem daunting and overwhelming to think about achieving improved and expanded Medicare for All in the current political environment, but it is within sight. Indeed, I have written a book-length road map to achieving improved and expanded Medicare for All, which will be released this September. It is called The Road to Medicare for All: A Call to Action (Routledge Press, forthcoming, 2026).
What would improved and expanded Medicare for All mean? It would mean this: no premiums, co-pays, co-insurance, or deductibles. It would mean comprehensive healthcare coverage for everyone in America, automatically. It would mean going to the doctor of your choice, without worrying whether your provider is in your insurer’s network. The vision of improved Medicare for All would include all services being covered automatically, including dental, vision, and hearing coverage. Medicare should also be expanded to cover long-term care, both at home and in nursing homes.
This November’s election will determine the future of Medicare and Medicaid. Will Republicans make Medicare and Medicaid work even worse for Americans? Will even more hospitals and nursing homes close? Or will Democrats be able to fight back and not only defend Medicare and Medicaid from Republican attacks, but enact a bold vision of improved and expanded Medicare for All?
With Republicans doing everything they can to disrupt and dismantle the current healthcare system, it is the perfect time to fight for a more durable and universal alternative: improved and expanded Medicare for All. Instead of a precarious and shaky patchwork system where a disruption to your healthcare is one job loss or plan change away, it is time to fight for a world where healthcare is truly a right, not a privilege.