SUBSCRIBE TO OUR FREE NEWSLETTER
Daily news & progressive opinion—funded by the people, not the corporations—delivered straight to your inbox.
5
#000000
#FFFFFF
To donate by check, phone, or other method, see our More Ways to Give page.
Daily news & progressive opinion—funded by the people, not the corporations—delivered straight to your inbox.
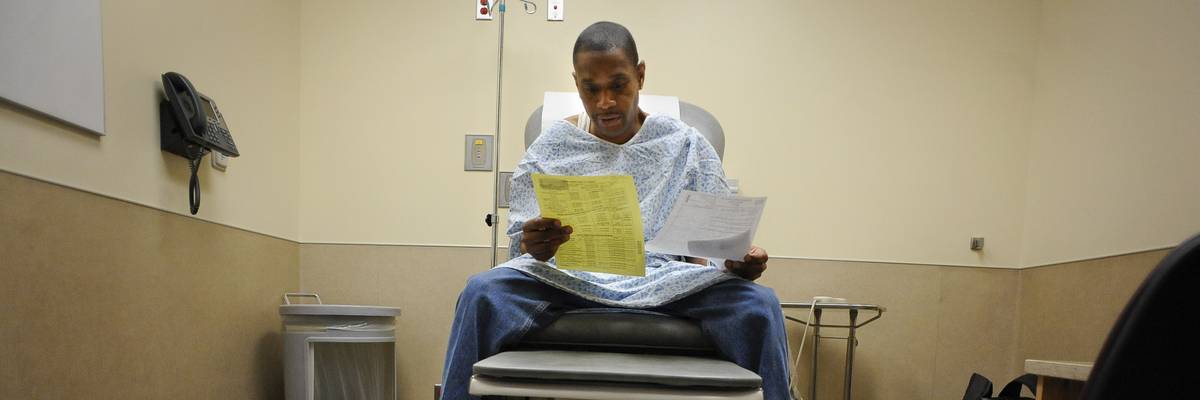
Medicaid patient Thomas Crippen looks over paperwork after being treated by family nurse practitioner Amy Quinone at Denver Health's Adult Urgent Care Clinic.
The Centers for Medicare and Medicaid Services' implementation of the One Big Beautiful Bill narrows the very protections Congress included to prevent vulnerable people nationwide from losing the health coverage they need.
The biggest Medicaid fight today isn't happening in Congress—it's happening inside the Centers for Medicare and Medicaid Services.
Now, a year after H.R. 1’s passage (the 2025 federal reconciliation bill enacting significant cuts and changes to Medicaid), CMS’ recently issued interim final rule (IFR) implementing the law’s work-reporting requirements in the program narrows the very protections Congress included to prevent vulnerable people nationwide from losing the health coverage they need.
The Congressional Budget Office previously estimated that more than 5 million people will lose Medicaid coverage because of these requirements. Already a conservative estimate as other organizations estimated over 10 million people are at risk of losing coverage, the number will surely be higher given CMS' IFR goes beyond the statutory language of the law.
The clearest example of this is the IFR's treatment of the medically frail exemption.
If the goal is really healthier communities and greater workforce participation, making it harder for medically vulnerable people to keep their health insurance is exactly the wrong approach.
Congress recognized that people living with complex medical conditions, disabilities, and chronic illnesses, including substance use disorder (SUD), should be protected from burdensome work-reporting requirements. As such, H.R. 1 specifically includes “medically frail” individuals among those exempt from the new requirements.
Yet CMS has added a new hurdle, putting millions of eligible Americans at dire risk of losing access to essential healthcare.
Under the IFR, people with SUD and other qualifying health conditions must also demonstrate that their condition "significantly impairs" their ability to satisfy the requirement before they can qualify for the exemption. This additional standard does not appear in the statute and will inevitably reduce the number of people who can secure the exemption.
For people living with SUD, the consequences could be profound.
While SUD is a chronic but treatable medical condition, pervasive stigma and discriminatory barriers have led to fewer than 1 in 5 people who need treatment actually receiving it. Amid persistent addiction and overdose crises, we should be making it easier for people to access the services and supports they need to become and stay well, not erecting additional barriers to lifesaving care.
Moreover, while CMS' rule relies heavily on Medicaid claims data and provider documentation to identify individuals who qualify as medically frail, the administration’s approach overlooks the reality that many people with SUD have never entered treatment due to the above-mentioned stigma and discrimination. Requiring additional documentation will not "motivate" people to seek care, as CMS suggests. Instead, it creates yet another barrier for people who are already among the hardest to reach.
When people are deprived of Medicaid access, their ability to engage in preventive care, behavioral health services, medications, and treatment that keep chronic conditions under control is also lost. And it doesn’t take a rocket scientist to understand how untreated health conditions can not just impede a person’s capacity to work but quickly lead to costly emergency services.
These are not only personal tragedies—they are costly public policy failures.
Taking away health coverage does not eliminate health needs. It just shifts and raises costs while undermining public health and safety. Access to healthcare is precisely what enables many people to work, care for their families, and be productive community members, so why are we erecting so many barriers?
If the goal is really healthier communities and greater workforce participation, making it harder for medically vulnerable people to keep their health insurance is exactly the wrong approach.
Last month, both our organizations, along with many other leading advocates nationwide, explicitly articulated these concerns and submitted comments urging the agency to reverse course and faithfully reinforce the protections Congress included in the law. While CMS' public comment period on the IFR is now closed, all those who share the same perspective can still take action by calling their members of Congress to share their concerns about the impact of H.R. 1 and specifically, how the administration is planning to implement the law.
A year after H.R. 1’s passage, the question is no longer simply about what Congress enacted—it is whether the regulations that make the law real will preserve purposeful protections or quietly erode them through administrative action.
Dear Common Dreams reader, It’s been nearly 30 years since I co-founded Common Dreams with my late wife, Lina Newhouser. We had the radical notion that journalism should serve the public good, not corporate profits. It was clear to us from the outset what it would take to build such a project. No paid advertisements. No corporate sponsors. No millionaire publisher telling us what to think or do. Many people said we wouldn't last a year, but we proved those doubters wrong. Together with a tremendous team of journalists and dedicated staff, we built an independent media outlet free from the constraints of profits and corporate control. Our mission has always been simple: To inform. To inspire. To ignite change for the common good. Building Common Dreams was not easy. Our survival was never guaranteed. When you take on the most powerful forces—Wall Street greed, fossil fuel industry destruction, Big Tech lobbyists, and uber-rich oligarchs who have spent billions upon billions rigging the economy and democracy in their favor—the only bulwark you have is supporters who believe in your work. But here’s the urgent message from me today. It's never been this bad out there. And it's never been this hard to keep us going. At the very moment Common Dreams is most needed, the threats we face are intensifying. We need your support now more than ever. We don't accept corporate advertising and never will. We don't have a paywall because we don't think people should be blocked from critical news based on their ability to pay. Everything we do is funded by the donations of readers like you. When everyone does the little they can afford, we are strong. But if that support retreats or dries up, so do we. Will you donate now to make sure Common Dreams not only survives but thrives? —Craig Brown, Co-founder |
The biggest Medicaid fight today isn't happening in Congress—it's happening inside the Centers for Medicare and Medicaid Services.
Now, a year after H.R. 1’s passage (the 2025 federal reconciliation bill enacting significant cuts and changes to Medicaid), CMS’ recently issued interim final rule (IFR) implementing the law’s work-reporting requirements in the program narrows the very protections Congress included to prevent vulnerable people nationwide from losing the health coverage they need.
The Congressional Budget Office previously estimated that more than 5 million people will lose Medicaid coverage because of these requirements. Already a conservative estimate as other organizations estimated over 10 million people are at risk of losing coverage, the number will surely be higher given CMS' IFR goes beyond the statutory language of the law.
The clearest example of this is the IFR's treatment of the medically frail exemption.
If the goal is really healthier communities and greater workforce participation, making it harder for medically vulnerable people to keep their health insurance is exactly the wrong approach.
Congress recognized that people living with complex medical conditions, disabilities, and chronic illnesses, including substance use disorder (SUD), should be protected from burdensome work-reporting requirements. As such, H.R. 1 specifically includes “medically frail” individuals among those exempt from the new requirements.
Yet CMS has added a new hurdle, putting millions of eligible Americans at dire risk of losing access to essential healthcare.
Under the IFR, people with SUD and other qualifying health conditions must also demonstrate that their condition "significantly impairs" their ability to satisfy the requirement before they can qualify for the exemption. This additional standard does not appear in the statute and will inevitably reduce the number of people who can secure the exemption.
For people living with SUD, the consequences could be profound.
While SUD is a chronic but treatable medical condition, pervasive stigma and discriminatory barriers have led to fewer than 1 in 5 people who need treatment actually receiving it. Amid persistent addiction and overdose crises, we should be making it easier for people to access the services and supports they need to become and stay well, not erecting additional barriers to lifesaving care.
Moreover, while CMS' rule relies heavily on Medicaid claims data and provider documentation to identify individuals who qualify as medically frail, the administration’s approach overlooks the reality that many people with SUD have never entered treatment due to the above-mentioned stigma and discrimination. Requiring additional documentation will not "motivate" people to seek care, as CMS suggests. Instead, it creates yet another barrier for people who are already among the hardest to reach.
When people are deprived of Medicaid access, their ability to engage in preventive care, behavioral health services, medications, and treatment that keep chronic conditions under control is also lost. And it doesn’t take a rocket scientist to understand how untreated health conditions can not just impede a person’s capacity to work but quickly lead to costly emergency services.
These are not only personal tragedies—they are costly public policy failures.
Taking away health coverage does not eliminate health needs. It just shifts and raises costs while undermining public health and safety. Access to healthcare is precisely what enables many people to work, care for their families, and be productive community members, so why are we erecting so many barriers?
If the goal is really healthier communities and greater workforce participation, making it harder for medically vulnerable people to keep their health insurance is exactly the wrong approach.
Last month, both our organizations, along with many other leading advocates nationwide, explicitly articulated these concerns and submitted comments urging the agency to reverse course and faithfully reinforce the protections Congress included in the law. While CMS' public comment period on the IFR is now closed, all those who share the same perspective can still take action by calling their members of Congress to share their concerns about the impact of H.R. 1 and specifically, how the administration is planning to implement the law.
A year after H.R. 1’s passage, the question is no longer simply about what Congress enacted—it is whether the regulations that make the law real will preserve purposeful protections or quietly erode them through administrative action.
The biggest Medicaid fight today isn't happening in Congress—it's happening inside the Centers for Medicare and Medicaid Services.
Now, a year after H.R. 1’s passage (the 2025 federal reconciliation bill enacting significant cuts and changes to Medicaid), CMS’ recently issued interim final rule (IFR) implementing the law’s work-reporting requirements in the program narrows the very protections Congress included to prevent vulnerable people nationwide from losing the health coverage they need.
The Congressional Budget Office previously estimated that more than 5 million people will lose Medicaid coverage because of these requirements. Already a conservative estimate as other organizations estimated over 10 million people are at risk of losing coverage, the number will surely be higher given CMS' IFR goes beyond the statutory language of the law.
The clearest example of this is the IFR's treatment of the medically frail exemption.
If the goal is really healthier communities and greater workforce participation, making it harder for medically vulnerable people to keep their health insurance is exactly the wrong approach.
Congress recognized that people living with complex medical conditions, disabilities, and chronic illnesses, including substance use disorder (SUD), should be protected from burdensome work-reporting requirements. As such, H.R. 1 specifically includes “medically frail” individuals among those exempt from the new requirements.
Yet CMS has added a new hurdle, putting millions of eligible Americans at dire risk of losing access to essential healthcare.
Under the IFR, people with SUD and other qualifying health conditions must also demonstrate that their condition "significantly impairs" their ability to satisfy the requirement before they can qualify for the exemption. This additional standard does not appear in the statute and will inevitably reduce the number of people who can secure the exemption.
For people living with SUD, the consequences could be profound.
While SUD is a chronic but treatable medical condition, pervasive stigma and discriminatory barriers have led to fewer than 1 in 5 people who need treatment actually receiving it. Amid persistent addiction and overdose crises, we should be making it easier for people to access the services and supports they need to become and stay well, not erecting additional barriers to lifesaving care.
Moreover, while CMS' rule relies heavily on Medicaid claims data and provider documentation to identify individuals who qualify as medically frail, the administration’s approach overlooks the reality that many people with SUD have never entered treatment due to the above-mentioned stigma and discrimination. Requiring additional documentation will not "motivate" people to seek care, as CMS suggests. Instead, it creates yet another barrier for people who are already among the hardest to reach.
When people are deprived of Medicaid access, their ability to engage in preventive care, behavioral health services, medications, and treatment that keep chronic conditions under control is also lost. And it doesn’t take a rocket scientist to understand how untreated health conditions can not just impede a person’s capacity to work but quickly lead to costly emergency services.
These are not only personal tragedies—they are costly public policy failures.
Taking away health coverage does not eliminate health needs. It just shifts and raises costs while undermining public health and safety. Access to healthcare is precisely what enables many people to work, care for their families, and be productive community members, so why are we erecting so many barriers?
If the goal is really healthier communities and greater workforce participation, making it harder for medically vulnerable people to keep their health insurance is exactly the wrong approach.
Last month, both our organizations, along with many other leading advocates nationwide, explicitly articulated these concerns and submitted comments urging the agency to reverse course and faithfully reinforce the protections Congress included in the law. While CMS' public comment period on the IFR is now closed, all those who share the same perspective can still take action by calling their members of Congress to share their concerns about the impact of H.R. 1 and specifically, how the administration is planning to implement the law.
A year after H.R. 1’s passage, the question is no longer simply about what Congress enacted—it is whether the regulations that make the law real will preserve purposeful protections or quietly erode them through administrative action.