

SUBSCRIBE TO OUR FREE NEWSLETTER
Daily news & progressive opinion—funded by the people, not the corporations—delivered straight to your inbox.
5
#000000
#FFFFFF
To donate by check, phone, or other method, see our More Ways to Give page.
Daily news & progressive opinion—funded by the people, not the corporations—delivered straight to your inbox.

"We cannot afford to sit by while our NHS is picked apart by a foreign regime," said one member of Parliament.
One member of British Parliament called on the Labour government to defend the country's revered National Health Service "with everything we have and firmly stand up to the bully in the White House" after a study published Wednesday showed the UK-US pharmaceutical trade deal brokered last year is projected to cause 229,000 excess deaths as funding is stripped away from the NHS.
“It is a complete insult to patients who are suffering and dying on hospital trolleys and waiting months for treatment," said Helen Morgan of the Liberal Democrats Party regarding the new analysis. "We cannot afford to sit by while our NHS is picked apart by a foreign regime."
The study, conducted by researchers at the University of York, the University of Liverpool, and Christchurch Hospital in New Zealand and published in the British Medical Journal, found that £44.7 billion ($59.5 billion) will have to be diverted from health services by 2036 in order to pay for new medications under the deal.
The agreement was reached last December, with recently resigned Prime Minister Keir Starmer's government agreeing to pay 25% more for new US medications over the next decade. The NHS will double the percentage of gross domestic product that it allocates for pharmaceuticals, from 0.3% to 0.6%, with the spending increasing from 10% to 12% of the universal healthcare system's budget.
In exchange, the Trump administration agreed not to impose tariffs of up to 100% that he had threatened for UK medicines being imported to the US.
Science Minister Patrick Vallance insisted in April that the deal would give NHS patients access to "life-changing new medicines that they previously would have been denied" while boosting the UK's "life sciences sector" by avoiding Trump's tariffs.
"Scandalously, this backroom deal was not subject to any scrutiny in Parliament before being rushed through—and the government refuses to say what impact it will have on the NHS."
But Sir Ciarán Devane, chief executive of the NHS Alliance, told The Guardian that the study raised "serious questions" about whether Britons will truly benefit from the agreement.
"If billions of pounds are diverted away from frontline care to meet higher medicines costs, the consequences for prevention, community services, and the treatment of long-term conditions could be profound," said Devane. "The government must urgently publish the full impact assessment and ensure there is appropriate scrutiny of the deal if it could have such far-reaching implications for population health.”
The projected avoidable death toll in the study far exceeds that which the UK saw during the coronavirus pandemic, when 137,000 excess deaths were recorded between March 2020-June 2022.
"If the indirect effect on adult social care is also included, the increase in excess deaths is even greater (291,000),” reads the study.
The greatest number of excess deaths is projected to occur in patients suffering from cardiovascular, respiratory, and gastrointestinal issues as well as cancer.
Patients with “neurological, endocrine, musculoskeletal, and mental health problems" will also face "broader effects on quality of life," the research states.
The government has assured the public that "frontline services" will be protected, notes the report, but "the NHS will need to fund this deal from allocations made six months before the deal was agreed. The evidence suggests that if additional public expenditure was available, it could be more effectively deployed within the NHS itself."
The research projected that the greatest number of deaths would occur in cardiovascular, respiratory, gastrointestinal and cancer patients.
It added that there will also be broader harm caused to quality of life for patients in those sectors as well as “neurological, endocrine, musculoskeletal, and mental health problems”.
Tim Bierley, a campaigner with the UK-based group Global Justice Now, said that the report "adds to the overwhelming evidence that the Trump medicines deal risks taking a wrecking ball to our health and our economy."
"Billions that could be spent on recruiting more NHS staff, cutting [general practitioner] waiting times, or improving our hospital care are set to be siphoned off by corporate giants in the pharma industry," said Bierley, whose group has joined the campaign Just Treatment in filing a legal challenge against the deal. "Scandalously, this backroom deal was not subject to any scrutiny in Parliament before being rushed through—and the government refuses to say what impact it will have on the NHS."
"The next prime minister," said Bierley, "must change direction, stand up for our NHS, and unpick the mess left by their predecessors.”

A health researcher for Public Citizen said Trump's interim CDC director has "no medical or public health background and extremist libertarian views."
After pushing out his own handpicked Centers for Disease Control and Prevention (CDC) director, infectious disease expert Susan Monarez, fueling a wave of outraged resignations this week, US President Donald Trump has appointed a loyal acolyte to replace her at Health and Human Services Secretary Robert F. Kennedy Jr.'s side.
On Thursday, the president tapped one of RFK's top aides as interim CDC director: biotech investor Jim O'Neill, a man with no medical experience but extensive experience profiting from healthcare while working at billionaire GOP megadonor Peter Thiel's venture capital firm, Mithril Capital.
Unlike his predecessor, whose ouster came as she tried to push back against RFK's anti-vaccine agenda, O'Neill fits snugly into the secretary's efforts to restrict access to the Covid-19 vaccine, and potentially ban it outright, as the Daily Beast reported earlier this week.
"A tech investor with no medical or public health background and extremist libertarian views, Jim O'Neill was unfit for the number two position at HHS and manifestly unqualified to lead the CDC," said Dr. Robert Steinbrook, director of Public Citizen's health research group, on Friday.
Just as Kennedy did during his confirmation hearings, O'Neill insisted he was "pro-vaccine," noting that he was "an adviser to a vaccine company." However, this is belied by his record on the subject.
He has championed unproven cures like ivermectin, hydroxychloroquine, and vitamin D supplements to protect against Covid-19, and has accused the CDC under the administration of former President Joe Biden of downplaying the vaccine's dangers while railing against mandates.
O'Neill has also praised Kennedy's response to the measles outbreak that swept across the US earlier this year, during which the secretary downplayed the severity and cast unfounded doubt on the effectiveness and safety of the measles vaccine that had virtually eradicated the disease before vaccination rates began to decline.
"Unlike Susan Monarez," Steinbrook said, "O'Neill is likely to rubber-stamp dangerous vaccine recommendations from HHS Secretary Kennedy's handpicked appointees to the Advisory Committee on Immunization Practices and obey orders to fire CDC public health experts with scientific integrity."
O'Neill melds medical crankery with a Thielite strain of anarcho-libertarianism. He has served on the board of the Seasteading Institute, an organization founded by Patri Friedman, the grandson of the right-wing economist Milton Friedman, who advocates for corporations like Apple and Google to form their own floating cities at sea, which would be governed as corporate "dictatorships" free from the constraints of democratic governance.
That anti-government ethos extends to his views on the healthcare system, which O'Neill says is flawed not because of the rampant profiteering of the private companies that run it, but because it is supposedly not "free market" enough.
In 2014, he advocated for the Food and Drug Administration (FDA) to begin approving drugs for the market without conducting clinical trials to determine their effectiveness. "Let people start using them, at their own risk," he argued, "Let's prove efficacy after they've been legalized."
He has also argued for the government to allow people to sell their own internal organs. This process often results in deteriorating health for the disproportionately poor people who partake.
While working at HHS under the administration of former President George W. Bush, O'Neill also opposed the FDA regulation of companies that use algorithms to perform laboratory tests.
At the time, he was focused on DNA testing products like 23andMe, but a report from the consumer watchdog group Public Citizen says that "a decade after he made this remark, it's clear how dangerous such a concept is," noting that "with the development and proliferation of artificial intelligence, algorithms are omnipresent in the practice of medicine, including in diagnostic tools, medical devices, AI assistants to doctors, and personalized medicine."
In addition to Thiel's ideology, he reportedly brings several conflicts of interest to the CDC director job from his time working at Thiel's venture capital firm.
Accountable.US reported Friday that O'Neill "took money from, helped incubate, or was otherwise linked to at least eight medical industry startups with direct business before the department he could help run."
These include firms he advised, like the pharmaceutical company ADvantage Therapeutics or the National Institutes of Health grantee Rational Vaccines, which manufactures herpes drugs.
It also includes four companies seeded by his Thiel-affiliated venture capital firm Breakout Labs, some of which have received government funding or have products awaiting FDA approval.
Though O'Neill agreed to divest from some of these companies and abstain from involvement in decision-making with them as part of his ethics agreement, the report notes that "he did not promise to abstain from decisions involving these companies for the duration of his term, or to abstain from doing business with them after departing HHS."
"O'Neill would be in a prime position to ensure favorable outcomes for several medical industry startups he's been financially linked to that have direct business before HHS and the CDC," said Accountable.US executive director Tony Carrk. "How can American patients be sure that proper vetting of these companies would take place on O'Neill's watch and that public health will be a higher priority over the profits of his former clients?"
Though Steinbrook describes O'Neill as "manifestly unqualified" for the position, he said, "No credible public health authority is likely to work for Kennedy, who is dictating the agency's decisions based on whim, not science."
"The only path forward," Steinbrook said, "is for Kennedy to go, which Congress, professional organizations, medical journals, and the public should demand."

One critic said the party's "top priority is making working- and middle-class families pay more for healthcare, lifesaving medications, food, cars, and electronics, all to fund more tax breaks for the ultrawealthy."
The national campaign Unrig Our Economy said Wednesday that U.S. President Donald Trump's promise of tariffs targeting the automobile industry, pharmaceuticals, and semiconductor chips is just the latest evidence that elected Republicans are prioritizing megarich individuals and corporations, not working people.
"This action is further proof that Republicans' top priority is making working- and middle-class families pay more for healthcare, lifesaving medications, food, cars, and electronics, all to fund more tax breaks for the ultrawealthy," said Unrig Our Economy spokesperson Kobie Christian in a statement.
The statement followed Trump discussing the forthcoming tariffs with reporters on Tuesday at his Florida residence, Mar-a-Lago. Bloomberg's Hadriana Lowenkron asked about his plans for new taxes on imports.
For the auto industry, "I probably will tell you that on April 2, but it'll be in the neighborhood of 25%," Trump said. For pharmaceuticals and semiconductors, he added, "it'll be 25% and higher, and it'll go very substantially higher over course of a year," giving those industries some time to set up U.S. factories to avoid the tariffs.
On April 1, "members of his Cabinet are due to deliver reports to him outlining options for a range of import duties as he seeks to reshape global trade," Reuters reported.
Trump's 10% tariff for imports from China has taken effect, but his 25% tariffs targeting Canada and Mexico have been delayed.
David Greene, an industry analyst at Cars.com, told CNN that "if the administration moves forward with a 25% tariff on all auto imports, car shoppers should get ready for some sticker shock at dealerships."
"If new car prices increase, more buyers will shift toward used vehicles, and as demand rises, so will prices," Greene said.
The president's latest comments on tariffs came after Republicans in the U.S. House of Representatives last week advanced out of committee a budget plan that would cut healthcare and food assistance programs to fund tax giveaways for the rich.
The Economic Policy Institute last week released a report detailing how extending the expiring provisions from the tax law that Republican lawmakers passed and Trump signed in 2017 "will have painful trade-offs for the U.S. economy and most Americans."
Christian said Wednesday that "even as the cost of everyday goods continues to rise and Trump and the billionaires in his administration arbitrarily cut programs that help feed children and seniors, Republicans in Congress are still pushing forward an agenda that would give billions in handouts to the wealthiest few, while leaving the rest of us behind."
"Our representatives in Congress need to look out for their constituents," the spokesperson added, "instead of prioritizing cost-raising tariffs to bankroll a massive payday for billionaires and giant corporations."

"Unfortunately, instead of working with Congress on this real issue, Trump and Musk have launched an immoral and unconstitutional attack on the Department of Health and Human Services."
Responding to a new study showing that leading health services companies made $2.7 trillion in profits and spent $2.6 trillion on stock buybacks and dividends in the years 2001-22, U.S. Sen. Bernie Sanders on Wednesday vowed to continue "to take on the unprecedented level of corporate greed in our healthcare system."
The study, published this week by the Journal of the American Medical Association, noted the "growing concern that a large proportion of U.S. healthcare spending appears to be directed to corporate shareholders rather than enhancing affordable access, improving quality of care, or advancing research and development."
Sanders (I-Vt.)—the ranking member of the Senate Committee on Health, Education, Labor, and Pensions—said in a statement that "it is absolutely unacceptable that since 2001, the top healthcare companies in America spent 95% of their profits, $2.6 trillion, not to make Americans healthy, but to make their CEOs and stockholders obscenely rich."
The top health care companies in America spent 95% of their profits to make their CEOs & stockholders obscenely rich. How many Americans would be alive today if those companies spent $2.6 trillion on disease prevention and primary care, instead of stock buybacks and dividends?
[image or embed]
— Senator Bernie Sanders (@sanders.senate.gov) February 12, 2025 at 11:21 AM
"The function of a rational healthcare system is to guarantee quality healthcare to all, not huge payouts for stockholders and executives in the drug and insurance industries," Sanders asserted. "None of this money was used to search for new treatments and cures, to lower prices, or to improve patient care. That has got to change."
The senator continued:
This study confirms that the greatest waste, fraud, and abuse in this country is corporate greed. Unfortunately, instead of working with Congress on this real issue, [U.S. President Donald] Trump and [Department of Government Efficiency leader Elon] Musk have launched an immoral and unconstitutional attack on the Department of Health and Human Services.
Instead of taking on the greed of the pharmaceutical industry, Trump and Musk are taking away AIDS treatment from poor people.
Instead of taking on the for-profit insurance industry, Trump and Musk are making it harder for working-class Americans to get the healthcare they need through Medicaid and community health centers.
"This absurdity must end," Sanders stressed. "As the ranking member of the Senate Health, Education, Labor, and Pensions Committee, I will do everything I can to take on the unprecedented level of corporate greed in our healthcare system."
Last month, Sanders—who twice sought the Democratic presidential nomination on a platform centering Medicare for All—unveiled a nine-point "Make America Healthy Again" plan in response to Health and Human Services secretary nominee Robert F. Kennedy Jr.'s variation on Trump's "Make America Great Again" slogan.

"As CMS negotiates the prices Medicare will pay for top-selling drugs, it should take into account the billions we've already lost due to these patenting tactics," said one researcher.
When the Inflation Reduction Act became law in 2022, it included a historic provision that gave the Centers for Medicare and Medicaid Services (CMS) the ability to negotiate maximum fair prices for select drugs. This means that CMS now has an important tool to resist high prices imposed by pharmaceutical companies and lower the cost that Medicare recipients pay for their drugs. So far, Medicare has negotiated the maximum fair prices for 10 drugs, which will go into effect January 1, 2026.
But according to a report released Wednesday by the watchdog group Public Citizen, the manufacturers behind these drugs are able to rely on another method to protect their profits: patent abuses and evergreening tactics.
The report defines "evergreening tactics" as the practice of "patenting trivial and/or obvious modifications of existing medications to lengthen exclusivity on branded medicines."
The makers of the drugs Eliquis, Imbruvica, Jardiance, Farxiga, and Entresto, for example, obtained patents on what constitute trivial or minor changes to earlier patent claims, "such as crystalline forms of drug compounds which would be discovered and managed during routine testing that is part of the drug approval process," according to Public Citizen. These new patents allow the manufacturers to extend their monopoly on these drugs.
" Big Pharma patent abuse is cheating Medicare enrollees of more affordable drugs and costing taxpayers billions," said Public Citizen Access to Medicines program researcher Jishian Ravinthiran in a statement.
"Patent abuses enable Big Pharma companies to unfairly extend their monopolies and keep prices artificially high. As CMS negotiates the prices Medicare will pay for top-selling drugs, it should take into account the billions we've already lost due to these patenting tactics," he added.
The report makes this same point, arguing that the agency's initial offers on pharmaceuticals should take into account how long-monopoly drugs have been able to obtain longtime exclusivities on medicines by manipulating patents.
This is paramount, Public Citizen argues, given the scope of lost savings. The group estimates that Medicare will lose somewhere between $4.9 and $5.4 billion in savings that should have accrued to taxpayers if four out of the 10 drugs did not take advantage of patenting tactics, and therefore would have faced greater competition prior to negotiation.
"These lost savings are nearly as much as what Medicare is expected to save if negotiated prices go into effect on all of the selected drugs in the first year of the program ($6 billion)," according to the report.
As an example, the drug etanercept, which is marketed as Enbrel, is on the list of 10 drugs that will be subject to a negotiated cap come January 2026. Etanercept's maker Amgen did not contribute to the original research and development of etanercept, per Public Citizen, it just acquired the original maker of the drug, Immunex, in 2002.
Immunex's patent of etanercept was set to expire in 2019, but "by using abusive patent practices" Amgen was able to extend the patent protections through 2029, according to Public Citizen. Amgen was able to evade competition of two potential "biosimilar" competitors, Erelzi and Eticovo, which received FDA approval in the 2010s.
Referencing analysis done in a separate report, Public Citizen estimated "that biosimilars could have entered the market after August 2019 were it not for Amgen's unwarranted patent exclusivities, and we calculated Medicare would have spent $1,891,500,836 less on a net basis had enrollees been able to use lower-cost alternatives by the time negotiated prices go into effect on January 1, 2026."

"By nominating RFK Jr. and Mehmet Oz," said one public health expert, "Trump is giving his middle finger to science."
If confirmed to be the next U.S. secretary of health and human services, anti-vaccine activist Robert F. Kennedy Jr. could be working "closely" with another official who's infamous for his questionable health guidance: Dr. Mehmet Oz, who President-elect Donald Trump on Tuesday nominated to run the Centers for Medicare and Medicaid Services.
Trump said in a statement that if confirmed, Oz would "cut waste and fraud within our Country's most expensive Government Agency"—a plan that advocates for Medicare said would be carried out by privatizing the healthcare program that serves more than 66 million senior citizens.
As The Lever reported in 2022, Oz aggressively pushed Medicare Advantage plans on his show, The Dr. Oz Show, airing one segment about the insurance agency MedicareAdvantage.com and urging viewers to sign up for the program via a hotline. Insurance companies that offer Medicare Advantage plans are notorious for requiring "prior authorization" for doctors to provide certain medical procedures, subjecting patients to deceptive marketing, and harming senior citizens.
Considering his opposition to traditional Medicare, Matt Stoller of the American Economic Liberties Project said Oz "is not a good pick for a very powerful position in charge of a trillion dollars of healthcare spending."
The advocacy group Social Security Works noted that plans to "completely privatize Medicare" are also in Project 2025, the far-right policy agenda that Trump repeatedly tried to distance himself from while campaigning.
"Hands off our earned benefits!" said the group.
With Trump's support, Oz unsuccessfully ran to represent Pennsylvania in the U.S. Senate in 2022. The president-elect said Tuesday that if confirmed, Oz would work closely with Kennedy "to take on the illness industrial complex."
Kennedy's proposals for doing so include halting research on drug development, removing teeth-strengthening fluoride from drinking water, and firing Food and Drug Administration employees who have waged a "war on public health" through the "suppression" of the veterinary drug ivermectin and raw milk, which has been associated with disease outbreaks.
Oz has spent years peddling health advice, half of which University of Alberta researchers found to be "baseless or wrong" in a 2014 study published in the British Medical Journal. He promoted a study claiming coffee bean weight loss pills would "burn fat fast for anyone," but the research was later retracted. Oz also claimed that eating certain foods like red onion and endive could reduce a person's cancer risk by up to 75%, leading one paper published in the journal Nutrition and Cancer to assert, "Reality Check: There is no such thing as a miracle food."
Oz has also maintained close ties to multi-level marketing companies that promote products like vitamins with false claims about their ability to treat, cure, or prevent diseases.
"Dr. Oz is unfit to run CMS," said Lawrence Gostin, director of the O'Neill Institute at Georgetown University. "He peddles conspiracy theories on vaccines and fake cures. He profits from fringe medical ideas."
"By nominating RFK Jr. and Mehmet Oz," he added, "Trump is giving his middle finger to science. Having worked for 40 years in public health, it's utterly disheartening."
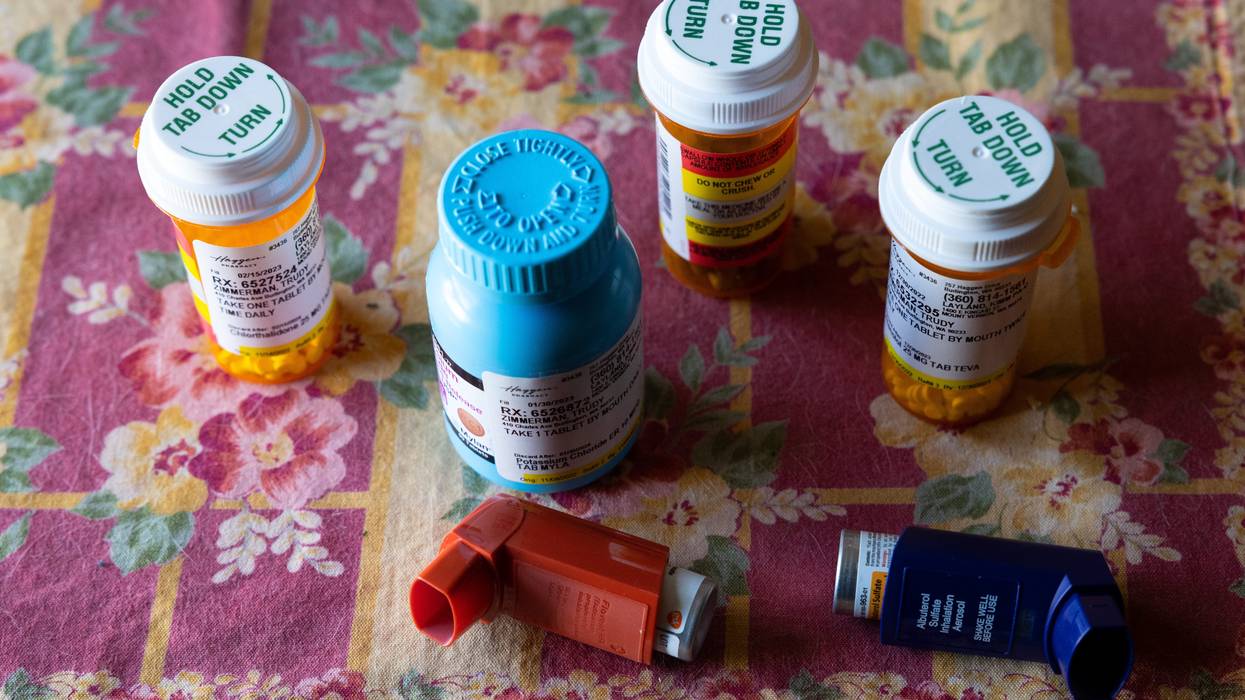
"We launched an investigation into big drug companies because the prices they were charging for inhalers just didn't add up," said Sen. Tammy Baldwin. "And looks like we were right."
Starting in June, the German pharmaceutical giant Boehringer Ingelheim will cap co-pays for its inhalers at $35 for U.S. patients—a decision that came just two months after members of a Senate panel led by Sen. Bernie Sanders launched an investigation into inhaler price gouging.
Combivent Respimat, one of Boehringer Ingelheim's inhaler products, carries a list price of around $500 in the U.S. That's roughly 70 times what the company charges for the same product in France, where patients can get the inhaler for $7.
Boehringer Ingelheim said Thursday that it plans to reduce the list prices of some of its inhalers.
Sanders (I-Vt.), chair of the Senate Health, Education, Labor, and Pensions (HELP) Committee, called the company's moves "very positive steps in the right direction" and demanded that other major inhaler manufacturers "take similar action."
"A Vermont resident recently told my office that she has to pay $320 per month for Boehringer Ingelheim's Spiriva HandiHaler. As a result of today's decision, she could save more than $3,000 a year on the inhaler that she needs to breathe," Sanders said in a statement Thursday. "If Boehringer Ingelheim can take action to cap the cost of inhalers at $35 in the United States and lower the list price of some of the inhalers it manufactures, these other companies can do the same."
In January, Sanders and other Senate HELP Committee members announced a probe into "the extremely high prices" that Boehringer Ingelheim, AstraZeneca, and other companies charge for their inhalers.
"We launched an investigation into big drug companies because the prices they were charging for inhalers just didn't add up," Sen. Tammy Baldwin (D-Wis.), a member of the HELP panel, wrote on social media Thursday. "And looks like we were right."
We launched an investigation into big drug companies because the prices they were charging for inhalers just didn’t add up.
And looks like we were right.
I’m glad to see some of the price gouging end and proud to help lower costs for Wisconsin families. pic.twitter.com/QluMNCSwJA
— Sen. Tammy Baldwin (@SenatorBaldwin) March 7, 2024
Boehringer Ingelheim was also facing scrutiny from the Federal Trade Commission (FTC). In November, the agency said it believes some of the company's patents "may have been improperly listed in the Orange Book," which includes products the agency deems safe and effective.
"Patents improperly listed in the Orange Book may delay lower-cost generic drug competition," the FTC wrote in a letter to Boehringer Ingelheim. "By listing their patents in the Orange Book, brand drug companies may benefit from an automatic, 30-month stay of FDA approval of competing generic drug applications."
On Wednesday, as Reuters reported, a class-action lawsuit filed in federal court by the Massachusetts Laborers' Health and Welfare Fund accused Boehringer Ingelheim of "improperly submitting patents to the U.S. Food and Drug Administration to delay generic competition and inflate prices for its lung disease drugs Combivent Respimat and Spiriva Respimat."
"As a result of Boehringer's wrongful Orange-Book-listing scheme, there [are], to this day, no affordable generic versions of either Combivent Respimat or Spiriva Respimat," the lawsuit states. "Payors must continue to pay for expensive brand-name products, instead of affordable generic products that should have been available years ago. This has caused payors, including the plaintiff, to suffer many millions, if not billions, of dollars in overcharges over the past three years."

"The court has rejected AstraZeneca's self-serving arguments and essentially said the company didn't have a leg to stand on," said one advocate.
The president of consumer advocacy group Public Citizen on Friday urged Big Pharma to "drop its far-fetched lawsuits and accept that the era of Medicare price negotiation is here to stay," after a federal judge in Delaware rejected drug company AstraZeneca's case challenging provisions under the Inflation Reduction Act.
AstraZeneca Pharmaceuticals LP et al. v. Becerra et al. is one of several cases that drug companies have filed against the federal government seeking to block Medicare from negotiating drug prices on behalf of patients—as the governments of every other high-income country do, with Americans paying as much as four times what people in countries such as the United Kingdom and Canada pay for their medications.
The company claimed that the Centers for Medicare & Medicaid Services violated the Administrative Procedure Act.
Chief Judge Colm Connolly in the U.S. District Court for the District of Delaware ruled that "because AstraZeneca's participation in Medicare is not involuntary, AstraZeneca does not have a protected property interest in selling drugs to the government at prices the government will not agree to pay. Accordingly, AstraZeneca's due process claim fails as a matter of law."
"Drug corporations have no constitutional right to price gouge Medicare, contrary to Big Pharma's claims."
In other words, said Patients for Affordable Drugs (P4AD), the judge emphasized that "the company's desire for higher prices does not supersede the government's ability to protect patient interests."
"On behalf of patients across this country, we are encouraged but not surprised that the court has rejected AstraZeneca's self-serving arguments and essentially said the company didn't have a leg to stand on," said Merith Basey, the group's executive director. "This ruling sends a clear message that Big Pharma's greed cannot continue to be prioritized over patients' well-being and underscores the importance of Medicare negotiation to begin to rein in exorbitant drug prices."
"The judge's decision reaffirms that pharmaceutical companies like AstraZeneca have the option to participate in Medicare voluntarily, accepting slightly lower negotiated prices if they wish to access a market worth billions," added Basey. "Once again, a judge has reviewed drug company claims, and the result has gone against the drug company and for the people of the United States."
AstraZeneca's drug Farxiga, which is used to treat Type 2 diabetes, was one of 10 medications selected by the Biden administration last year for the first round of negotiations under the Inflation Reduction Act's (IRA) Medicare Drug Price Negotiation Program. In 2022, the company reported nearly $4.4 billion in revenue from Farxiga.
P4AD said Connolly's ruling was a victory for patients like Karen, a Pueblo West, Colorado resident.
"I am on Medicare and was prescribed Farxiga with a bill of over $600 for a three-month supply. I am on a fixed income and can no way afford that amount of money," Karen told the group, which has signed onto amicus briefs in seven different cases regarding Medicare price negotiations.
Tony Carrk, executive director of Accountable.US, noted that Big Pharma previously spent millions lobbying against the drug price negotiation provisions in the IRA.
“Big drug company executives are stopping at nothing to price gouge Americans and pad their profits," said Carrk. "Now they are trying to do it by clogging the judicial system with meritless lawsuits. Today's ruling is a victory for the Biden administration's historic cost-lowering program and for seniors who need lower prescription drug costs."
Robert Weissman, president of Public Citizen, pointed out that the IRA's restraints on Big Pharma's price gouging are only "modest" but will make a difference to seniors, saving $100 billion over a decade.
"In response, Big Pharma has launched a flurry of preposterous lawsuits against the Medicare drug negotiation provisions in the Inflation Reduction Act," said Weissman. "As Public Citizen has argued in amicus briefs, drug corporations have no constitutional right to price gouge Medicare, contrary to Big Pharma's claims."
Weissman said his expects that with seven pending cases, "today's decision is the first of many rejecting Big Pharma's attack on the act's effort to rein in exorbitant prescription drug prices."

"I don't want their money," one woman who lost a son to the opioid crisis said of the Sackler family. "I want them in prison."
At the U.S. Supreme Court on Monday, families whose loved ones are among the tens of thousands of Americans who have died of opioid use disorder each year over the past two decades rallied to push the nine justices to reject a proposed bankruptcy plan that would give the former owners of Purdue Pharma legal immunity—with many joining the U.S. Justice Department in arguing that the company should not be released from accountability for the opioid epidemic.
Purdue Pharma filed for bankruptcy in 2019, as the number of Americans killed by opioids hit 50,000 and the OxyContin manufacturer faced thousands of lawsuits alleging its aggressive marketing of the addictive painkiller had fueled the rising death toll.
The company agreed to settle the lawsuits for $10 billion, with the Sackler family—which oversaw Purdue when OxyContin was introduced and flooded communities across the U.S.—contributing $4 billion. In exchange, the Sacklers would be shielded from future lawsuits.
The bankruptcy plan—which now includes $6 billion from the Sacklers following a push from lawsuit plaintiffs—has been approved by state and local governments, tribes, and families and individuals who would be entitled to money.
But the U.S. Trustee Program, a watchdog at the Justice Department, has joined some families in arguing that the Sacklers should not be shielded from liability for the opioid crisis.
"No Sackler immunity at any $$," read one sign held by a woman outside the Supreme Court on Monday, while another said, "My dead son does not release Sacklers."
The issue at hand in the case, Harrington v. Purdue Pharma, is whether it is legal to give a third party—the Sackler family—legal immunity in a bankruptcy case even though they themselves have not declared bankruptcy, also known as nonconsensual third-party release.
A lawyer for groups and individuals told the court that families and governments are highly unlikely to get any more out of Purdue and the Sacklers than the money the company and family have offered as part of the deal.
The plan would include $161 million in a trust set aside for Native American tribes and $700 million to $750 million in a trust for families and individuals who were able to file claims, with payouts expected to range from about $3,500 to $48,000. Governments would use the money to set up addiction treatment centers and other programs to mitigate the opioid crisis.
"Forget a better deal—there is no other deal," lawyer Pratik Shah told the Supreme Court on Monday.
Curtis Gannon, representing the U.S. Trustee Program, noted that the Sackler family already showed that a "better deal" could be possible when it offered $6 billion for the plan instead of $4 billion. The Justice Department is advocating for a new settlement that would not include nonconsensual third-party releases, saying the current bankruptcy deal violates federal law.
"We do hope there is another deal at the end of this," said Gannon.
The justices appeared split on the case, in which a ruling is expected next summer. Justice Ketanji Brown Jackson noted that appeals courts do not allow bankruptcy plans that take away the rights of alleged victims to sue parties that have not declared bankruptcy.
Outside the court, Alexis Pleus, who lost her son to opioid use disorder, told Aneri Pattani of KFF Health News that many families, including hers, will not be entitled to money under the current deal because they are required to provide records such as the original opioid prescription.
Beth Macy, author of the book Dopesick, told CNN Monday morning that while some families "are divided" about whether the bankruptcy plan and payouts should move forward, as the U.S. Trustee Program "has pointed out, only 20% of the families who were eligible to vote on [the proposal], even voted."
"I don't want their money," Jen Trejo, whose son Christopher was prescribed OxyContin at age 15 and died of an overdose when he was 32, told Pattani. "I want them in prison."

They are walking out across the country for better working conditions and a commitment to increasing staffing levels needed to perform their job safely and effectively for the patients they serve.
Employees are staging walkouts at some of the biggest pharmacy retail chains in the country. A string of pharmacies closed at CVS in Kansas City. Later pharmacists held walkouts at Walgreens. More recently, an estimated 4,500 pharmacy workers from all three of the biggest chains, CVS, Walgreens and Rite Aid, announced participation.
#Pharmageddon is trending in nationwide protest. Pharmacy Guild, a new worker empowerment project, announced its efforts to unionize. With the recent news of the SAG-AFTRA strike ending, and the United Auto Workers declaring victory in new contracts, there is hope agreements can be made for resolution.
I worked as a community pharmacist early in my career more than 20 years ago. I dreaded times when I was alone in the pharmacy—every shift—haphazardly filling prescriptions while getting tied up on the phone adjudicating insurance claims, all the while running from one end of the pharmacy to another inputting, verifying, and dispensing prescriptions rapidly.
Every voice is needed to see positive legislation and improved conditions for pharmacies and to also encourage reform.
I was also answering doctor calls, attending to the drive-through, and hurriedly ringing up and counseling patients as fast as I could, without any help for half of my workday. Admittedly, I did not have the added stress of administering vaccinations while performing those duties at that time.
Pharmacy walkout momentum has been on the rise since 2021. Chronic understaffing coupled with higher prescription volume and growing additional duties exacerbated by the Covid-19 pandemic, with vaccinations and rapid test appointments, have led to unsafe working conditions for both employees and patients.
Additionally, abusive business practices by pharmacy benefit managers have not only resulted in thousands of pharmacy closures nationwide, but inflation in the amount paid for prescription drugs by seniors due to a loophole in Medicare regulations. According to Centers for Medicaid & Medicare Services, retroactive direct and indirect remuneration fees have increased by 107,400% between 2010-2020.
To be sure, drugstore chains have been struggling over the years with rising competition from mail-order pharmacies and lower reimbursement rates for prescription drugs, leading to the elimination of multiple locations and bankruptcy filings.
However, the pharmacy closures are now leaving gaps in communities for medicines and essentials. An assessment of pharmacy closures revealed one in eight pharmacies closed from 2009-2015, with pharmacies located in low-income, urban areas at greater risk of closing. The closures can create pharmacy deserts, further worsening the problem of disparities and access.
Pharmacists are highly skilled and trained, obtaining six to eight years of formal education with an additional one to two more years for possible post-graduate training. They enter the workforce eager to use their expert drug knowledge and provide patient-centered care.
For many, the excitement quickly dissipates in a highly volatile, pressurized environment. Inadequate staffing and burnout are truly a prescription for disaster.
The American Pharmacists Association supports workplace safety and well-being. The American Association of Colleges of Pharmacy is also in solidarity to improve working conditions.
Unlike other union strikes by autoworkers and SAG-AFTRA members, pharmacists participating in the walkouts are not asking to increase their salary. They are asking for better working conditions and a commitment to increasing staffing levels needed to perform their job safely and effectively for the patients they serve.
They are asking to not have to put patients’ lives at risk every day. They are asking not to have to place their mental health and well-being at risk every day. They are asking for improved work-life balance and sustainable working conditions to keep patients safe.
They are asking retail employers to do the right thing and set realistic goals for performance with adequate resources and staffing in place. They are asking pharmacy benefit managers to do the right thing and stop the assessment of exorbitant direct and indirect remuneration fees on retail prescriptions that are pushing pharmacies out of business.
It is not too much to ask.
As of January 1, 2024, the Centers for Medicaid & Medicare Services issued a final rule eliminating Part D plans’ and pharmacy benefit managers’ use of retroactive direct and indirect remuneration fees.
However, the first half of 2024 will still come with cash flow challenges for pharmacies, high fees, and low point-of-sale reimbursement during the transition, in addition to retroactive fees from 2023. More actions are needed to stop pharmacy benefit managers’ harmful business practices.
Every voice is needed to see positive legislation and improved conditions for pharmacies and to also encourage reform. From policy makers to elected officials, advocates, healthcare professionals, funders, pharmacists, retailers, customers, and citizens, everyone needs to acknowledge this urgency and make changes.
Community pharmacists need help now.