

5
#000000
#FFFFFF
To donate by check, phone, or other method, see our More Ways to Give page.
Daily news & progressive opinion—funded by the people, not the corporations—delivered straight to your inbox.

Because Improved Medicare for All is such a winning policy, powerful forces opposed to it must rely on fear, division, and lies to prevail. Knowing their lines of attack will help assure our ultimate victory.
To move forward toward Improved Medicare for All, the supporters must be strategic, persistent, and patient. In addition, supporters must be ready to neutralize the counterattacks from the opponents who are rich, formidable, and devious.
Because Improved Medicare for All is such a winning policy, those powerful forces must rely on fear, division, and lies to prevail. They succeed not by convincing us with reason but rather by tricking us into working against our own best interests. President Roosevelt exposed this dynamic in 1936, as he fought for our Social Security. “It is an old strategy of tyrants to delude their victims into fighting their battles for them,” he warned us.
As a first step, it is imperative to recognize who the “tyrants” are. They include some of the largest, most profitable, multinational corporations in the world, the ones that profit so enormously from the current healthcare system. The “tyrants” also include billionaires who are determined to amass more and pay as little as possible toward the common good. These wealthiest people in the history of the world have no intention of paying their fair share.
In addition to them are their surrogates, some of whom may be disguised. They include those we elect, who are supposed to work for us, but want to keep open and flowing the pipeline to campaign contributions and other benefits the wealthy “tyrants” provide. Some of the surrogate-politicians are obvious. They seek unabashedly and openly to rip away even the inadequate health insurance Americans currently have. They are the ones working toward the further privatization of Medicare.
Some, though, whether they rationalize to themselves or simply are confused and don’t realize that they are doing the bidding of the “tyrants,” claim that they support national health insurance, but argue that it’s not practical. They not only don’t fight for Improved Medicare for All, they muddy the debate and even may subtly throw up roadblocks to its enactment. Another group of surrogates are some journalists and editors who often work for publications owned by the billionaire “tyrants.”
All of these surrogates are highly influential and may convince your family, friends, neighbors, and even you, that Improved Medicare for All is something to be feared – notwithstanding that virtually every other industrialized country has their own form of Improved Medicare for All, systems that cover their entire populations less expensively and have better health outcomes than the United States.
To understand how the “tyrants” and their surrogates delude their victims – the rest of us – into fighting among ourselves and working against our own best interests, it is essential to keep in mind the Powell memo of the 1970s and the Gingrich memo of the 1990s. Underlying both was the retreat from honest policy discussions and instead a power struggle backed by huge amounts of money. Their views represent a small minority, so their method of prevailing is to divide and instill fear.
Supporters must be hyper-vigilant against the monied interests tricking the American people into succumbing to this “old strategy of tyrants.” Those who want to enact Improved Medicare for All must understand the facts and the ploys.
Perhaps the oldest line of attack is simply to call Improved Medicare for All “socialized medicine.” The phrase “socialized medicine” has become the proverbial four-letter curse word to many Americans. Opponents are quick to label any health proposals they don’t like, “socialized medicine.”
One might think that the phrase, “socialized medicine,” has lost its bite. After all, the Soviet Union and the Cold War officially ended decades ago, on December 25, 1991, when the hammer-and-sickle flag last flew over the Kremlin in Moscow. The phrase appears to be effective because it invokes irrational fears of change and the unknown. It is, in essence, shorthand for something that is foreign, dangerous, and scary.
Because the charge plays on people’s fears, the lie that Improved Medicare for All is socialized medicine can’t be defeated with logical explanations. Rather, it makes sense to address quickly the epithet but then immediately pivot to what people like about Improved Medicare for All.
Another powerful lie is that Improved Medicare for All will hurt the people who are currently on Medicare. This is a deeply cynical stratagem, but, unfortunately, it is effective. Because seniors and people with disabilities, on average, have the greatest health care needs, they are, as a group, particularly susceptible to this kind of fearmongering. It is therefore imperative that advocates of Improved Medicare for All have a honed, well thought-through strategy aimed toward current Medicare beneficiaries and those close to turning age 65.
In fact, those currently on Medicare will be much better off with Improved Medicare for All. Their benefit package will be more comprehensive, their out-of-pocket costs will drop to zero, and the security of the program will increase, since everyone will have a personal stake in seeing it expanded and not cut.
Moreover, it will be simpler. Gone will be all premiums, deductibles, co-insurance, and co-pays. Those who today have their Medicare premiums automatically deducted from their Social Security benefits will see those benefits increased. Gone also will be the impossible tasks of deciding what prescription drug plan best covers one’s future needs, whether to go with so-called Medicare Advantage, and if so, which one, and if not, whether to buy a supplemental plan and if so, which one.
It is important to recognize that there is a thread of a concern that vaguely connects the “socialized medicine” charge and the accusation that current beneficiaries will be hurt. Today, Medicare and Social Security are accurately recognized as earned benefits. To qualify for those benefits, a worker has to have worked and contributed for long enough to be insured, in the case of Social Security and Medicare’s Part A hospital insurance. Workers contribute to the cost of those benefits throughout their working lives, underscoring their earned-benefit nature. Supporters of Improved Medicare for All can and must deal with the sense of current beneficiaries that they earned their Medicare, while it will just be “given” to everyone else, when it is expanded.
The reality is that unlike retirement income, which replaces earned wages, everyone needs health care. The nation has some means-tested programs, like Temporary Assistance for Needy Families, which are designed to alleviate poverty, some earned-benefit programs, like Social Security, which are designed to replace earnings, and some universal benefits, like public parks, freeways, and the police, which are designed to safeguard and improve the lives of all of us.
As much as the American image is one of individualism, virtually all Americans recognize the importance of some communal activities. While Americans differ about whether there should be a military draft, virtually everyone accepts the need for a military paid for collectively. Similarly, public libraries, local fire departments, and public roads and bridges are all seen as public goods appropriately paid for with tax dollars and available to all of us.
With health insurance so tied to employment, it often has to be earned – but it shouldn’t. Having guaranteed high-quality health insurance with no out-ot-pocket costs as a benefit to all Americans is what it means for it to be a right, not a privilege.
It is important to be especially aware of how this subtle attack on national health insurance paid through taxes is perceived not just by Medicare beneficiaries but also by union members. Many unionized workers have been successful in negotiating for excellent health insurance. To obtain the plans, the workers generally had to trade away higher cash compensation. Consequently, it is not surprising that they are reluctant to give them up.
The message to the workers is that, as excellent as their current plans may be, the new coverage will be even better. Union members should be assured, and the Improved Medicare for All legislation should require, that their employers continue to pay what they have been paying in total compensation. Instead of paying that compensation in the form of health care premiums to health insurance corporations, though, the payments will now be in the form of increased current compensation and non-health care benefits.
A related fear tactic to the claim that current Medicare beneficiaries, union members, and others will be worse off is for opponents to tell you that you will lose your current health insurance. The implication is that either it won’t be replaced or the replacement will leave you worse off. It is effective not because people so love their current health insurance, but because the fear of losing even the inadequate coverage you may now have is literally a matter of life and death. It is a classic deployment of people’s aversion to loss. It is another tactic aimed at division.
As a related matter, opponents seek to play on the fear of loss by emphasizing that people will lose choice. Importantly, the choice that people will lose is trivial – to which insurance company their hard-earned money goes.
Most Americans will gain choice in what matters: who their health providers will be. Indeed, Improved Medicare for All will improve people’s ability to get the care they want from the doctors and hospitals they want anywhere in the country and ensure continuity of care.
Another way that opponents have sought to turn people away from Improved Medicare for All is with a sleight of hand. They emphasize that federal expenses will increase resulting in increased taxes or borrowing. Indeed, this same sleight of hand is used to convince too many Americans that today’s Medicare is unaffordable. By focusing on the money going into the government’s coffers and out to providers, opponents seek to convince Americans that Improved Medicare for All will produce “big government,” which is somehow scary and negative.
The truth is that in the modern world, no one is truly opposed to “big” government; it is just that progressives and conservatives have different views of what a big, powerful, modern government should do. Conservatives want a big government military and a big brother government, limiting what women can do with their own bodies, what schools can teach, what museums can display, what kind of gender-affirming care parents, doctors, and children can utilize, how immigrants should be treated, and so on. Progressives want all of us, collectively through government, to ensure every American has economic security in the form of expanded Social Security, health care as a matter of right, a living wage, and more.
If the nation once again has a truly progressive tax system, we can have much greater economic security for everyone. If multimillionaires, billionaires, and multinational corporations were simply required to pay their fair share and the revenue raised dedicated to Improved Medicare for All, that would be sufficient to cover the costs. Even if some revenue were to come from working families, though, their out-of-pocket costs would be considerably lower than today. It is just that the payments would go to the federal government, rather than UnitedHealthcare and other private health insurance companies.
At base, the issue isn’t big government versus small government or increased taxes. It is one of values. That is what supporters should emphasize. Not only will Improved Medicare for All cost less, the money will be spent more productively. Instead of wasteful time spent on the phone appealing denials and seeking pre-authorizations, most of the monies will be spent on paying doctors, hospitals, and other providers.
Another fear tactic is to selectively point to other countries and claim that the quality of care will decrease, at least for the very wealthy, and people will have to wait for inordinately long periods of time for basic care. Importantly, both parts of that framing are untrue. They are both well-cultivated myths. As many people know, the United States is worse than its counterparts in terms of health care outcomes and affordability of care. What is generally not known is that it measures around average or worse in terms of timeliness of care.
The truth is that wait times to see a primary care doctor or a specialist vary among countries that have mandatory, universal health care plans, as do wait times for urgent and non-urgent surgery. Some are longer wait times than patients experience in the United States and some are shorter. Indeed, doctors in other countries are much better at providing care after hours and even make house calls!
What is of legitimate concern are the people who will lose their jobs as our health care system becomes more efficient. That is an issue that proponents of Improved Medicare for All must address. Indeed, proponents not only recognize this responsibility; they include, in their Improved Medicare for All proposals, ways to address it.
Every single job loss is generally a destabilizing event for working families. it is essential that the workers who are displaced are properly treated. Systematic, planned, and consistent outreach should be made to those workers.
One way to alleviate the many fears and concerns that Roosevelt’s “tyrants” are sure to exploit is through an incremental approach, so that Americans will see that they are no worse off, and, in fact, are better off, when Medicare is improved and expanded. Ideally, the incremental steps should combine expansion to additional groups with improvements for current beneficiaries. In that way, current beneficiaries will see clearly the advantage to them. As more Americans receive the benefit, along with an active campaign to assure people additional expansions will leave them better off, not worse off, this natural fear of change should dissipate, and support for expansion increase, like a snowball rolling down a snowy hill.
As long as the final destination remains in mind and is continually invoked, steps that are truly along the way help, but supporters must be wary of disguised alternatives and incremental steps that will hurt the effort. Numerous polls reveal that Medicare for All is an extremely popular idea. Unfortunately, those who oppose the idea of Improved Medicare for All or simply don’t completely understand its striking advantages, have put forward proposals that are decidedly not Improved Medicare for All and, indeed, would not lead us to our desired destination.
The far right is not the only source of these similar-sounding alternatives. Some Democrats have advanced these confusing alternatives. They do so, while seeking to persuade supporters that Improved Medicare for All is not practical, not politically realistic. The assertion that Improved Medicare for All is somehow not able to be enacted may be simply a misguided perception, or it may be a product of the work of the monied interests. In either event, it is destructive and must be taken seriously.
At base, advocates must be wary of steps that appear to point in the right direction, but carry significant risks of derailing the effort. Anything short of a universal, mandated Improved Medicare for All has to be clearly understood as simply a stop along the way, not the final destination. That final destination cannot have an opt in or an opt out, nor include a competing commercial alternative. Just as Social Security is and indeed must be mandatory and virtually universal to work so well, Improved Medicare for All must be, also.
An important lesson from history is that even when victory is achieved, particularly if the victory is incremental, the fight continues. It should be celebrated. It should not be seen, though, that the fight is over. The enactments of Social Security and Medicare were hard fought. Once they were well established and popular, the monied interests sought to prevent their expansion and undermine them from within. Indeed, there are many who today seek to undermine public education with vouchers and charter schools, illustrating that these fights never end.
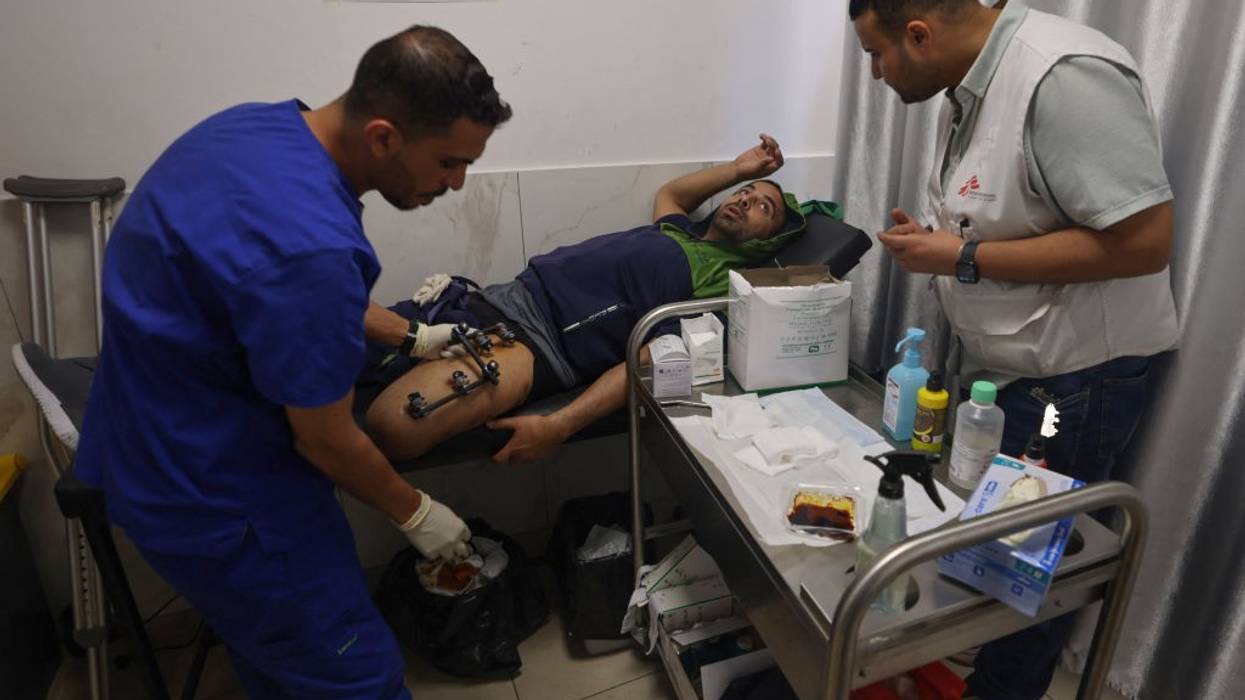
"Support for Israel requires you to be against everything good in this world, like an organization which sends doctors to conflict areas to save human lives," said one observer.
Doctors Without Borders on Saturday condemned allegations made by a British pro-Israel lobby group, which called on Home Secretary Shabana Mahmood to investigate and potentially proscribe the group, whose medical providers and other humanitarian workers provide lifesaving aid in 70 countries and have worked in Palestine during Israel's assault there.
As The Telegraph reported, UK Lawyers for Israel (UKFLI) wrote to Mahmood as well as the Charity Commission and Fundraising Regulator, calling on the Labour government to investigate Doctors Without Borders, also known by its French name, Médecins Sans Frontières (MSF).
The group claimed at least two of MSF's workers who were killed by Israeli forces, physiologist Fadi Al Wadiya and driver Nasser Hamdi Abdelatif Al Shalfouh, had connections to terrorist groups in Gaza.
Palestine Islamic Jihad published a poster earlier this year naming Wadiya as a "martyr commander," and UKFLI claimed Al Shalfouh was a sniper for a Hamas battalion.
MSF acknowledged the poster regarding Wadiya in February and said the medical group "had no indication that Fadi Al Wadiya might have been involved in military activity of any kind prior to his killing by the Israeli Forces."
“If the Israeli authorities had any reliable information about Fadi’s involvement in military activity, they never shared it with MSF either prior to his killing or when we reached out immediately after he was killed to ask for clarifications around the circumstances of his death," the group added. “We would never knowingly employ people engaging in military activity. Any employee who engages in military activity would pose a danger to our staff and patients.”
UKFLI sent its report on MSF to Mahmood asking her to ban the group, as the Labour government proscribed the protest group Palestine Action last year, labeling it a terrorist group under the Terrorism Act. The government took that action after members of the group vandalized planes at a military base.
The designation put Palestine Action on the same legal footing as Al Qaeda in the UK and made membership of the group—or even expressions of support for it—punishable by up to 14 years in prison.
The demand for the same designation for MSF, said former British Army general Charlie Herbert, was "absolutely grotesque."
MSF doctors and healthcare workers have treated thousands of Palestinians in Gaza since Israel began its onslaught there in October 2023 in retaliation for a Hamas-led attack. At least 15 people working with the organization have been killed by Israeli forces. The group is also currently providing humanitarian and medical aid in Sudan as the civil war there has displaced millions of people and collapsed the healthcare system; in Yemen as the conflict between the Houthis and Saudi-backed government troops has escalated; and in the Democratic Republic of Congo, which is facing an Ebola outbreak as well as humanitarian crises exacerbated by years of conflict.
"I work in aid, and when people ask who to support I always say MSF," said researcher and activist Philip Proudfoot. "MSF, wherever I’ve been, are right there on the front, in dangerous conditions, in isolated outposts, providing life-saving support. They’re heroes. UK lawyers for Israel are not fit to wash their scrubs."
US-based researcher Shaiel Ben-Ephraim said the report by UKLFI demonstrates that "support for Israel requires you to be against everything good in this world, like an organization which sends doctors to conflict areas to save human lives."

"It is well past time that the United States joins the rest of the industrialized world and treats healthcare as a right, not a privilege, by improving traditional Medicare and expanding it to everyone."
News that top Medicare Advantage insurers are moving to cut benefits and drop some plans entirely in a bid to boost their profitability came as no surprise to critics of the for-profit US health insurance system, which enriches giant companies and their executives while leaving tens of millions of people in the lurch.
In recent public remarks, executives at Humana and UnitedHealthcare—two of the largest Medicare Advantage insurers in the US—have indicated that the companies plan to exit certain geographic markets and implement other changes deemed necessary to drive "margin expansion," corporate-speak for profits. The changes by the two companies are expected to impact more than a million seniors who receive coverage through the insurers' Medicare Advantage plans, which are privately run but funded by taxpayer dollars.
Wendell Potter, president of the Center for Health and Democracy and a former Cigna executive, told Common Dreams that companies like Humana and UnitedHealthcare "have long made clear they answer to their shareholders, not those they insure."
"These companies are not really in the healthcare business, they are in the business of making money for their shareholders and their executives," said Potter, who now advocates for a Medicare for All system. "They will cut any corner, deny any care, and cut any patient if it helps increase their bottom line."
UnitedHealth Group, UnitedHealthcare's parent company, reported $5.5 billion in profit during the second quarter of 2026, up from $3.4 billion the same time last year. Humana reported $694 million in second-quarter profits.
Recent research led by Mark Meiselbach, a healthcare economist at Johns Hopkins University estimates that "approximately one in 10 beneficiaries in HMO or PPO Medicare Advantage plans will be forced to disenroll from their current plan due to their plan exiting the market" this year. That amounts to around 3 million seniors who will be forced to find a different plan or switch to traditional Medicare during the open enrollment period, which begins next month.
Nancy Altman, president of Social Security Works and author of The Road to Medicare for All: A Call to Action, told Common Dreams that "misleadingly-named Medicare 'Advantage,' together with all private health insurance, is why our nation’s healthcare system is so dysfunctional."
"It mixes healthcare with the motive to make a profit, resulting in the most expensive system in the industrialized world with the worst health outcomes," said Altman. "The recent announcements by UnitedHealthcare and Humana that they plan to exit markets and cut benefits is just one symptom of the dysfunction."
"It is well past time that the United States joins the rest of the industrialized world and treats healthcare as a right, not a privilege, by improving traditional Medicare and expanding it to everyone," said Altman.
A Congressional Budget Office (CBO) analysis published in July found that federal spending per Medicare Advantage enrollee "is projected to be 7% higher, on average," than spending on traditional Medicare over the next 10 years.
The Committee for a Responsible Federal Budget noted that the CBO's analysis "suggests the federal government will spend about $1 trillion on MA overpayments over the next decade." Medicare Advantage plans are notorious for making patients appear sicker than they actually are, reaping larger federal payments.
President Donald Trump pledged during remarks earlier this week to the Republican midterm convention that his administration would "end all payments to big health insurance companies."
But Potter noted that Trump's administration is set to shell out over $13 billion in payments to Medicare Advantage plans this year along.
"If Trump were serious about lowering healthcare costs," Potter told Common Dreams, "he'd break up the monopolies and the for-profit healthcare system."

"At a time when people are scraping by to keep up with the high cost of groceries, rent, and healthcare, this $500 gimmick won’t even begin to dig them out of the hole that Trump and Republicans created."
President Donald Trump said Thursday that his administration would issue $500 rebate checks to some Americans who were purportedly "overcharged" under the Affordable Care Act, a move that would provide little to no relief to the millions of people impacted by surging health insurance premiums.
The White House said in a fact sheet that around a million Americans in 30 states would receive rebate checks, beginning next month—just weeks before the November midterms. Brad Woodhouse, president of the advocacy group Protect Our Care, ripped the rebate plan as "an absolute joke," calling $500 "a drop in the bucket compared to what Americans are paying because Trump and Republicans gutted healthcare to bankroll massive tax breaks for billionaires and big corporations."
Woodhouse was referring to a Republican budget measure, signed into law last summer by Trump, that enacted more than $800 billion in cuts to Medicaid over the next decade.
The GOP also declined last year to extend enhanced ACA subsidies that helped reduce costs for tens of millions of Americans, sending premiums skyrocketing. Some families have seen annual premium increases in the thousands of dollars, leading many to drop marketplace coverage entirely. ACA premiums are set to surge by double digits for a second consecutive year in 2027.
"At a time when people are scraping by to keep up with the high cost of groceries, rent, and healthcare, this $500 gimmick won’t even begin to dig them out of the hole that Trump and Republicans created," said Woodhouse.
The White House said ACA enrollees who "do not receive premium assistance" and who live in states that "use the federal exchange for the operations of their Obamacare markets" would be eligible for a rebate check, meaning the payments would disproportionately benefit enrollees with higher incomes in red states.
"The vast majority of ACA enrollees won't get $500 from the Trump administration, including: those who still get premium subsidies, though what they're paying has gone up a lot with expiration of enhanced tax credits. And, those in mostly blue states that run their own exchanges," noted Larry Levitt, executive vice president for health policy at KFF. "There are 19.2 million ACA enrollees. The Trump administration is talking about sending $500 rebate checks to fewer than one million of them."
Policy experts disputed the Trump administration's claim that Americans were "overcharged" due to the Biden administration's "gross mismanagement" of the ACA. As The Associated Press reported:
Cynthia Cox, a vice president and director of the ACA program at the healthcare research nonprofit KFF, said it’s entirely possible that the funds Trump has promised came from fees collected during Trump’s first term. His first administration collected more user fees from insurers than it spent, resulting in an estimated $1 billion in unspent funds, according to KFF analysis.
It is unclear whether the $500 rebate represents what each enrollee may have overpaid, where the money for the rebates would come from, and whether it requires congressional approval for disbursement.
The White House's rebate check pledge came as Trump also vowed to send $5,000 to every American adult if Republicans retain control of the House and Senate in the November midterms, a promise that was widely derided.
"The 'Trump dividends' scam is just Trump’s latest attempt to distract the country from the Republican affordability crisis," said Rep. Don Beyer (D-Va.). "Trump promised he would lower prices, and instead he keeps mashing the 'make stuff more expensive button.' The American people will not be fooled."

Humana said it is exiting plans covering roughly 600,000 seniors to "drive the intended margin expansion."
Two of the largest Medicare Advantage insurers in the US, UnitedHealthcare and Humana, have signaled in recent days that they plan to exit certain "underperforming" markets and curb benefits in an effort to boost their bottom lines, a strategy that's expected to kick more than a million seniors from their coverage.
On Thursday, Axios cited an analyst note published earlier this week indicating that UnitedHealthcare "has dropped around 13% of plans offered across 18 states." Healthcare Dive reported that the company "expects to end 2026 with up to 1.1 million fewer MA members than it had last year."
"UnitedHealthcare—the largest MA insurer in the US—offered plans in one fewer state and 109 fewer counties this year, cut allowances for certain over-the-counter health and wellness items, and prioritized plan designs with more limited provider networks," Healthcare Dive noted. "The company also shifted commissions to brokers to incentivize enrollment in more profitable plans."
As for Humana, the company's chief financial officer said during an earnings call in late July that its exit from certain markets and dropping of specific plans would "impact approximately 600,000 members" as the firm implements "the changes necessary to drive the intended margin expansion."
Seniors who lose their MA plans in response to the insurance giants' moves will have to either find a new plan during open enrollment, which begins next month, or switch to traditional Medicare. MA plans currently cover more than half of all eligible Medicare beneficiaries.
Mark Meiselbach, a healthcare economist at Johns Hopkins University, has estimated that nearly 3 million people enrolled in MA will be forced to switch coverage this year due to insurers canceling their plans—which Meiselbach describes as "forced disenrollments."
“For most enrollees, they will likely be able to still find a comparable MA plan,” Meiselbach told Investopedia last week. “However, no two plans are exactly the same. They may still have access to their same primary care provider, but have to undergo new prior authorization for a medication or lose a supplemental benefit they relied on.”
The companies laid out their profit-boosting strategies months after the Trump administration provided a substantial payment increase to Medicare Advantage plans, which are run by private companies and funded by taxpayer dollars. MA companies are notorious for denying necessary care and overbilling the federal government through practices such as upcoding, whereby patients are made to appear sicker than they are to reap a larger federal payment.
"President Trump, Dr. Oz, and leaders in Congress have talked a big game for two years about reining in waste, fraud, and abuse, but instead they increased insurer payment by multiple times more than what the administration originally proposed," Anthony Wright, executive director of Families USA, said in response to the April payment hike.
During his remarks to the GOP midterm convention on Wednesday, President Donald Trump vowed to "stop all government payments to big insurance companies"—an apparently inadvertent call for the elimination of privately run Medicare Advantage plans, which received over $534 billion from the federal government last year.

The pessimistic view that we are moving in the wrong direction sees only the waves at the surface. It misses the subterranean tremors underneath. If we fight, we can win.
As policy-wise and popular as Improved Medicare for All is, the nation may appear to be as far away from enacting Improved Medicare for All as possible. During his first term, Trump did what he could to accelerate the privatization of Medicare. Unfortunately, his thumb on the scale in favor of privatized Medicare is not only back, but is on steroids.
Adding to the sense that the nation may be as far away from Improved Medicare for All as possible, the Republicans enacted legislation that is projected to cause 15 million people to lose their health insurance. Adding to the sense that we are nowhere near enacting Improved Medicare for All, the two prior presidential elections, in 2016 and 2020, saw Senator Bernie Sanders (I-Vt.) and Senator Elizabeth Warren (D-Mass.), two leading champions of Medicare for All, lose in the primary to the more centrist candidate Hillary Clinton, in 2016, and Joe Biden, in 2020. Trump defeated Clinton and won a second term in 2024 against Vice President Kamala Harris. Though Harris did not mention the fact in her presidential campaign, she was an original cosponsor of the Sanders-authored Medicare for All Act.
Trump’s election to a second term, the Republican control of Congress (as these words are written), and a Supreme Court with two-thirds of the justices who are acting as Trump advocates rather than independent jurists appear to suggest that the nation is moving away from national health insurance. But it is crucial to recognize that today is only a snapshot in time. The pessimistic view that we are moving in the wrong direction sees only the waves at the surface. It misses the subterranean tremors underneath. The Republican cuts to health insurance are already putting a strain on rural and inner-city hospitals, as well as nursing homes. The nation is seeing hospitals close as a result of the enactment. Their closure, in turn, strains even those hospitals and nursing homes not directly affected by the cuts.
Improved Medicare for All won’t magically become a reality. It will take all of us who support it to fight for it, in small and large ways.
With the cost of health care rising and, with it, increased insecurity, a majority of the electorate are concluding that the nation is moving in the wrong direction. Perhaps even more significantly, it will become clearer and clearer that the current path is unsustainable.
Importantly, two action-forcing events requiring Congressional legislation are on the horizon. Social Security and Medicare Part A, by law, can only pay benefits if they have sufficient dedicated revenue to cover their costs. To avoid an automatic across-the-board reduction of around 20 percent of the monthly Social Security benefits received by more than 70 million beneficiaries, and to avoid hospitals no longer being reimbursed, Congress must act. However the precise dates shift over the next few years, Congress unquestionably will have to act in the next half decade or so, before the revenue is insufficient to continue to pay full benefits.
Those action-forcing events provide an opportunity. Because those action-forcing events will result in must-pass legislation, provisions that expand Medicare, as well as Social Security, could be included. To make that a reality, though, it is essential that those who support Improved Medicare for All are fully prepared.
Improved Medicare for All won’t magically become a reality. It will take all of us who support it to fight for it, in small and large ways. The wonderful news is that determined activists are currently working hard to make Improved Medicare for All the law of the land. Building a winning coalition and other steps are already underway.
It is imperative that a winning coalition is built strong enough to defeat those who will fight against Improved Medicare for All. Physicians have been extremely active politically since the United States first started to seriously debate universal health insurance at the start of the twentieth century. Initially, the American Medical Association, whose members in 1910 comprised more than half the doctors in the nation, endorsed the legislation under consideration. Individual doctors, however, strenuously objected and made those objections known through their state medical societies. As a result, in 1920, the AMA’s House of Delegates formally voted to reverse its support, and instead opposed the initiatives.
While the AMA has been a staunch opponent ever since, that may be changing. Though the AMA has opposed national health insurance for over a century, doctors have much to gain from it. The image of the self-employed family doctor who makes house calls is virtually an anachronistic image. Today, around four out of five physicians – 77.6 percent – work for corporations. Historically, doctors have expressed concern over government oversight and interference. More and more, though, physicians’ reality is that they now live under commercial insurance oversight and interference. Unlike elected officials for whom Americans vote and whose salaries are set and paid transparently from public funds, doctors have no say over who runs private insurance companies and how they are operated.
A survey of doctors conducted by the Chicago Medical Society found that 66.8 percent had favorable views of a single-payer system.
The doctors most active in support of Improved Medicare for All are the leaders and 25,000 members of Physicians for a National Health Program (PNHP). They have provided a clear and steady voice on the issue since their founding in 1987. In part because of PNHP’s sustained effort, doctors seem to be moving toward support for Improved Medicare for All. A survey of doctors conducted by the Chicago Medical Society found that 66.8 percent had favorable views of a single-payer system. In fact, when asked to choose between Medicare for All and an improved Affordable Care Act (colloquially known as Obamacare), the doctors chose Medicare for All by two to one!
The increasing support among doctors for Improved Medicare for All is likely in large part a response to how vexing and inadequate the current system is for all participants, including doctors. The increasing support for Improved Medicare for All may also reflect a more diversified pool of physicians. When Medicare was enacted in 1965, doctors were overwhelmingly white men, who tended to identify as Republicans. Accordingly, the AMA gave the majority of its campaign contributions to Republican candidates. Ninety-four percent of the medical students at that time were men. Only 2.5 percent of practicing physicians were African-American, generally having been trained in segregated settings. An even tinier 0.2 percent of medical students were Hispanic or indigenous at that time.
In contrast, women comprised 55.1 percent of the entering classes in accredited medical schools across the country for academic year 2024-25. That was the sixth year in a row that women made up the majority of medical school students. They comprised 54.9 percent of total enrollment. African-Americans comprised 10.3 percent of total enrollment, and Hispanics, 12.3 percent. In 2021, more than one out of four surgeons and other physicians – 26.5 percent – were foreign-born.
Led by PNHP, advocates of Improved Medicare for All must have a focused strategy geared toward physicians to solidify the support of doctors, with the goal of converting the AMA from a force in opposition to a force in support. With a focus on improving the quality of medical practice while compensating its providers adequately, along with improving Medicare and extending it to everyone, the goal for supporters of Improved Medicare for All should be to convince doctors to become a force for its enactment.
Physicians have been perhaps the hardest opponent to overcome in the past, because of the extremely close relationship they have had historically with their patients, who rely on their doctors when their lives are literally on the line. When doctors give patients advice, those words carry enormous weight, even if the advice is about whether universal health insurance would lead to better or worse health care. If physicians tell their patients the proposed legislation will harm their practice and therefore their patients’ health care, that is influential.
While attaining the support of the AMA can likely be achieved with concerted effort particularly and primarily by physicians themselves and would be extremely valuable, that support is not essential. After all, Medicare was enacted despite the AMA’s strong opposition. Moreover, while doctors historically have been extremely influential with their patients about health policy, and they remain so, the need to change doctors because they are no longer in-network and the increasing reliance on teams of healthcare providers, including nurses, nurse practitioners, and physicians’ assistants, have increased the influence of nonphysician providers.
Nurses are another key group, and fortunately they have been leading the fight for Improved Medicare for All. Unlike the AMA, National Nurses United (NNU), the largest professional association of registered nurses, with 225,000 members nationwide, has been advocating for Improved Medicare for All for decades, with determination and effectiveness.
Following the lead of the AMA, the American Hospital Association (AHA), which represents nearly 5,000 hospitals, has opposed the last century of efforts to enact national health insurance. Improved Medicare for All, with its guaranteed payments to providers, its ability to incentivize healthcare providers to practice where the need is highest, and its ability to use tax dollars to subsidize the most at-risk hospitals, is a solution. Though the AHA does not yet support Improved Medicare for All, advocates may be able to persuade individual hospital administrators and, over time, the AHA itself to recognize the advantages of Improved Medicare for All and join the effort.
Another powerful group that started as supportive in the early years but then quickly switched were employers, who worried about the cost to them and the potential government interference in what they considered their independent authority. Though they still oppose it today, they might be persuaded of its value to them because healthcare costs have grown so substantially, and the lack of universal national health insurance puts them at a competitive disadvantage to their foreign counterparts.
Most companies are primarily focused on the cost of health care and, therefore, should be open to Improved Medicare for All, if they are convinced it would reduce their costs. There are some industries, though, that have an overwhelmingly strong stake in the current inefficient, costly system. Pharmaceutical manufacturers, pharmacists, and their associations have been aggressive parts of the opposition from the beginning. Another opponent has been the insurance industry. Neither pharmaceutical companies nor health insurance companies are likely to be convinced to end their opposition to Improved Medicare for All. Pharmaceutical companies take advantage of the bloated system to make extraordinary profits. Under Improved Medicare for All, the pharmaceutical industry will still make profits. Price gouging, however, will stop. Similarly, health insurance companies, for which Improved Medicare for All is an existential threat, will fight as hard as possible.
Health care is a matter of life and death for virtually all of us at some point in our lives.
Those monied interests must be defeated – no easy task given their vast resources. As powerful as they are, history shows that they can be beaten. They can be defeated, if the electorate is engaged and determined. The way to defeat those stakeholders that cannot be convinced of the benefits of Improved Medicare for All is with ongoing motivated action at both the grassroots and grasstops levels. The strong antipathy to commercial health insurance, exposed by the murder of the UnitedHealthcare CEO, reveals that the public may be ready to fight persistently, relentlessly, and effectively for accessible, affordable, high-quality health care for all.
History reveals that Americans’ support for national health insurance is generally widespread and strong at the start of the public push, likely because the need is so great, but that support can easily be shaken. Polling shows that support for Improved Medicare for All is susceptible to opposition messaging that invokes fear of loss and danger. That is not surprising, because health care is a matter of life and death for virtually all of us at some point in our lives. The challenge will be to keep people motivated and not swayed by half-truths and lies, which history demonstrates opponents are willing to deploy. The uber-wealthy want to defeat anything that will increase their costs and reduce their wealth, even by a little. They will seek to scare the American people to retain the status quo. Obviously, fear of failing to obtain adequate health care when needed is an extremely powerful fear that can be exploited.
A key player in maintaining the active support of the American people is organized labor. Studies show that union members are more likely to vote, to volunteer for candidates, and to be influenced by their union leadership in political matters generally. Importantly, they remain a counterweight to the corrosive power of self-interested billionaires and multinational corporations. While organized labor can be counted on, it does have concerns that should be addressed. These include the fact that in negotiating for the generous healthcare plans their members enjoy, they had to trade away current compensation. Moreover, some workers involved in the administration of the current wasteful system will lose employment as a result of the greater efficiency of Improved Medicare for All. Both of those concerns should be addressed as part of the fight for Improved Medicare for All. Both issues are discussed in greater detail in the next chapter, which focuses on the counterattack.
A crucial part to winning the fight for Improved Medicare for All is extremely careful messaging to strengthen the commitment and effort of supporters and to win over those who may be skeptical.
As part of the effort to enact Improved Medicare for All, advocates must be an active part of the fight for workers’ rights to unionize and build union strength. In addition, advocates must employ a careful strategy, in addition to relying on unions, to convince the American people to fight for Improved Medicare for All.
Using the right messaging is key. While the majority of Americans favor Improved Medicare for All, polling indicates that the support can be shaken simply by the way the issue is framed. For example, while 63 percent have a positive reaction to the phrases “Medicare for all,” and “Universal health coverage,” that reaction drops to 49 percent when the phrase is “Single-payer health insurance system,” and 43 percent when the proposal is called “Socialized medicine.” People’s opinions can change dramatically depending on what is emphasized. When those polled are told that Medicare for All will increase their taxes, support drops to just 37 percent. When, though, they are told there will be no premiums and out-of-pocket costs will be reduced, support increases to 67 percent. Indeed, when those polled are told that the proposal guarantees health care as a right for all, support jumps to 71 percent.
This means that a crucial part to winning the fight for Improved Medicare for All is extremely careful messaging to strengthen the commitment and effort of supporters and to win over those who may be skeptical. While the facts are important and strongly on the side of advocates of Improved Medicare for All, history teaches that winning must include effective messaging that is repeated frequently.
Careful strategizing and messaging are especially crucial with respect to older Americans who are Medicare beneficiaries or are about to become so. Seniors have, on average, the greatest need for health care and are the most reliable voters. History shows that they generally pay keen attention to conversations about retirement security and health care. Older Americans were key to the enactment of Social Security in 1935 and its improvements ever since. They were also key to the enactment of Medicare in 1965. History also reveals, though, that the deployment of fear tactics targeted toward seniors can be effective, unfortunately. Consequently, it is vital that proponents of national health insurance have a systematic strategy with respect to seniors, including careful messaging.
In particular, the name Medicare for All may be a two-edged sword. The name presumably tests so well because Medicare, having completed its 61st year, is widely known and understood. Virtually all Americans know people who currently are covered by Medicare and appropriately expect to be covered themselves one day, if they aren’t currently. Consequently, it is harder to demonize as something scary, foreign, and potentially dangerous.
As important as the enactment of Medicare was, both in its own right and as a first big step toward Improved Medicare for All, its creation established a part of the population that might believe that they have something to lose by its expansion to others. Opponents can and have played on the fear that expanding Medicare to the entire population will dilute it and endanger it. For this reason, it may be prudent to always call the proposal, as this book does, Improved Medicare for All.
Starting with the word, “improved” subtly emphasizes that it will benefit those currently on Medicare. The improvements make the proposal a winner for current beneficiaries. It will eliminate all of their out-of-pocket costs. Its long-term care coverage will be a lifesaver for one out of every three seniors and their families. That coverage of long-term care will end the need for seniors to spend all of their assets to qualify for Medicaid and the care they need. Instead, it will allow seniors to pass on whatever savings they have accumulated to their children and grandchildren. Moreover, simply the knowledge of that coverage will provide everyone with greater peace of mind.
For those who today have traditional Medicare, Improved Medicare for All will provide them with hearing, vision, and dental services. And it will free everyone from the complicated sign-up process that current Medicare enrollees must wade through for prescription drug coverage, Medigap coverage, and, for increasing numbers, the erroneously-named Medicare Advantage. In that regard, though, supporters must have a strategy for those who are enrolled in Medicare Advantage. The ending of Medicare Advantage is particularly challenging to message, because it is extremely popular at least until people get seriously ill, when its extra benefits are of less concern and its narrow network of providers and deny/delay tactics are life-threatening. How to message Medicare Advantage, as well as messaging more generally to seniors, is dealt with in greater detail in the next chapter. The basic point, though, is that messaging specifically aimed at reassuring and enlisting seniors must be a key part of a winning strategy.
Fundamentally, advocates must be astute about employing the most effective messaging. The issue should be constantly polled and the messaging refined, as part of an overarching strategy and game plan. The bottom line, though, is that a winning strategy must include careful messaging that is snappy and compelling, but brief. The messaging must be used repeatedly, consistently, and widely.

"The most serious risk is premature death," said one physician.
A senior Iranian health official on Tuesday accused the United States of deliberately targeting Iran's medical infrastructure amid a worsening shortage of critical medicines as President Donald Trump's illegal US-Israeli war of choice against Iran drags on.
Iran's pharmaceutical system is straining under US bombing, blockade, and sanctions that have severely disrupted trade and transportation in the Middle East nation of around 90 million people. Iranian officials say shortages of roughly 800 medicines—including dozens of essential drugs—are affecting the treatment of cancer and other serious illnesses.
“The enemy has identified medicine as one of the sensitive areas of the country, and is trying to denigrate and portray Iran’s conditions as unfavorable by releasing content in the press and social media," Deputy Health Minister Mahdi Pirsalehi, who also heads Iran's Food and Drug Administration, told Al Jazeera.
Pirsalehi has said that more than 50 factories and pharmacies have been damaged or destroyed by US and Israeli bombing during the six-month war. The attacks have exacerbated existing shortages.
One gastroenterologist and university professor in Tehran, who spoke to Al Jazeera on condition of anonymity, sounded the alarm on what she called a "staggering" rise in drug prices—including for domestically produced generic medications—caused in significant part by the US naval blockade.
“Reports that rotavirus vaccine imports have been halted because of the maritime blockade—and that influenza vaccines may soon face the same problem—represent a serious and alarming threat to nationwide efforts to prevent vaccine-preventable communicable diseases,” she said.
“Runaway inflation, poverty, and inadequate access to essential food groups among vulnerable populations, including infants, children, and pregnant women, signal the onset and spread of malnutrition,” she added, warning of the risk “of both communicable and noncommunicable diseases, creating a vicious cycle in which malnutrition develops and progressively worsens."
For ordinary Iranians, empty pharmacy shelves, delayed treatments, and prohibitively expensive prescription drugs have become the new normal.
One Iranian pharmaceutical company recently announced price increases for scores of drugs, including a 543% rise in the price of the Alzheimer's medication donepezil, a 308% higher cost for the antibiotic clarithromycin, and a 135% spike in acetaminophen and diphenhydramine syrups, according to reporting by Tasnim News Agency.
Dr. Hassan Nayeb Hashem told Deutsche Welle last month that "for many specific diseases, there is effectively no substitute" for prescribed drugs.
"If the medicine becomes inaccessible, patients can develop complications much sooner," he said. "The most serious risk is premature death."
One patient requiring testing for an abdominal and pelvic mass recently told Iran International that CT and MRI scans now cost over $100, even with Social Security insurance—the equivalent of a month's pay for many Iranians.
“How are we supposed to pay these costs with such meager incomes?” they asked.
A 33-year-old man said the exorbitant cost of dental treatment has left him without half of his teeth.
“I feel like I’m 60,” he said. “The bitter part is that this humiliating way of life has become normal for me.”
Another Iranian said they feared what would happen if anyone in their family got sick this winter.
“We’re stressed about where we would get the money for treatment," they said, "if God forbid we or our children even catch a cold."

"War is driving Sudan’s needs; funding cuts are shrinking the response."
The renowned humanitarian group Doctors Without Borders said Tuesday that the Trump administration's destruction of the US Agency for International Development has contributed to the collapse of the war-torn nation's healthcare system, forcing clinics to close and leaving millions of people without access to lifesaving treatment.
The organization, known internationally as Médecins Sans Frontières (MSF), said the closure of USAID last year at the behest of President Donald Trump and the world's richest man, Elon Musk, left many healthcare providers in Sudan "unable to find alternative funding to continue providing services," leaving facilities with no option but to shut down in the midst of a worsening humanitarian catastrophe.
"War is driving Sudan’s needs; funding cuts are shrinking the response,” Muhammad Ibrahim, MSF's head of mission in Sudan, said in a statement on Tuesday. “MSF’s work in Sudan is privately funded. But when funding disappears from other health services, clinics close, patients have fewer places to go, and pressure shifts to the facilities that remain, including ours.”
MSF said its hospital in Um Rakuba, a refugee camp in eastern Sudan, is now "the only lifeline left" for locals and refugees.
"The cuts here go well beyond healthcare," emphasized Fabrizio Locuratolo, MSF humanitarian affairs manager. "Food rations are shrinking and protection programs are being dismantled, pulling away the last safety nets and leaving refugees completely exposed.”
The dismantling of USAID by Musk's wrecking crew at the so-called US Department of Government Efficiency has already killed hundreds of thousands of people—most of them children—according to experts tracking the impacts on humanitarian aid around the world. Musk and the Trump administration have continued to deny that the aid cuts have killed any children.
A study published in The Lancet earlier this year estimated that the gutting of USAID—whose surviving programs were mostly transferred to the US State Department—could result in more than 14 million additional deaths by the end of the decade. The US Department of Agriculture took over USAID's Food for Peace program—and subsequently omitted Sudan from the list of countries that would receive shipments of US grain.
MSF said Tuesday that "just as health providers faced the impending removal of US support, many European governments also reduced their assistance to people in Sudan."
The results have been horrific. MSF said that "malaria and malnutrition cases are already rising despite limited rainfall, ahead of the peak of the rainy season—and we expect numbers to increase as the rain intensifies."
"In August, our teams admitted 191 children under five with severe malnutrition to our inpatient feeding center, and nearly 22% also tested positive for malaria," the group said Tuesday. "The UN reports that 825,000 children under five are expected to suffer severe acute malnutrition and 19.5 million people faced crisis-level hunger earlier this year. Yet the UN’s $2.87 billion response plan is barely 41 per cent funded, and 37 per cent of Sudan’s health facilities are estimated to be completely out of service."
"As world leaders gather at the UN General Assembly, governments and institutional donors must protect funding for essential health services in Sudan and provide flexible transitional financing where facilities are at risk of closure," the organization pleaded.

The wrong question is how can we afford Improved Medicare for All. Rather, the right question is how can we afford not to enact it.
Editor's Note: The following is the second excerpt from Nancy J. Altman's latest book, The Road to Medicare for All: A Call to Action (Routledge, 2026), now available for purchase wherever quality books are sold. Read the first excerpt published by Common Dreams here. As the United States continues to spend substantially more on health care than other wealthy nations but with poorer health outcomes, Altman's book analyzes the dysfunction of the current system and sets forth the solution. "Medicare for All won’t happen without a fight," she argues, "but it is a fight we can win."
Imagine having more money in your pocket. Imagine being able to see any doctor you want without checking whether the provider is in your network and covered by your insurance. Imagine having more time with your doctor and, at the end of the appointment, simply walking out the door without having to take out your wallet or even ask what you owe for the visit. Imagine being free of filing insurance claims. Imagine being able to simply get any medicine your doctor prescribes without discovering it is exorbitantly expensive and asking your doctor what, if anything, they can prescribe that is covered by your insurance. Imagine no such thing as medical debt. Imagine simply getting the care, procedures, hospital stays, therapies, and medications your doctor prescribes with your only focus and thought being on how to restore and optimize your health. That is what you will experience.
Where is that destination? It is tantalizingly close. In fact, those who, on average, have the greatest medical needs—seniors and people with disabilities—are already almost there. Medicare, having recently celebrated its 61st anniversary, is well known to Americans. Most people are either covered by Medicare or know someone who is. It already covers Americans from age 65 to the grave. To reach the destination that health care is a right, not a privilege, with all those imaginations a reality, it has to be extended back to the cradle and improved, so that its coverage is completely comprehensive and available without premiums, co-payments, co-insurance, or deductibles. (To be clear, the destination is the expansion of traditional Medicare, not privatized Medicare—the deceptively named Medicare Advantage—whose serious shortcomings are discussed throughout this book.)
As important as Medicare is... it should be improved.
Medicare, which currently covers only seniors and people with disabilities—those who, on average, have the highest healthcare costs—does so more efficiently, comprehensively, and fairly than commercial insurance does, or indeed can. Medicare is the most important birthday gift those turning age 65 get. Too many Americans in their late fifties and early sixties lack adequate health insurance and desperately seek to hang on until they reach that special birthday that brings Medicare. As important as Medicare is, though, it should be improved. As Chapter 3 explains, soon after Medicare was enacted and expanded to people with disabilities, the most powerful forces organized against it. They succeeded in stopping further expansion of its coverage and the services and treatment it provides. They also stood in the way of reducing the costs of those it covers.
On the road to Improved Medicare for All, traditional Medicare should be expanded to cover all essential services. As the nation is driving toward Improved Medicare for All, traditional Medicare should be expanded to cover all safe and effective prescription drugs, also. Under the current system, without Medicare simply covering all safe and effective prescription drugs automatically at no cost, beneficiaries must repeatedly answer the following impossible, ludicrous questions: What illnesses will you contract next year? What medications will your doctor prescribe to treat those yet-to-be-contracted illnesses? Only if you know the answers to those unanswerable questions, can you intelligently decide, in today’s dysfunctional system, which insurance plan has the right drug formulary or list of covered drugs at a price you can afford.
Expanding traditional Medicare to cover all prescription drugs will mean that people can fill all of their prescriptions without worry about their cost. In addition, Medicare should be expanded to cover long-term care—both care at home and in nursing homes.
If Medicare were expanded to cover in-home services and supports as well as nursing home care for those who had no other alternatives, people who were able could age at home, as most want, with the security to know that they would not be a financial burden to those they love. An expanded Medicare for All would meet Americans’ needs today and their unforeseeable needs in the future. As it does today for seniors who have traditional Medicare, it would pool risk among everyone so that everyone is protected; people with costly and complex medical conditions would not be saddled with huge costs.
Under today’s patchwork system, out-of-pocket costs in the form of deductibles, co-pays and co-insurance force people into the arms of commercial insurance, whether they like it or not. Those with traditional Medicare must buy, if they can afford it, private supplemental insurance, colloquially known as Medigap, since traditional Medicare lacks an overall cap on out-of-pocket expenses. Those who can’t afford Medigap may be forced to purchase an inadequate Medicare Advantage plan which includes an overall cap, one more thumb on the scale placed by those who are hostile to single-payer health insurance.
With comprehensive coverage, without co-pays, co-insurance, deductibles, or premiums, there will be no need for supplemental, so-called Medigap, private insurance. We do not pay out of pocket for public libraries, schools, fire protection, or the military. Rather, those services are paid from taxes. We should not be required to pay out of pocket for health care, either. Like those other services, we should have universal, national health insurance, paid for completely out of taxes. The United States is the wealthiest nation in the world at the wealthiest moment in its history. It doesn’t feel that way to many, because so much of that wealth is concentrated in the hands of the very few. A fairer system of taxation which finances an Improved Medicare for All would allow all of us to share the wealth that all of us have created.
We do not pay out of pocket for public libraries, schools, fire protection, or the military. Rather, those services are paid from taxes. We should not be required to pay out of pocket for health care, either.
The nationwide network of Improved Medicare for All providers, which would likely cover all doctors and hospitals nationwide, would ensure that people can continue to get care from the doctors they know and trust. Everyone would be free to see doctors and use hospitals anywhere in the nation. There would be no restrictive networks that keep people from using centers of excellence and seeing the doctors they want to see, including the best specialists. Improved Medicare for All would ensure that everyone—people with costly and complex conditions, people who want good specialty care from doctors and hospitals they know and trust, people who need continuity of care, and those who are currently in excellent health—could get needed health care without financial stress or anxiety.
Improved Medicare for All is fully affordable. Given the unsustainability of the current system, as described in the last chapter, the wrong question is how can we afford Improved Medicare for All. Rather, the right question is how can we afford not to enact it. Relatedly, Improved Medicare for All will cost less than we pay currently. Consequently, the other correct question is not how are we going to pay for Improved Medicare for All, but, rather, how should we divvy up the savings!
Improved Medicare for All will save the nation trillions of dollars while covering everyone comprehensively. In addition to money saved, Improved Medicare for All will save lives. It will result in a higher quality of life for individuals and also a healthier population overall, generating greater productivity for the nation as a whole. Doctors will have more freedom and flexibility. They will be free from the micro-management of commercial insurance companies, concerned about turning a profit.
An Improved Medicare for All system will provide dependable income to healthcare providers. They can count on their bills being paid in a timely manner without the need to chase patients or, even more dispiriting, seek the assistance of loan collection agencies.
Part of the savings should go to doctors, nurses, and other providers to ensure that they are well compensated. They should do better under Improved Medicare for All, not just financially, but also in terms of job satisfaction and time to focus on healing, not paperwork.
Hospitals and those they serve will do better, as well. Improved Medicare for All can reduce physician shortages in underserved areas, often described as healthcare deserts, and help to reduce shortages in areas of medicine where they exist now or are projected to exist. Rural hospitals too often have limited staff without backup. The loss of a surgeon can cause the surgical unit to close, which, in turn, can have a cascading effect, ultimately resulting in the inability to receive care close by, quickly, in an emergency.
Despite all the advantages, Improved Medicare for All won’t happen without a fight.
Like the need to reimburse doctors fairly, in a timely manner, hospitals must be, as well. Whether for-profit, nonprofit, or governmental, hospitals want to remain state-of-the-art, with the latest equipment, and be fully staffed. Consequently, they need to cover their costs and ideally, maintain reserves. Under Improved Medicare for All, hospitals will have reduced costs along with more certainty and dependability of payments, free from charitable cases, which will become a thing of the past. In addition to fairly reimbursing hospitals and other facilities, the costs of maintaining, updating, and constructing them should be a priority, so that all communities are adequately served. At base, under Improved Medicare for All, hospitals, physicians, nurses, and other practitioners should be paid generously. They can and should be paid fully and on a timely basis for care given to every patient. Improved Medicare for All can and should be structured to ensure that providers have the ability to spend the time required to see patients.
In addition to all of the health and health-related advantages that Improved Medicare for All will bring, it can also usher in improvements unrelated to health care. They include a fairer federal tax system, together with reduced income and wealth inequality; more revenue for Social Security; an improved system of workers’ compensation, and more funds for state governments. Improved Medicare for All will provide intangible benefits for everyone, including reduced stress, less paperwork with the accompanying added free time, and, most importantly, greater peace of mind. All of those byproducts are explained at length in the book. They are just some of the fortuitous byproducts that will accompany the enactment of Improved Medicare for All.
Despite all the advantages, Improved Medicare for All won’t happen without a fight. The special interests will fight ferociously, but they will be no match for the hundreds of millions of Americans who will be benefited, as long as the public is engaged and active.

The work that our families run on often happens where no one can see it. This Labor Day, as midterms near, I'm thinking about what it will take for the people who do that work—and the people who depend on it—to finally be counted.
What does it say about this country when you can work for more than 40 years and still can’t afford to stop?
I am 66 years old and have spent over 30 years caring for children across the South. When 2024 drew to a close, I tried to retire. I thought I had put in enough time to set myself free from the labor of surviving this economy.
But, as I worried, I couldn't afford it. The price of everything was increasing, including bread, and I realized I had no choice but to return to work within six months of my retirement.
You can tell workers like me that we should have saved more, planned better, chosen a better path toward our retirement. But here’s the problem many domestic and care workers encounter: You cannot save money you never had. When wages barely cover housing, groceries, medicine, and everything else life throws at you, retirement is less like a plan and more like a luxury. In 2025 (the year I was supposed to be retired), early educators had a median wage of $34,980. Other domestic workers, like house cleaners make an estimated median wage of $34,650, and home care workers in 2025 had a median annual income of $22,429. These wages reflect the reality that domestic workers overall are three times as likely to live in poverty as other workers.
With seven children and 18 grandchildren, I do not want another generation of women in my family to inherit a country’s economy where caring for others means giving up their own security.
I come from a legacy of domestic workers. My grandmother, Big Momma, was a Certified Nursing Assistant. My mother was a housekeeper. I became a childcare worker. Three generations of Black women in my family have cared for other people.
We are part of a much longer history, and that is why this work has never paid what it should.
In 1881, 20 Black laundresses organized a movement that grew to nearly 3,000 members and won better wages after striking. Nearly a century later, Dorothy Bolden organized domestic workers across this same city and founded the National Domestic Workers Union of America. Bolden understood that better working conditions and civic power went hand in hand and even made voter registration part of the strategy to organize domestic workers.
When this country finally wrote basic protections into law, such as the right to organize, a minimum wage, and a path to retirement, domestic workers and farmworkers were left out of these protections. That was intentional. Much of that work was done by Black women in the South; leaving it unprotected was no accident. A multigenerational legacy later, we are still living with the consequences these gaps created.
It’s why a person can care for children for over 32 years and still not be able to afford to retire. We didn’t fail to plan; our work was just kept out of sight and out of the protections other workers won.
For most of my career as a childcare worker, children knew me as Miss Cathy. If one of them came to me crying because they were being bullied or something was wrong, I would tell them, "Miss Cathy is going to get to the bottom of it." And trust that Miss Cathy always did.
I adore my work and the children I care for. But loving your work should not require sacrificing your own security.
Or your health.
I have Graves’ disease—a disease that is twice as likely to impact Black women—and often, we face delayed diagnoses and advanced symptoms because of healthcare disparities. For years, I managed it by going to quick clinics when I could afford them and, most of the time, went without care when I couldn't. It was ironic: I was spending my days making sure other people's children were cared for while struggling to afford consistent care for myself. It was not until I turned 65 and qualified for Medicare that I finally had access to health coverage. And even that coverage is at risk.
But this essay is not meant to share all of the challenges I face in care work. No, I am writing this to emphasize that I am no longer the exception. We, as working-class people, have become the rule.
Across the United States, retirement is slipping out of reach for working people of every kind. Wages have not kept up with the cost of the roof over our heads, a simple doctor's visit, a full grocery cart, or care of any kind. More and more people are working into their late 60s, 70s, even 80s, not because they want to, but because stopping simply is not an option. For me, I work until God tells me to stop. The insecurity I’ve referenced has always shadowed domestic workers, and now it’s reaching the rest of the working class. My story reflects the lives of so many working people.
But domestic workers are building a constituency around care: domestic workers, family caregivers, parents, and everyone who understands that care is not some niche issue. It is part of whether a family can afford to live and whether the people who provide that care can afford to grow old, in my case, preferably with a crisp beverage on a beautiful beach.
The economy and affordability are on people's minds. It’s the only thing that’s on my mind. My bank account tells me that things are expensive.
For Black women like me, the right to be heard was never simple. Our grandmothers cleaned other people's homes and were told their voice did not matter in their own country. My father, who raised my siblings and me in 1960s Memphis, taught us that sitting out of the civic process was not optional; he refused to be invisible, and engaging with elected officials was a way to ensure that.
And it is not only domestic workers who have a stake in this. Every family with childcare needs, every person with an aging parent or disabled loved one at home, all of us who will need care someday—we all deeply depend on this work. When we make that care visible, when we insist that it be counted and prioritized, we are looking out for one another.
I want the people in elected office to hear that childcare lets parents go to work, that home care lets people live with dignity, and that we, the people who do that work, should be able to retire from it one day.
Domestic workers are more than our labor. We are neighbors, parents, and grandparents.
With seven children and 18 grandchildren, I do not want another generation of women in my family to inherit a country’s economy where caring for others means giving up their own security.
My grandmother cared for people. My mother cared for people. I spent 32 years caring for children. We have done our part.
This Labor Day, I want the people who represent us—and the country we have spent our lives caring for—to show us they will do theirs.
And if they don't, Miss Cathy is going to get to the bottom of it.