

SUBSCRIBE TO OUR FREE NEWSLETTER
Daily news & progressive opinion—funded by the people, not the corporations—delivered straight to your inbox.
5
#000000
#FFFFFF
To donate by check, phone, or other method, see our More Ways to Give page.
Daily news & progressive opinion—funded by the people, not the corporations—delivered straight to your inbox.
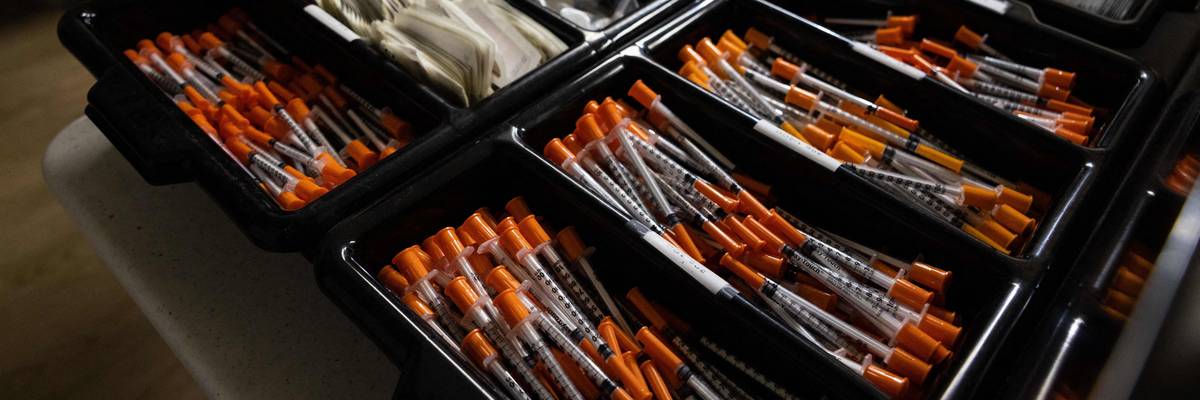
In this November 30, 2021 photo, syringes and other medical equipment are shown during the media tour of their supervised drug injection site OnPoint, in New York. Operated by OnPoint NYC, a consortium of two nonprofit social welfare organizations, these centers are the first to be officially licensed in the United States. They offer opioid and other drug users a variety of services, including addiction treatment.
We have come too far to turn our backs on what works when it comes to sound, life-saving drug policies. Now is the wrong time to politicize practical, proven responses to this medical emergency.
We lost more than 80,000 Americans to overdose last year, making it the leading cause of death for adults aged 18 to 44. But, for the first time in years, we have some reason for hope: in 2024, overdose deaths dropped by 27 percent. That progress, however, didn’t happen on its own. It came from investments in harm reduction: an ecosystem of strategies including naloxone distribution, syringe service programs, medications for opioid use disorder, and housing-first programs that secured shelter for people before connecting them to care.
Unfortunately, much of that progress is in danger. In recent weeks, President Trump issued an executive order targeting the very programs that provide these services and helped bring down overdose deaths. In doing so, the administration is cutting federal funding for proven, evidence-based interventions. It is also carving out naloxone from the larger harm reduction ecosystem it belongs to, falsely suggesting that naloxone can succeed in isolation. The reality is that saving someone from an overdose requires more than just increasing naloxone’s availability. It requires a broader public health approach to reach those at risk. Without systemic support for trusted community-led networks, naloxone will not be able to reach the people who are most vulnerable.
I should know. I’ve spent the past 30 years working with people who use drugs—first addressing HIV in Central and Eastern Europe, and now as Director of Drug Policy at the Open Society Foundations, where we support harm reduction efforts globally. I’ve seen, time and again, that when we lead with evidence and compassion, we save lives.
The biggest barrier we consistently face isn’t science, but the stigma and misunderstandings associated with drug use.
Back in the 1990s, I worked on a program that supported harm reduction efforts in former Soviet countries, then the region with the highest rates of HIV among people who use drugs. The interventions were straightforward: provide sterile syringes, educate people about safe injections, and offer access to basic medical care. Whether in Tomsk, Russia, or my hometown in New Jersey, I never met a person who didn’t want to protect themselves. We were fortunate to have tools that people actually wanted. And they work. Syringe service programs cut HIV and hepatitis C infections in half. Other interventions, like methadone and buprenorphine, can lower HIV incidence by as much as 60 percent by helping people reduce or stop injecting altogether.
The biggest barrier we consistently face isn’t science, but the stigma and misunderstandings associated with drug use.
People mistakenly believe that providing sterile syringes encourages drug use or that drug treatment medications simply “replace one drug with another.” But by supporting and translating scientific research, educating medical professionals, and, perhaps most importantly, supporting people who use drugs, we’ve made great progress. These efforts have not only produced strong results but have also helped chip away at longstanding stigma.
Take, for example, the OnPoint NYC—the first overdose prevention center in the country. Since 2021, the center has reversed nearly 2,000 overdoses. Syringe exchange programs are now authorized in 37 states, the District of Columbia, and Puerto Rico. With bipartisan support, red states from Kentucky to Indiana to South Carolina are using opioid settlement funds to support critical harm reduction work. The reality that many have recognized is that harm reduction programs provide an important on-ramp to broader care. They engage people who often don’t go to traditional medical providers out of fear. People who visit syringe service programs are five times more likely to enter treatment than those who don’t. Harm reduction programs are an optimal venue for naloxone distribution since they directly reach people at risk of overdose. That’s why the Trump administration’s recent actions are so concerning. They reflect a shift away from science that has been working.
We have come too far to turn our backs on what works. We must not politicize practical, proven responses to this medical emergency. We live in a time where evidence-based public health interventions that had once been taken as givens have become political flashpoints. But we can’t let politics come in the way of saving very real lives. Too much is at stake now.
This country and this world are at a monumental crossroads. US voters have an opportunity to beat back the forces of fascism and confront the billionaires who are rigging the economy, our media system, and our democracy, making it increasingly impossible for ordinary people to get by. We’re not just talking about the election. We’re talking about what must be done once these fascist elements are vanquished from power. We need a bolder set of solutions than what either major party has so far been willing to offer and a working-class movement ready to fight like hell for it. Trump didn't emerge from nowhere. The conditions that fueled MAGA authoritarianism were created by decades of radical neoliberal economic policies and a corrupt political system dominated by corporate interests. They slashed taxes on the super-rich, promising that the benefits would trickle down. They said giveaways to the corporate titans would make life more affordable for the rest of us. It was all bullshit. And when a bitter, betrayed populace searches for someone to blame, right-wing demagogues have little trouble finding scapegoats. People know when they're being lied to, but you won't hear any of this from the corporate media. Only independent journalism—powered and funded by people who believe in building a better world—can deliver truly trustworthy daily news. If you share our vision, please contribute whatever you can to sustain our work. |
We lost more than 80,000 Americans to overdose last year, making it the leading cause of death for adults aged 18 to 44. But, for the first time in years, we have some reason for hope: in 2024, overdose deaths dropped by 27 percent. That progress, however, didn’t happen on its own. It came from investments in harm reduction: an ecosystem of strategies including naloxone distribution, syringe service programs, medications for opioid use disorder, and housing-first programs that secured shelter for people before connecting them to care.
Unfortunately, much of that progress is in danger. In recent weeks, President Trump issued an executive order targeting the very programs that provide these services and helped bring down overdose deaths. In doing so, the administration is cutting federal funding for proven, evidence-based interventions. It is also carving out naloxone from the larger harm reduction ecosystem it belongs to, falsely suggesting that naloxone can succeed in isolation. The reality is that saving someone from an overdose requires more than just increasing naloxone’s availability. It requires a broader public health approach to reach those at risk. Without systemic support for trusted community-led networks, naloxone will not be able to reach the people who are most vulnerable.
I should know. I’ve spent the past 30 years working with people who use drugs—first addressing HIV in Central and Eastern Europe, and now as Director of Drug Policy at the Open Society Foundations, where we support harm reduction efforts globally. I’ve seen, time and again, that when we lead with evidence and compassion, we save lives.
The biggest barrier we consistently face isn’t science, but the stigma and misunderstandings associated with drug use.
Back in the 1990s, I worked on a program that supported harm reduction efforts in former Soviet countries, then the region with the highest rates of HIV among people who use drugs. The interventions were straightforward: provide sterile syringes, educate people about safe injections, and offer access to basic medical care. Whether in Tomsk, Russia, or my hometown in New Jersey, I never met a person who didn’t want to protect themselves. We were fortunate to have tools that people actually wanted. And they work. Syringe service programs cut HIV and hepatitis C infections in half. Other interventions, like methadone and buprenorphine, can lower HIV incidence by as much as 60 percent by helping people reduce or stop injecting altogether.
The biggest barrier we consistently face isn’t science, but the stigma and misunderstandings associated with drug use.
People mistakenly believe that providing sterile syringes encourages drug use or that drug treatment medications simply “replace one drug with another.” But by supporting and translating scientific research, educating medical professionals, and, perhaps most importantly, supporting people who use drugs, we’ve made great progress. These efforts have not only produced strong results but have also helped chip away at longstanding stigma.
Take, for example, the OnPoint NYC—the first overdose prevention center in the country. Since 2021, the center has reversed nearly 2,000 overdoses. Syringe exchange programs are now authorized in 37 states, the District of Columbia, and Puerto Rico. With bipartisan support, red states from Kentucky to Indiana to South Carolina are using opioid settlement funds to support critical harm reduction work. The reality that many have recognized is that harm reduction programs provide an important on-ramp to broader care. They engage people who often don’t go to traditional medical providers out of fear. People who visit syringe service programs are five times more likely to enter treatment than those who don’t. Harm reduction programs are an optimal venue for naloxone distribution since they directly reach people at risk of overdose. That’s why the Trump administration’s recent actions are so concerning. They reflect a shift away from science that has been working.
We have come too far to turn our backs on what works. We must not politicize practical, proven responses to this medical emergency. We live in a time where evidence-based public health interventions that had once been taken as givens have become political flashpoints. But we can’t let politics come in the way of saving very real lives. Too much is at stake now.
We lost more than 80,000 Americans to overdose last year, making it the leading cause of death for adults aged 18 to 44. But, for the first time in years, we have some reason for hope: in 2024, overdose deaths dropped by 27 percent. That progress, however, didn’t happen on its own. It came from investments in harm reduction: an ecosystem of strategies including naloxone distribution, syringe service programs, medications for opioid use disorder, and housing-first programs that secured shelter for people before connecting them to care.
Unfortunately, much of that progress is in danger. In recent weeks, President Trump issued an executive order targeting the very programs that provide these services and helped bring down overdose deaths. In doing so, the administration is cutting federal funding for proven, evidence-based interventions. It is also carving out naloxone from the larger harm reduction ecosystem it belongs to, falsely suggesting that naloxone can succeed in isolation. The reality is that saving someone from an overdose requires more than just increasing naloxone’s availability. It requires a broader public health approach to reach those at risk. Without systemic support for trusted community-led networks, naloxone will not be able to reach the people who are most vulnerable.
I should know. I’ve spent the past 30 years working with people who use drugs—first addressing HIV in Central and Eastern Europe, and now as Director of Drug Policy at the Open Society Foundations, where we support harm reduction efforts globally. I’ve seen, time and again, that when we lead with evidence and compassion, we save lives.
The biggest barrier we consistently face isn’t science, but the stigma and misunderstandings associated with drug use.
Back in the 1990s, I worked on a program that supported harm reduction efforts in former Soviet countries, then the region with the highest rates of HIV among people who use drugs. The interventions were straightforward: provide sterile syringes, educate people about safe injections, and offer access to basic medical care. Whether in Tomsk, Russia, or my hometown in New Jersey, I never met a person who didn’t want to protect themselves. We were fortunate to have tools that people actually wanted. And they work. Syringe service programs cut HIV and hepatitis C infections in half. Other interventions, like methadone and buprenorphine, can lower HIV incidence by as much as 60 percent by helping people reduce or stop injecting altogether.
The biggest barrier we consistently face isn’t science, but the stigma and misunderstandings associated with drug use.
People mistakenly believe that providing sterile syringes encourages drug use or that drug treatment medications simply “replace one drug with another.” But by supporting and translating scientific research, educating medical professionals, and, perhaps most importantly, supporting people who use drugs, we’ve made great progress. These efforts have not only produced strong results but have also helped chip away at longstanding stigma.
Take, for example, the OnPoint NYC—the first overdose prevention center in the country. Since 2021, the center has reversed nearly 2,000 overdoses. Syringe exchange programs are now authorized in 37 states, the District of Columbia, and Puerto Rico. With bipartisan support, red states from Kentucky to Indiana to South Carolina are using opioid settlement funds to support critical harm reduction work. The reality that many have recognized is that harm reduction programs provide an important on-ramp to broader care. They engage people who often don’t go to traditional medical providers out of fear. People who visit syringe service programs are five times more likely to enter treatment than those who don’t. Harm reduction programs are an optimal venue for naloxone distribution since they directly reach people at risk of overdose. That’s why the Trump administration’s recent actions are so concerning. They reflect a shift away from science that has been working.
We have come too far to turn our backs on what works. We must not politicize practical, proven responses to this medical emergency. We live in a time where evidence-based public health interventions that had once been taken as givens have become political flashpoints. But we can’t let politics come in the way of saving very real lives. Too much is at stake now.

