

SUBSCRIBE TO OUR FREE NEWSLETTER
Daily news & progressive opinion—funded by the people, not the corporations—delivered straight to your inbox.
5
#000000
#FFFFFF
To donate by check, phone, or other method, see our More Ways to Give page.
Daily news & progressive opinion—funded by the people, not the corporations—delivered straight to your inbox.
"It will be patients who will pay the ultimate price," said one global health advocate.
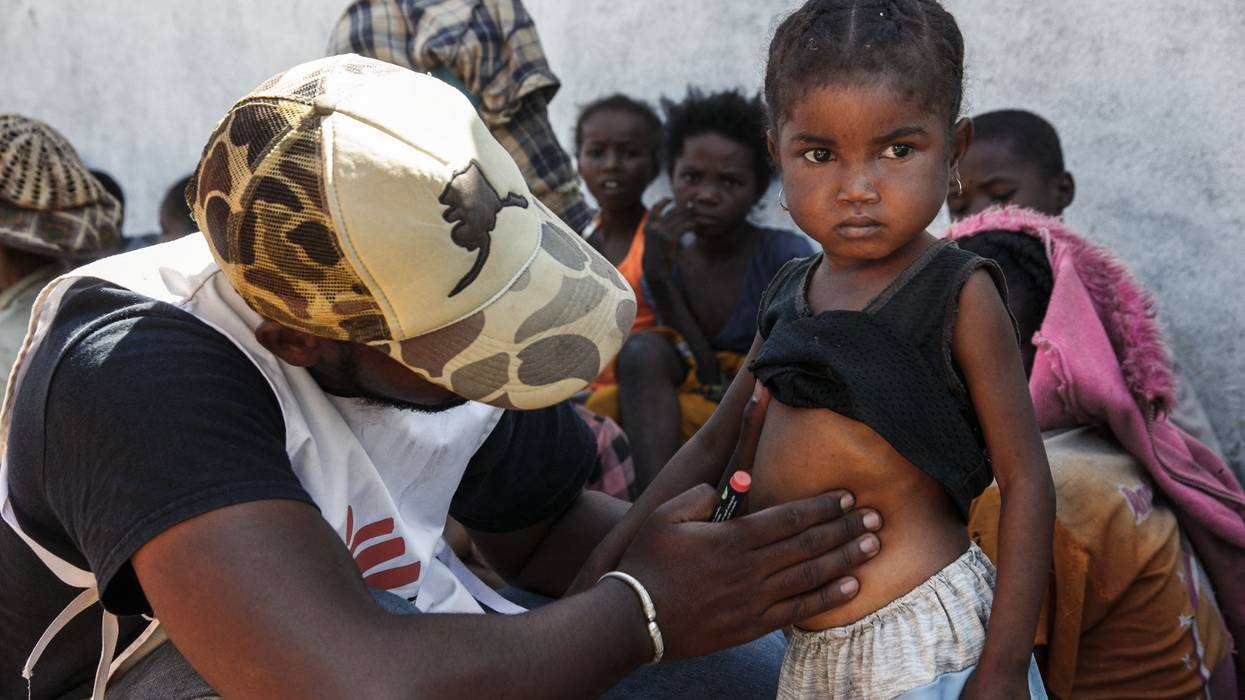
The US Congress has pushed back against President Donald Trump's efforts to slash foreign aid, which has long been supported by Democrats and Republicans alike—but a new report on more than a dozen Memoranda of Understanding that the White House has reached with countries that have long relied heavily on healthcare assistance shows that the administration is underspending "congressionally appropriated global health funds by potentially billions of dollars," as it pushes its "America First Global Health Strategy."
That's according to Public Citizen, which on Sunday joined Partners In Health in releasing an analysis of documents that the two nonprofits obtained after suing the Trump administration and filing a Freedom of Information Act (FOIA) request.
The groups reviewed the MOUs that have been signed for 18 out of 34 countries whose agreements have been negotiated by the US State Department, including Rwanda, Liberia, Burundi, and Madagascar.
Although Congress has voted to keep foreign aid levels relatively constant—rejecting a budget that called to slash global health spending by $6.2 billion before approving one that proposed a $615 million decrease in spending—the report finds that the MOUs cut foreign health aid by about $2 billion by 2030, compared to 2024 levels.
“These documents suggest that the Trump administration is on course to underspend on global health by billions of dollars compared to what Congress has ordered, risking lives and allowing diseases to spread,” said Peter Maybarduk, director of the Access to Medicines program at Public Citizen. “The administration must answer how and when it intends to invest the missing billions for health.”
Overall, funding for programs that aim to prevent the spread of diseases including HIV/AIDS, tuberculosis, and Ebola—which is currently spreading in the Democratic Republic of Congo's fastest-spreading outbreak on record—is set to be reduced by 59% from historical spending, according to the MOUs viewed by Public Citizen and Partners in Health.
Some countries would see their health assistance from the US plummet even more, with Rwanda's MOU stipulating a 97% reduction in US health aid. Liberia is set to receive 84% less funding for health initiatives by 2030, and Burundi is set to lose 78% of its aid.
"Partners In Health provides direct care in Rwanda, Liberia, and Sierra Leone, along with seven other countries, and expects under-spending of these funds to impact patients’ access to care," said Public Citizen.
The MOUs also demand that the countries meet strict co-financing requirements to make up for their lost funding, and governments in poor countries across Africa could face penalties "which could worsen funding cuts" if they miss the co-financing targets.
"The planned decreases in US funding are larger for several countries than the funding increases from partner governments," reads the report. "For more than half of countries (11 out of 18), co-financing commitments fall short of the US government’s cuts over five years compared to baseline US government funding."
Countries are likely to struggle to meet the co-financing requirements in the MOUs, warned Public Citizen and Partners In Health.
Malawi would be required to secure new healthcare funding equal to 56% of the country's total health expenditure, the report found. With Uganda also facing co-financing requirements from international health organizations including the Global Fund and Gavi, the East African country would be required to mobilize funds equal to 44% of its total health budget.
"These funding cuts will cause death and disease that is preventable,” said Vincent Lin, associate director of health policy and advocacy for Partners In Health. “The State Department is setting up other countries for failure with the co-financing requirements outlined in these agreements, but it will be patients who will pay the ultimate price.”
Maybarduk told The Washington Post that Sierra Leone will be required under its MOU to fill a 71% health funding gap by 2030.
“It’s going to be very difficult, and if a country like that falls behind, and then is punished for that, then of course the health problems compound," said Maybarduk.
The State Department denied to the Post that the Trump administration will not spend all the foreign health assistance funds appropriated by Congress; it suggested that more of the money than usual may go to religious organizations as well as an "innovation fund" to support US technology that aims to fight disease.
Last week, Public Citizen sued the Trump administration under FOIA to obtain the rest of the MOUs that remain hidden from the public.
The White House, said the group, "has kept the public in the dark about the full details of its plans for the future of US support for global health."
"The State Department has negotiated these bilateral agreements," the group said, "on rushed timelines with limited participation from civil society and affected communities."

"The people of the DRC deserve the world’s attention, resources, care, and solidarity," said one advocate.
As the Ebola crisis that was first detected in the Democratic Republic of Congo in May became the deadliest outbreak of the disease in the country's history on Monday, one global public health expert in the United Kingdom pointed to the key difference between the 2014 epidemic in West Africa and the one that has now killed at least 2,325 people in the DRC.
In 2014, wrote Devi Sridhar, chair of global public health at the University of Edinburgh, in The Guardian, the US and other wealthy countries "worked with the World Health Organization (WHO) to escalate a response, bringing military-like coordination, necessary resources, logistics, and trained personnel."
Now, said Sridhar, "we’ve had two 'America-First'" terms of President Donald Trump.
"The US is no longer part of the WHO or working multilaterally, favoring a 'go-it-alone' response," she wrote.
In Trump's second term, the president cut tens of billions of dollars in foreign aid spending. Data released by the Organization for Economic Cooperation and Development in April showed the US spent 56.9% less on foreign assistance last year after Trump dismantled the US Agency for International Development (USAID), cut smaller programs, and demanded that Congress rescind billions that had already been appropriated for countries and programs in need.
Ebola has become the DRC's worst-ever outbreak in just three months, wrote Sridhar, "in the context of the defunding of foreign aid, the censorship of scientists, the closure of USAID, the implosion of the Centers for Disease Control and Prevention, and a 'Make America Healthy Again' movement."
By the time officials announced that the outbreak had been detected in May, they had already recorded 246 suspected cases and 80 suspected deaths in Ituri province—suggesting that US aid and public health cuts had "undermined some of the surveillance and detection initiatives that might have helped to catch this earlier," as Jeremy Konyndyk of Refugees International said at the time.
Months after getting a significant head start in spreading throughout the population, Ebola has now been detected in six of the DRC's 26 provinces, and the country's public health institute has recorded at least 4,945 cases, with 101 detected in the 24 hours preceding Monday's announcement.
Ebola "is winning in the Democratic Republic of the Congo,” said the United Nations last Friday, noting that the epidemic was killing one person every 30 minutes.
Amnesty International called on the globa; community to urgently try to make up for the surveillance failures that happened earlier this year and mobilize to slow the outbreak.
"We call for global solidarity as eastern DRC faces its deadliest Ebola outbreak in the country's history," said Amnesty. "Human rights must continue to be prioritized as health workers treat the disease across the region."
The US State Department said earlier this month that it has provided $512 million in direct assistance to help respond to the outbreak—far less than the $5.4 billion the US enacted in December 2014 to fight the epidemic in West Africa.
US spending is lagging as the outbreak has become the fastest-growing in the history of the virus, as The Guardian reported Monday. The 2014 outbreak took five months to reach 1,000 deaths, but more than 2,000 people have died of Ebola in less than three months since the disease was detected.
Thomas Parisch, a public health specialist with Doctors Without Borders in the DRC, told The Guardian that the country still appears to be struggling with the limits imposed by aid cuts.
"Normally, as an outbreak progresses, the case fatality ratio should fall as contact tracing improves and patients are identified and treated earlier," said Parisch. "Instead, we’re still seeing many cases detected very late, when treatment is less likely to succeed, with many identified only after they die in the community.”
The outbreak also differs from previous epidemics in that the current Ebola infections are being caused by the rare Bundibugyo virus. There are no approved vaccines or treatments for the strain, but WHO Director-General Tedros Adhanom Ghebreyesus said recently that two new vaccines were being tested on people.
Lawyer and advocate Bernice King urged the public to "refuse to look away."
"Nonviolence is an active commitment to protect life," said King. "The people of the DRC deserve the world’s attention, resources, care, and solidarity."

"We need to massively step up our response," said one senior UN official, while another stressed that "Ebola feeds on delay, fear, and hunger."
As the official death toll from the Ebola epidemic in the Democratic Republic of Congo topped 1,500, United Nations officials called for a dramatic expansion of humanitarian assistance to combat what's now the fastest-spreading outbreak of the deadly disease ever recorded.
The DRC's Health Ministry on Friday confirmed more than 3,400 infections and at least 1,556 deaths since the outbreak was declared in May. The ministry said the fatality rate during the current epidemic is 44%.
The epidemic is caused by the rare Bundibugyo strain of the Ebola virus, which has spread across multiple DRC provinces, with the vast majority of cases concentrated in Ituri Province. Unlike the Zaire strain from previous outbreaks, there is currently no approved vaccine or treatment for the Bundibugyo virus.
The current epidemic has killed more people faster than any previous outbreak, including in 2014-16, when more than 28,000 infections and over 11,000 deaths were reported.
"In the last 24 hours, 50 people have died of Ebola in the Democratic Republic of the Congo and the number of cases is growing exponentially, doubling every 20 days,” senior United Nations aiEbola coordinator Julien Harneis said during a Wednesday press conference in New York.
“So, in support of the government, I'm calling that we step up, across the response, the United Nations, nongovernmental organizations, member states,” Harneis continued. "We need to massively step up our response, be it in terms of supplies, specialized supplies like personal protective equipment, staff, specialized medical staff, and logistics as well.”
Harneis spoke at the press conference with acting UN World Food Program Executive Director Carl Skau, who said that "Ebola feeds on delay, fear, and hunger."
“Stopping this outbreak requires all hands on deck and communities at the center," he continued. "Food assistance is frontline Ebola containment. It helps families stay home, supports safe isolation, builds trust with communities, and keeps health teams moving. We know what works; what we need now is the speed and resources to scale it before this outbreak outruns the response.”
Skau noted that around 10 million people are suffering from acute food insecurity in the eastern DRC, with 3 million of those in an Integrated Food Security Phase Classification (IPC)-designated "emergency"—one step away from famine.
“You cannot force people to choose between hunger and health,” he said.
Compounding the crisis, a growing number of Ebola patients are dying outside of treatment centers. Officials said that more than 60% of recent Ebola deaths have occurred in communities, increasing the risk of further transmission through unsafe caregiving and burial practices.
Health workers also continue to endure attacks by armed groups, which have forced aid organizations to suspend operations in some of the hardest-hit areas of the epidemic.
Some experts also pointed to US President Donald Trump’s ideologically driven decision to withdraw the US from the World Health Organization, his administration’s dismantling of the US Agency for International Development, and reduced funding for the US Centers for Disease Control and Prevention’s global public health efforts as adversely affecting the response to the current Ebola epidemic, especially when compared with outbreaks in 2014 and 2019.
Meanwhile, health officials in neighboring Uganda this week declared an end to the country's Bundibugyo outbreak after no new cases were reported for a month. Twenty people were infected, and three died, in Uganda.

"This is what happens when the US Department of State fires career experts and tries to have AI conduct diplomacy."
"AI use gone wrong." "Utter embarrassment." "Stupid empire." "Idiot Reich."
Those were just some of the responses to Thursday reporting on a US Department of State map presented at a global conference in Brazil that mislabeled every African country it included.
"Reuters viewed a video of the presentation given at the AIDS 2026 conference in Rio de Janeiro, which shows the errant map displayed halfway during a presentation about the State Department's new health agreements," the news agency reported.
"A Reuters analysis found the image of the map included in the presentation contained an artificial intelligence watermark that signals it was made with OpenAI tools," the outlet noted. "The company said it was investigating the report."
While Jeff Graham, who oversees the President's Emergency Plan for AIDS Relief (PEPFAR) and was speaking at the conference, did not respond to Reuters' requests for comment, the State Department said that "we take full responsibility for the confusion and misrepresentation it caused for attendees, including our African partners."
Critics around the world, including Democrats in Congress, blasted the department under Secretary of State Marco Rubio and President Donald Trump, who have reduced staff by 3,000 between layoffs and voluntary departures.
A recent Financial Times article headlined "RIP the US State Department" noted that "as of late June more than half of American ambassadorships were vacant, including high-status posts from Germany to Saudi Arabia," and nearly 80% of American embassies across Africa lack an ambassador.
Sharing the Reuters reporting on social media Thursday, Nick Cleveland-Stout, a research associate in the Democratizing Foreign Policy program at the Quincy Institute for Responsible Statecraft, commented, "Checking in on the whole defund the State Department thing."
Former US Ambassador to Jamaica Luis Moreno said that "this is the pathetic result when you fire career, nonpartisan diplomatic personnel and replace them with unqualified partisan hacks who rely on faulty AI."
US Senate Foreign Relations Committee Ranking Member Jeanne Shaheen (D-NH) declared: "What an embarrassment. This is what happens when the US Department of State fires career experts and tries to have AI conduct diplomacy."
Congressman Jonathan Jackson (D-Ill.) stressed that "Trump's Department of State showed up to a global conference with an AI-generated map that mislabeled nations across Africa. Every. Single. One. This isn't just an embarrassing mistake."
"It's a symbol of an administration that has treated a continent of 1.5 billion people as an afterthought while China is deepening engagement across the African continent," he argued. "That's what happens when you hollow out expertise and stop taking diplomacy seriously. Our African partners and the American people deserve better."

“Trump is exploiting African states’ urgent need to restore lifesaving health aid," said one campaigner.
US Department of State text messages detailing health agreements between the Trump administration and African nations have sparked fresh alarm among public health advocates, who warn that the coercive deals could allow the United States to secure access to virus samples and valuable data while failing to guarantee that countries providing them will receive vaccines, treatments, and other benefits in return.
Public Citizen said Thursday that it had analyzed documents concerning the Trump administration's terms for sharing pathogen data in health agreements with African nations. The consumer advocacy group described these terms as "unfair" and said that they threaten "to undermine the core equity bargain of the [World Health Organization's] Pandemic Agreement negotiations."
The conditions of the proposed deals, said Public Citizen, "would require African states to share viral samples and pathogen information with the US and allow the US to share that information with drugmakers, but provide no credible expectation of benefits in return or access to medical tools developed from those samples."
"This undercuts the federated proposal for viral sharing with access benefits put forward this month at WHO negotiations by the Africa+ Group, which includes all countries for which bilateral specimen agreements are available," Public Citizen added.
At the center of the controversy are agreements that tie US health assistance—which has been eviscerated by the Trump administration with widespread deadly consequences—to commitments involving disease surveillance, data sharing, and, in some cases, the exchange of pathogen samples.
Supporters argue the deals strengthen America's ability to detect and respond to emerging infectious diseases while providing partner countries with much-needed funding after devastating cuts to US aid. Public health advocates, however, contend the agreements shift power away from multilateral institutions and toward one-on-one negotiations in which lower-income countries have less leverage against the world's wealthiest and most powerful nation.
As Common Dreams reported last month, President Donald Trump's so-called “America First” approach to global health strategy is characterized by transactional agreements with African governments to restore some funding. Human rights advocates have raised concerns about the possibly coercive nature of this strategy.
“Trump is exploiting African states’ urgent need to restore lifesaving health aid and pushing them to give up a shot at real lifesaving medical access and equity, for which so many people have worked, bled, and died,” Peter Maybarduk, director of Public Citizen's Access to Medicines program, said Thursday in a statement. "African states at WHO have led the way in efforts to secure a fair deal and cooperation to fight pandemics, but individually, these states are vulnerable to Trump’s threats.”

One critic noted that Sahrawis "are beaten, arbitrarily arrested, and have their equipment confiscated for trying to make their own films of life under occupation."
Sahrawi activists and filmmakers are leading renewed calls to boycott the big-screen adaptation of Homer's ancient Greek epic The Odyssey over filmmaker Christopher Nolan's decision to shoot the film in the Western Sahara, whose people have suffered Moroccan occupation for over half a century.
"It is deeply disturbing that while Sahrawi journalists are imprisoned for exposing abuses, an international film production can use our homeland as a cinematic backdrop without addressing the reality of the occupation," Sahrawi journalist and filmmaker Mamine Hachimi told Middle East Eye (MEE) in an interview published on Wednesday.
Hachimi, who co-directed the short documentary Three Stolen Cameras about the oppression of people who document human rights crimes committed by Moroccan occupiers, told MEE's Alex MacDonald that calls to boycott The Odyssey—which was filmed in the Western Saharan city of Dakhla and opens on Friday—"is not a campaign against cinema or artistic freedom, it is a call for ethical responsibility."
"Two of my colleagues, Abdallah Lhafaouni, who is serving a life sentence, and Bachir Khadda, who is serving a 20-year sentence, are political prisoners simply because they documented human rights violations in occupied Western Sahara," Hachimi said.
Another Sahrawi filmmaker, Mohamedsalem Werad, told MEE that "choosing to film in occupied Western Sahara was not a politically neutral production decision—it meant operating with the permission of the occupying power in a territory where the Sahrawi people have long been denied the opportunity to exercise their right to self-determination."
"A boycott sends a clear message that filmmakers cannot expect audiences to overlook decisions that risk legitimizing an occupation," he added.
Sarah Yerkes, a senior fellow in the Middle East Program at the Carnegie Endowment for International Peace, wrote last week that The Odyssey "has a colonialism problem."
"For Morocco, the territories that make up Western Sahara are referred to as the 'southern provinces' and are an indisputable part of the kingdom," Yerkes noted. "But... Dakhla is part of what is considered the occupied and non-self-governing Western Sahara under existing international law."
"The Sahrawi people, who are indigenous to the region and currently have no meaningful self-determination, have not consented to the film’s production—and the Moroccan government is reaping the rewards at their expense," she added.
The renewed calls to boycott The Odyssey follow last year's appeal, led by the Western Sahara International Film Festival and signed by hundreds of artists, journalists, activists, and other human rights defenders, urging Nolan, Universal Pictures, and producers of the film "to break their silence and cease to be accomplices to Morocco’s 50-year illegal occupation."
The government of the Sahrawi Arab Democratic Republic, which claims sovereignty over Western Sahara but is not recognized by the United Nations, has also condemned what it called "an attempt to film a cinematic work in occupied Dakhla, considering it a violation of international legitimacy and the ethics of cultural and artistic work."
Morocco has occupied Western Sahara since 1975, when Spanish forces withdrew from their former colony in the dying days of longtime dictator Francisco Franco's regime. Moroccan warplanes bombed Sahrawis, many of whom fled into neighboring Algeria as the government under King Hassan II orchestrated a “Green March” of hundreds of thousands of Moroccan civilians into the phosphate- and fishery-rich territory.
Western Sahara is today known among locals and human rights advocates as “Africa’s last colony.” Moroccan forces have brutally oppressed the Sahrawi people under their rule, severely restricting freedom of expression, movement, association, and the press, and utilizing arbitrary arrest and torture as tools of repression, according to human rights groups.
Moroccan occupation forces also built a 1,700-mile mostly sand wall to keep Algerian-backed Sahrawi militants led by the Polisario Front out of the territory, while denying people inside their occupied homeland a United Nations-backed referendum they’ve been awaiting for decades.
During his first term, US President Donald Trump recognized Moroccan sovereignty over Western Sahara, essentially in exchange for Morocco’s decision to normalize relations with Israel under the Abraham Accords.

“It’s hard to fathom how deeply evil this is,” said Sen. Chris Murphy.
The US government advises Americans not to travel to the Central African Republic "for any reason." But it just deported nearly two dozen people to the war-torn country, including several refugees who fled persecution in other nations.
On Friday morning, Human Rights First's deportation flight tracker reported that a plane used by Immigration and Customs Enforcement (ICE) had landed in Accra, Ghana, after departing from Louisiana the previous day and was believed to be en route to the CAR's capital, Bangui.
Per The New York Times on Thursday, the administration was preparing to deport "at least two Iranian women who had sought refuge in the United States" as well as "migrants from Afghanistan and Syria."
According to their lawyers, several of the migrants had received court orders from judges prohibiting their deportation to their home countries, citing the risk of persecution there.
A lawyer for one of the Iranian women told the Times that neither of them has a criminal record and that they both have been granted court protection due to fear of threats to their freedom or lives if they returned to Iran. One is a Christian convert, and the other is a pro-democracy activist.
According to Reuters, just the activist ended up on the flight from Louisiana. But the Christian woman is still at risk, along with another Iranian national.
Human Rights First's @ICEFlightM is monitoring this egregious situation, and we urge our policy makers to decry this life-threatening flight and other deals that send people seeking safety back to the very harms from which they fled.
https://t.co/ABZZMTQNuS
— Human Rights First (@humanrights1st) June 11, 2026
The burden of proof to receive what is known as a “withholding of removal” status from an immigration judge is even higher than that needed for migrants to qualify for asylum.
Those seeking their deportations to be halted must demonstrate that it’s more likely than not that their life or freedom would be threatened if they returned to a specific country due to their race, religion, nationality, or political or social affiliation.
In order to get around orders protecting these migrants from deportation to their home countries, the administration is instead dumping them in what have been described as "third countries."
The flight departed on Thursday is the first US deportation flight to the CAR, which is one of the poorest countries in the world and is reeling from a civil war that's displaced more than a million people both inside and outside the country.
The country is under the State Department's highest travel advisory, warning US citizens not to go there "due to risk of unrest, crime, kidnapping, landmines, health, and terrorism."
This is the @StateDept travel advisory for the Central African Republic.
The United States—a self-proclaimed nation of refuge—is about to send refugees here. https://t.co/uxfexS5S73 pic.twitter.com/pvYyxIQHdN
— Sarah Pierce (@SarahPierceEsq) June 11, 2026
"People on this flight proved to a judge that they were likely to be persecuted in their home countries," said Aaron Reichlin-Melnick, a senior fellow at the American Immigration Council. "This is profoundly unjust."
Human rights law experts Anjli Parrin and Savi Arvey wrote on Wednesday for Just Security that the administration was putting "lives at risk" by sending these migrants to a dangerous country where they know nobody and where basic healthcare infrastructure hardly exists.
They said the administration's deportation of these migrants "is the latest example of its dangerous and potentially life-threatening strategy: using secretive deals with countries to expel asylum seekers and migrants with no legal or personal connection to the places where they are being sent."
"Since early last year, the US government has signed a growing number of third-country forced transfer agreements with over 30 countries worldwide to expel and deport people to places where they have no legal or personal ties," they said.
"These deportations are often carried out in secrecy and without any semblance of due process," they added. "Individuals are often not given any advance warning or the opportunity to challenge their deportation to a third country—with many only discovering they are being sent to a country they may have never heard of while airborne."
Emily Trostle, a lawyer for the Iranian activist, told Reuters that the migrants facing deportation to the CAR "have absolutely no connection to this place."
“These individuals are being removed from the United States and abandoned in a country where they have no status, no connection, and no support network,” she said. “We fear they will ultimately be forced to return to the countries they originally fled.”
According to Human Rights First's Third Country Deportation Watch, governments around the world have been given $44 million from US taxpayers to receive these migrants. More than 19,000 people, it found, have been deported across 24 countries.
Most of them have been sent to Mexico, but the US has also shipped migrants to some of the poorest, most unstable nations in sub-Saharan Africa, including Eswatini, Equatorial Guinea, and Sierra Leone. Many have faced arbitrary detention and torture or been returned to the country where they fled persecution.
In order to avoid having to allow over 1,000 Afghans who fought alongside US soldiers to settle as refugees in the US as planned, the Trump administration is reportedly trying to ink a deal with the Democratic Republic of the Congo to take them instead, but the plan was stalled amid public backlash, and the administration is seeking other options.
It's hard to fathom how deeply evil this is, and that we have people running our country who get sick pleasure from sending women fleeing violence in Iran to an African country in the middle of a brutal civil war. https://t.co/JaN8z2LFI2
— Chris Murphy 🟧 (@ChrisMurphyCT) June 11, 2026
The Iranian American Legal Defense Fund said on Thursday that the deportation of Iranian nationals was a “potentially fatal action,” as they could face danger in the CAR or be sent back to Iran.
Another person scheduled to be deported to the CAR was an elderly man from Syria, whose immigration attorney, Margaret Stock, told the Times that he had scars all over his body due to torture in his home country.
He is a Sufi Muslim and feared persecution if he returned there, and is in danger of lacking access to care for his diabetes if sent to the CAR. According to Stock, he received an emergency temporary order halting his deportation.
Sen. Chris Murphy (Conn.), the ranking Democrat on the subcommittee in charge of funding for the Department of Homeland Security and its immigration agencies, responded to the Times report on the deportations with outrage.
"It's hard to fathom how deeply evil this is, and that we have people running our country who get sick pleasure from sending women fleeing violence in Iran to an African country in the middle of a brutal civil war," he said.
Reichlin-Melnick agreed: "Evil is the right word for... taking people who are safe in the United States, who have proven to a judge they would be persecuted in their home country, and dumping them in a random country in the middle of a civil war."
"No previous administration would have done this, despite it likely being legal," he added.
“After the sudden and devastating pullback from US assistance in 2025, governments are now being pressured to accept agreements with contingencies that jeopardize human rights."
The Trump administration is requiring African nations to agree to a series of "troubling conditions" to restore lifesaving health aid, according to a Human Rights Watch report on Monday.
The administration's abrupt shuttering of the US Agency for International Development (USAID) last year shut off billions of dollars and caused havoc across Africa's healthcare system, resulting in what public health models project could be hundreds of thousands of preventable deaths.
But under what has been dubbed the “America First” Global Health Strategy, the administration has negotiated secretive agreements with dozens of these countries to restore some of the funding. Most of them have been kept under lock and key by the US.
Those that have been made public have come with terms that Human Rights Watch said "raise concerns that health aid is being inappropriately leveraged to extract terms beneficial to the US in negotiations around natural resources and access to sensitive health data from recipient countries."
In March, a draft memorandum of understanding with the government of Zambia was revealed to have conditioned $1 billion for HIV, tuberculosis, malaria, and other disease prevention for millions of people, on the country's acceptance of a separate bilateral treaty that would have given US companies greater access to the country's minerals.
A leaked State Department memo, prepared for Secretary Marco Rubio, put the exploitative terms plainly: “We will only secure our priorities by demonstrating willingness to publicly take support away from Zambia on a massive scale.”
After the details of that agreement were met with backlash, the text of agreements with several other countries—Ethiopia, Kenya, Mozambique, Nigeria, and Uganda—were suddenly removed from the State Department’s Freedom of Information Act Library.
A Human Rights Watch assessment of the agreements with those five countries—as well as agreements with Rwanda and Liberia that were leaked—revealed that in order to restore a portion of the more than $800 million collectively stripped from them by the US, they'd have to agree to several coercive measures that jeopardize the reproductive and privacy rights of their citizens.
“The agreements show the US intends to condition vital health assistance for millions of people on acquiescence to troubling conditions,” said Julia Bleckner, senior health researcher at Human Rights Watch. “After the sudden and devastating pullback from US assistance in 2025, governments are now being pressured to accept agreements with contingencies that jeopardize human rights.”
All seven of the agreements require the governments to provide the US with "broad access to data and information" to monitor compliance with the Helms Amendment, which forbids the use of US foreign assistance to pay for abortion care.
The agreements with Mozambique, Rwanda, and Liberia require them to provide “any data” requested by the US to ensure compliance with the amendment, while Uganda's permits the US to conduct unannounced spot checks of health facilities and clinics.
"By making a broad package of health aid contingent on broad and potentially invasive surveillance of Helms compliance, the agreement could encourage a more restrictive regulation of abortion than national law mandates and give rise to further violations of the right to healthcare,” says the report.
The agreements also give the US permission to directly audit clinics, laboratories, and health programs to ensure compliance with the conditions. Six of them require clinics to provide access to "any data" requested by the US at a sample of facilities it chooses.
Agreements with five countries also mandate that they share biological specimens taken from patients and associated information related to novel infectious diseases, which HRW described as part of an effort to undermine a global pathogen access and sharing system being created by the World Health Organization, from which Trump has removed the US.
HRW said in a news release:
The agreements raise serious concerns about use of people’s private health data, without clear limits, uniform safeguards, or meaningful protections for patient confidentiality, including in several countries with weak or absent domestic data protection laws. The agreements contain no prohibition on this data being shared with US pharmaceutical companies without patient consent.
“Governments negotiating health assistance agreements with the United States face difficult choices,” Bleckner said. “They should be wary of terms asking them to sign away their populations’ rights and push for the inclusion of civil society representatives and multilateral global health organizations like the Global Fund in deliberations.”
"Unsure how any US citizen would feel comfortable deploying" to help fight the outbreak, said one doctor, "knowing our government would not make sure they are okay if something happened."
The United Nations' emergency relief office on Thursday was mobilizing $60 million to fight the rapidly spreading Ebola outbreak in the Democratic Republic of Congo, with the body's under-secretary-general for humanitarian affairs saying relief teams are "fully mobilized" and "applying lessons from previous outbreaks," with a focus on building community trust and communicating with governments.
But with the Trump administration having dismantled the US Agency for International Development (USAID) and slashed funding and staffing for the Center for Disease Control and Prevention's (CDC) global efforts, the response is largely missing a key feature that helped with containment during the 2014 and 2019 outbreaks—the involvement of the US government and public health teams—and Secretary of State Marco Rubio signaled on Thursday that was unlikely to change.
In comments to the press, Rubio said the Trump administration's top priority is that Ebola doesn't reach the US—even if that means imposing travel restrictions against the guidance of the World Health Organization (WHO)—and described an approach that one disaster relief leader said was antithetical to the actions the US took in previous Ebola outbreaks.
"Our number-one objective on Ebola, before anything else, and we think it's terrible what's happening there to the people... Our number-one thing has to be, we can't have it affect the United States," said Rubio. "We can't have Ebola cases coming here."
Rubio: "We can't have ebola cases here. In fact, I think we had a flight last night headed to Detroit that was diverted." pic.twitter.com/S84FmWIq5b
— Aaron Rupar (@atrupar) May 21, 2026
The secretary of state noted that an Air France flight that had been headed for Detroit was diverted to Montreal on Wednesday after a passenger from Congo was found to have boarded the plane "in error."
The Department of Homeland Security announced new restrictions this week saying that all travelers who have been in the DRC, Uganda, and South Sudan in the past 21 days—including US citizens and permanent residents—can only enter the US through Washington Dulles International Airport.
When WHO declared the Ebola outbreak a public emergency of international concern last weekend, the agency noted that "no country should close its borders or place any restrictions on travel and trade."
"Such measures are usually implemented out of fear and have no basis in science," said WHO in its guidance, which also noted "state parties should be prepared to facilitate the evacuation and repatriation of nationals (e.g. health workers) who have been exposed" to Ebola.
Jeremy Konyndyk, president of Refugees International and a former USAID disaster relief official, said the message sent by Rubio was "insanely counterproductive."
By sending the message that the US is prioritizing that Ebola stays outside US borders above all, said Konyndyk, the Trump administration is telling "any US health workers that if they get infected trying to contain the outbreak, they won't be allowed home."
"In the 2014 outbreak we did the opposite, because we knew that posture would undermine the response and extend the outbreak," he said.
Dr. Krutika Kuppalli, who specializes in infectious diseases and deployed to West Africa in 2014 to help fight the Ebola outbreak that killed more than 11,000 people, said she did so "with the understanding that if something happened my government would take care of me."
"Unsure how any US citizen would feel comfortable deploying, knowing our government would not make sure they are okay if something happened," said Kuppalli.
The Trump administration's refusal to directly help US healthcare workers impacted by the outbreak has already resulted in two doctors being sent to European countries including Germany and the Czech Republic for treatment.
As he emphasized that Ebola cannot reach US shores, Rubio sent out messages of thanks to German and Czech officials for admitting the two medical workers to their hospitals.
With more than 170 deaths and about 750 infections suspected in the "rapidly" spreading Ebola outbreak and cases reported in Uganda as well as the DRC, public health experts are warning that the crisis is likely to "get worse before it gets better" and that its impact has likely already reached farther than initial numbers show due to a lack of surveillance on the ground.
Former CDC Director Robert Redfield told NewsNation on Thursday that "normally when we have these Ebola outbreaks, and I had three of them when I was CDC director, all of which were in the DRC, normally we recognize them when we have five, 10 cases, you know, at most."
"This one really wasn’t picked up until there was over 100 cases," he said.
WHO Director General Tedros Adhanom Ghebreyesus said Friday that the risk assessment for Ebola is "very high at the national level, high at the regional level and low at the global level."
As Common Dreams reported earlier this week, experts have pointed to President Donald Trump's cuts to foreign assistance and public health initiatives as reasons the outbreak had already spread as far as it did when the emergency was declared this week.
The State Department announced on Monday it was mobilizing $13 million in assistance to help contain the outbreak; the US spent more than $5 billion to fight to 2014 epidemic that hit several countries in West Africa.
"The United States cannot quickly reverse our abdication of leadership on the global health stage," wrote Dr. Craig Spencer, an emergency medicine physician who helped treat Ebola patients in 2014 and survived the disease himself. "But we can bolster our response to this crisis. There should be a steadfast commitment to working closely and coordinating with essential partners like the WHO. We need to mobilize funding and experts, speed up the development of new treatments, and increase resources for protective equipment and expanded testing."

"Before the second Trump administration, USAID would have been on the ground," said one public health expert.
The World Health Organization's official designation of an Ebola virus outbreak in the Democratic Republic of Congo and Uganda as a public health emergency of international concern on Sunday came just a day after the world learned that the disease was spreading at all—a highly unusual chain of events, public health experts said, and one that suggested the virus has been circulating for weeks without the outbreak being detected.
WHO Director-General Tedros Adhanom Ghebreyesus said Sunday that eight laboratory-confirmed cases, 246 suspected cases, and 80 suspected deaths had been reported in at least three health zones across Ituri Province in the DRC. In Kampala, the densely populated capital of neighboring Uganda, two lab-confirmed cases and one death were reported within 24 hours of each other.
The victims in Kampala had no apparent link to one another; both had recently traveled from Congo.
The confirmed cases in Congo include some that have been reported in Kinshasa, the capital. The fact that the disease has been able to spread to two large cities with international airports, and the "clusters of deaths across the province of Ituri" point to "a potentially much larger outbreak than what is currently being detected and reported, with significant local and regional risk of spread," said WHO.
"At least four deaths among healthcare workers in a clinical context suggestive of viral haemorrhagic fever have been reported from the affected area, raising concerns regarding healthcare-associated transmission, gaps in infection prevention and control measures, and the potential for amplification within health facilities," the agency said.
Dr. Ashish Jha, who served as the White House Covid-19 response coordinator, said the numbers being reported could make the outbreak "one of the 10 biggest Ebola outbreaks in history."
"We're just hearing about this now? That makes no sense. Those numbers take weeks to accumulate," said Jha, adding that the fact that suspected cases have been detected in capital cities as well as Bunia, the provincial capital of Ituri, "matters enormously for spread."
Tedros emphasized that the outbreak is considered "extraordinary" because there is no approved vaccine or therapeutics for Ebola caused by the Bundibugyo virus, as this strain is. WHO sent a team to investigate in Ituri after first being notified of suspected Ebola cases on May 5, but initial samples tested negative, as available field equipment was only able to detect the Zaire strain of the disease.
The US Centers for Disease Control and Prevention (CDC) and global partners "need to surge resources in," Jha said. "A slow response creates unnecessary risks to people everywhere."
WHO, which President Donald Trump withdrew the US from last year, said the public health emergency designation was made to ramp up surveillance and infection prevention in the countries where the outbreak is occurring, enhance preparedness in bordering countries, and spread awareness in the international community.
The Ebola outbreak is the second to hit Uganda since Trump slashed foreign assistance funding, including by dismantling the US Agency for International Development. Earlier this month, CNN reported that the administration plans to divert $2 billion in global health program funding to cover the cost of closing USAID.
US foreign spending dropped by 56.9% after Trump shut down the agency as well as smaller aid programs and pushed Congress to rescind previously approved foreign assistance. USAID played a critical role in responding to the 2014 Ebola outbreak in West Africa.
In March 2025, when an Ebola outbreak was reported in Uganda, US officials warned that Trump's actions on foreign assistance at that point, including the termination of USAID grants, was impeding the Ugandan government's ability to procure lab supplies, diagnostic equipment, and protective gear for medical workers.
Dr. Herbert Luswata, president of the Uganda Medical Association, told The New York Times at the time that the country's ability to respond to Ebola was notably different than it had been during a previous outbreak in 2022, when dozens of medical workers volunteered to help treat patients.
The lack of funds and protective equipment had "left many afraid to help this time," the Times reported.
“With no USAID money and CDC expertise, it was like Uganda was left to die," Luswata told the Times.
Dr. Craig Spencer, an emergency medicine physician who survived Ebola in 2014, told CBS Saturday that "before the second Trump administration, USAID would have been on the ground" to respond to the current outbreak.
"The CDC would have been on the ground at a moment's notice, maybe even before a moment's notice, of a new outbreak of Ebola because we were in a bunch of countries," said Spencer. "We created relationships beforehand."
Last year, Trump megadonor Elon Musk, who was then leading efforts to slash government spending at the Department of Government Efficiency, said DOGE had "accidentally" canceled US support for Ebola prevention but claimed the funding had been "restored...and there was no interruption.”
But a number of Ebola-related contracts were in fact cut, accounting for $1.6 million out of $2.2 million that had previously gone toward the prevention efforts.
In recent weeks, public health experts have also warned that Trump's cuts to the CDC and other public health programs have left the US ill-prepared to respond to the hantavirus outbreak that originated on a cruise ship.
Jeremy Konyndyk, president of Refugees International and former leader on USAID's Covid-19 and disaster relief response work, said the current Ebola outbreak is "very worrying" and appeared to be the result of a "massive surveillance failure."
"It is really unusual for an Ebola outbreak to get to this scale before being detected; particularly in DRC, which has a lot of Ebola experience," said Konyndyk.
"I can't help but wonder," said Konyndyk, "if the drawdown of USAID and CDC health interventions by DOGE undermined some of the surveillance and detection initiatives that might have helped to catch this earlier."
WHO emphasized that the current crisis in DRC and Uganda requires "international coordination and cooperation to understand the extent of the outbreak, to coordinate surveillance, prevention, and response efforts, to scale up and strengthen operations and ensure ability to implement control measures."