

SUBSCRIBE TO OUR FREE NEWSLETTER
Daily news & progressive opinion—funded by the people, not the corporations—delivered straight to your inbox.
5
#000000
#FFFFFF
To donate by check, phone, or other method, see our More Ways to Give page.
Daily news & progressive opinion—funded by the people, not the corporations—delivered straight to your inbox.

Public health advocates on Wednesday applauded an African nurse who came up with a novel way to protest pharmaceutical industry profiteering during the Covid-19 pandemic--by sardonically clapping for Big Pharma executives attending the World Economic Forum annual meeting in Davos, Switzerland.
"If I wanted to earn what Pfizer CEO Albert Bourla made last year, I would have to work every single day until 6100 A.D."
George Poe Williams, a frontline nurse from Liberia, launched his "Clap for Pharma Profits" protest as pharmaceutical corporations reap $1,000 per second in profits while price gouging and blocking patent waivers as the world's poorest countries remain largely unvaccinated against a virus that's killed more than 6.2 million people.
"This forum is clearly made to represent the interests of the financial elite," Williams said of the Davos gathering, "not the interests of us workers who actually make the world economy work."
"If I wanted to earn what Pfizer CEO Albert Bourla made last year, I would have to work every single day until 6100 A.D.," he added. "But what makes me really furious is that Bourla and many of his billionaire buddies here at WEF are doing all they can to block our demands for a patent waiver--just so they can make even more money."
Williams' clapping protest--during which he says he was harassed by police--drew applause from public health, trade justice, and other campaigners.
"While Pfizer CEO Bourla is pondering how to morally get away with $24 million in pay/year, frontline worker and nurse George Poe Williams is calling out pharma's role in blocking access to lifesaving tools by not waiving patents," tweeted Medecins Sans Frontieres Access international campaign manager Lara Dovifat.
In Liberia, only about 28% of the population is fully vaccinated, according to the Johns Hopkins Coronavirus Resource Center. In at least 17 countries, less than 10% of people have been fully inoculated against the coronavirus. In Haiti, the figure is just over 1%. In Burundi, it's one-tenth of 1%.
Liberia is one of more than 100 countries that support a World Trade Organization (WTO) Trade-Related Aspects of Intellectual Property Rights (TRIPS) Agreement waiver, an Indian and South African proposal aimed at tackling vaccine inequity that would suspend coronavirus-related patents for the duration of the pandemic. The pharmaceutical industry and most wealthy nations oppose the proposal, with exceptions including the United States and France.
Meanwhile, tax-dodging pharmaceutical companies have raked in over $34 billion in profits during the pandemic, thanks largely to vaccine monopolies, even as more than 90% of vaccine research and investment came from public funding.
"These blocking governments are putting the interests of pharma corporations ahead of the lives of billions across the Global South," Williams asserted. "Vaccine production continues to be restricted by patents. In Liberia, only a third of us are vaccinated. If they don't act now, they will have blood on their hands."
"Me and my frontline colleagues saw pain, misery, death. Bourla and the other pharma executives here in Davos saw a chance to pump up profits," he added ."I'm not waiting for them to have a moral epiphany--I'm asking that the few remaining governments stop blocking this waiver and start putting our lives ahead of pharma profits."

Underscoring the desperate need to dramatically increase equitable access to coronavirus vaccines on a global scale, Africa just saw its worst pandemic week yet and conditions across the continent are only expected to get worse in the weeks ahead.
"The worst is yet to come as the fast-moving third wave continues to gain speed and new ground."
--Dr. Matshidiso Moeti, WHO
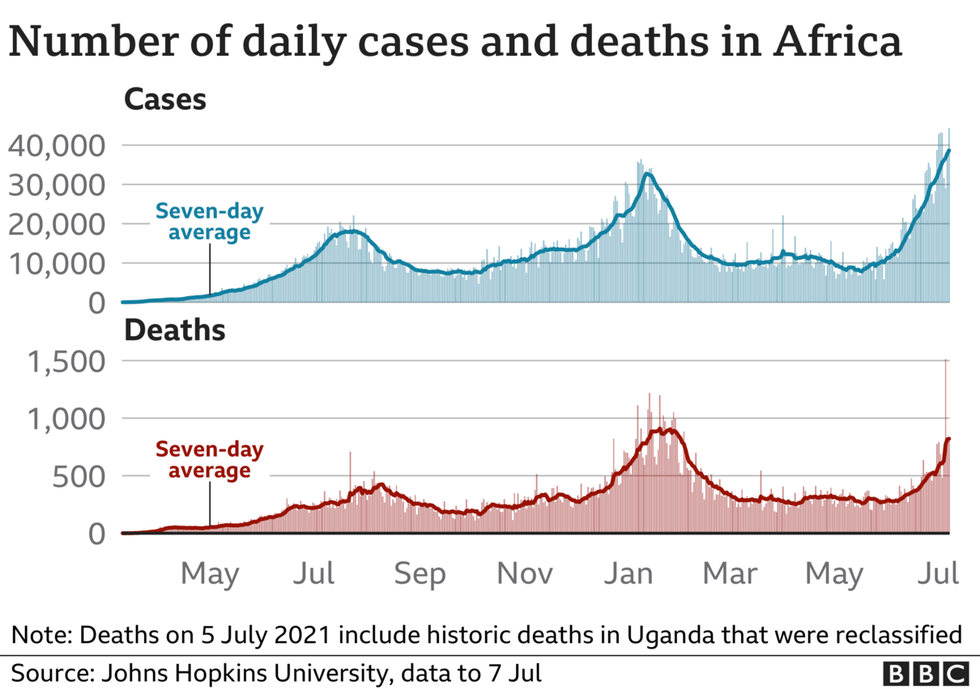
With the ultra-contagious Delta variant spreading, Africa recorded over 251,000 new Covid-19 cases during the week that ended July 4--a 20% jump from the previous week and a 12% rise from the high point in January, the World Health Organization (WHO) said Thursday.
As Dr. Matshidiso Moeti, WHO's regional director for the continent, put it: "Africa has just marked the continent's most dire pandemic week ever. But the worst is yet to come as the fast-moving third wave continues to gain speed and new ground."
"The end to this precipitous rise is still weeks away," Moeti warned. "Cases are doubling now every 18 days, compared with every 21 days only a week ago. We can still break the chain of transmission by testing, isolating contacts and cases, and following key public health measures."
According to BBC News:
There are 23 countries on the continent that have so far experienced a third wave of infections, with Senegal and Malawi the latest two to be affected.
Of those, 13 are experiencing a more severe wave than before, the Africa CDC says, with Uganda, the Democratic Republic of Congo, Namibia, Zambia, Rwanda, and Tunisia the worst hit.
Liberia, during the final two weeks of last month, saw Covid-19 cases surge by more than 300%.
"Since the beginning of June, we've had 21 deaths," Dr. Richard Doe, clinical coordinator at a Covid-19 treatment unit in the capital, Monrovia, told Al Jazeera. "Just to put that into perspective, it's more than we had from March to December last year."
"Our facilities here are struggling," said Doe, explaining that a lack of human resources means ventilators are not being used. "We need the public to help us in this fight against Covid. As long as the people out there do not practice those basic things--wearing masks, hand hygiene, social distancing, and getting vaccinated where available, it will be like a rat race we can't keep up with."
CNN on Friday detailed some scenes from South Africa:
Patients are crammed into every corner of the hospital's emergency room ward. They lie on beds and gurneys, or sit slumped in wheelchairs. Many suck on oxygen, but nobody talks. Some die while waiting for a bed.
On the worst nights in Johannesburg, currently in the grips of a terrible wave of infections, medics at one hospital must turn away ambulances carrying Covid-19 patients. It may be a diversion order more common to mass casualty events, but 16 months into the pandemic here, Covid-19 is a mass casualty event.
"It's devastating, it's soul destroying," said a senior doctor at a major public hospital in Johannesburg. "We are trained to save lives, but you revert to that wartime mentality. You revert to becoming numbed, you revert to becoming blunted."
The doctor explained that cars are arriving at the hospital "with desperately ill patients who have been turned away from other hospitals with no beds."
The outbreak in South Africa is now largely driven by the Delta variant, the Hindustan Times reported Friday--and new research has raised concerns about the threat that variant in particular poses to the unvaccinated and partially vaccinated worldwide.
South Africa, which on Friday announced plans to start vaccinating people under age 50, has administered at least one dose to only about 6% of its population, the newspaper noted, and just over 2% of people there are fully vaccinated.
Although that figure starkly contrasts with vaccination rates in rich countries such as the the United States, it is slightly higher than the continent's numbers. Only 16 million, or less than 2%, of Africans are now fully vaccinated.
Globally, nearly a quarter of people have received at least one dose of a Covid-19 vaccine--but only 1% of people in low-income countries have had at least one shot, according to Our World in Data.
A total of 66 million vaccine doses have been delivered to Africa--largely through bilateral deals and the WHO-led COVAX--and 50 million doses have been administered, but several countries are rapidly using up their supplies, the United Nations agency warns.
Moeti on Thursday highlighted that more doses are headed for the continent.
"COVAX partners are working around the clock to clinch dose-sharing pledges and procurement deals with manufacturers to ensure that the most vulnerable Africans get a Covid-19 vaccination quickly," the WHO regional director said. "These efforts are paying off. Our appeals for 'we first and not me first' are finally turning talk into action. But the deliveries can't come soon enough because the third wave looms large across the continent."
"With much larger Covid-19 vaccine deliveries expected to arrive in July and August, African countries must use this time to prepare to rapidly expand the roll-out," she added. "Governments and partners can do this by planning to expand vaccination sites, improving cold chain capacities beyond capital cities, sensitizing communities to boost vaccine confidence and demand, and ensuring that operational funding is ready to go when it is needed."
Even given those anticipated deliveries, public health leaders and justice advocates continue to decry the nationalistic approaches that wealthy nations have taken throughout the pandemic.
"Vaccine nationalism, where a handful of nations have taken the lion's share, is morally indefensible," Dr. Tedros Adhanom Ghebreyesus, WHO's director-General, declared Wednesday.
"Variants are currently winning the race against vaccines because of inequitable vaccine production and distribution, which also threatens the global economic recovery," Tedros added. "It didn't have to be this way and it doesn't have to be this way going forward."
The global Covid-19 death toll topped four million this week and provoked fresh demands that members of the World Trade Organization (WTO) support a temporary waiver of intellectual property rights for vaccines.
"This is a moral and human rights catastrophe," Colm O'Gorman, executive director of Amnesty Ireland, tweeted Thursday in response to the world's Covid-19 casualties.
"It's still not too late for Ireland to step up and do what is simply right," O'Gorman added, urging governments against the WTO waiver to "put people's lives and human rights ahead of the profits of Big Pharma."

From preserving marine biodiversity to protecting tropical forests from palm oil developers, the six recipients of a prestigious environmental award are "extraordinary individuals who have moved mountains to protect our planet."
"Each of them has selflessly stood up to stop injustice, become a leader when leadership was critical, and vanquished powerful adversaries who would desecrate our planet."
--Susie Gelman, Goldman Environmental Foundation
That's according to the Goldman Environmental Foundation, which for the past 30 years has honored grassroots activists from across the globe. This year's winners, described on Twitter by fellow activist Bill McKibben as "a great collection of #KeepItInTheGround leaders," were announced Monday.
Each of the six recipients hails from one of the world's inhabited continents.
Environmental lawyer Alfred Brownell is being recognized for his successful efforts to stop palm oil plantation developers from destroying forests vital to biodiversity in his home country of Liberia. For safety reasons--and after his government threatened to arrest Brownell for his activism--he now lives in exile in the United States.
Brownell told The Guardian about an encounter with private security guards in 2016.
"They threatened to cut off my head, to eat my heart, and drink out of my skull," Brownell said. "They began a war dance around the car. They were drinking and said they would cannibalize me."
Brownell added that receiving the honor has made him optimist about returning to Liberia in the future: "I hope this award will help change the minds of people in Liberia so we find more allies to speak to the government and the company. We need to find a way to engage with them so I can go home."
Bayarjargal Agvaantseren, of Mongolia, was selected for her work to establish the Tost Tosonbumba Nature Reserve in the South Gobi Desert--which is home to the snow leopard, a vulnerable species threatened by mining in the area. Due in part to pressure from Agvaantseren, the Mongolian government has canceled all mining licenses in the reserve.
Alberto Curamil--a Mapuche, Chile's largest indigenous group--organized the people of Araucania to block the construction of two hydroelectric projects that could have diverted more than 500 million gallons of water daily from the Cautin River, with dire consequences for the regional ecosystem. Curamil was arrested for his activism last year and remains in jail.
The first-ever recipient from North Macedonia, Ana Colovic Lesoska, campaigned against a pair of hydropower plants. The campaign she led convinced key international backers to pull their funding for the projects in the Mavrovo National Park, one of the last habitats for the endangered Balkan linx. She, too, has faced consequences for her activism.
"I've received death threats and warnings that I will be imprisoned," she told the The Guardian. "Newspaper articles have suggested we are aiding foreign governments just because the rivers we are protecting run to Albania."
Jacqueline Evans, of the Cook Islands, is also the first person from her country to receive the Goldman prize. Evans fought for legislation to restrict large-scale commercial fishing and seabed mining around her nation's 15 islands to safeguard south Pacific marine biodiversity--including whales, sea turtles, manta rays, seabirds, and sharks.
The North American recipient, Linda Garcia, was among the activists who blocked the construction of the continent's largest oil terminal, which was set to be built in Vancouver, Washington. Garcia organized residents of Fruit Valley, a racially diverse, low-income neighborhood whose air would have been impacted by the project.
"Each of them has selflessly stood up to stop injustice, become a leader when leadership was critical, and vanquished powerful adversaries who would desecrate our planet," Susie Gelman, president of the Goldman Environmental Foundation, said in a statement. "These are six ordinary, yet extraordinary, human beings who remind us that we all have a role in protecting the Earth."
The foundation planned an award ceremony in San Francisco for Monday evening featuring a speech from former Vice President Al Gore, a vocal environmental activist. The event will be broadcast on Facebook, Twitter, and YouTube, with updates posted on social media using the hashtag #GoldmanPrize30. A second ceremony is scheduled for May 1 at the National Academy of Sciences in Washington, D.C.
"Thirty years ago, when Richard and Rhoda Goldman started the Goldman Environmental Prize, the idea of celebrating grassroots environmentalists was a novel one," said Gore, a friend of the founders. "Today, thanks in large part to the Goldmans, the world recognizes just how important it is to honor and illuminate those who have shown courage in the face of environmental destruction."

In January, I was in Washington for a couple of days and early on a Saturday morning took a Lyft car from Capitol Hill to Georgetown for a meeting with friends. The driver and I began to talk.
I know, I know, the chat with the Uber or Lyft driver has become kind of a cliche in this kind of piece but hear me out.
He was from Liberia, and as a child had fled that country with his grandmother during the civil wars there, vicious fighting that killed an estimated 200,000 and sent a million more to refugee camps in Guinea, Ghana and other African nations.
Several thousand, perhaps as many as 34,000, came to the United States, protected at first during George H. W. Bush's administration by an order of temporary protected status (TPS). Refugees from other troubled nations, including El Salvador, Honduras, Sudan, Haiti and Nepal have received the TPS designation as well.
In 1999, when TPS for Liberians expired, President Bill Clinton set up Deferred Enforcement Departure (DED) status instead, stating that while "conditions have improved... the political and economic situation [in Liberia] continues to be fragile." The refugees could stay.
The Lyft driver had worked hard to make a life here. He'd just left a dangerous yet lucrative job working at an electric arc furnace that at 9,000 degrees melted down automobiles for the steel and aluminum - but then he'd done some reading and became scared about the toxins he was breathing in. Now he was taking classes and driving to make ends meet.
He told me he actually liked Secretary of State Mike Pompeo - Pompeo had just made his big speech in Cairo extolling America as a force for good and he admired that, he said, because as a young Liberian he had seen what happens when the civil order in a country disintegrates into brutality and death.
I wonder how he feels today about Pompeo and his capricious boss, Trump. My Lyft driver and his fellow Liberians who are alive and well because of the DED program almost saw it eliminated this weekend and faced deportation as undocumented immigrants. But just days before expiration, the administration relented and extended it for another year, through the end of March 2020.
Until now, such extensions have been commonplace - four past presidents regularly have given their approval, citing continuing instability and an outbreak of Ebola in West Africa. What's more, there's a long, historic connection between our two countries. Liberia was colonized by America in the 19th century as a home for former slaves and their families, a plan, Orion Donovan-Smith notes in The Washington Post, "supported by some abolitionists and by slaveholders who feared revolts led by free blacks."
Hostility between descendants of these newcomers and the Africans already there helped foment the bloodshed of civil war. Yet many of those who are here now were so young when they left, they have no memory of their homeland.
The off-again, on-again status of the Liberian refugees is unkind to them and emblematic of the Trump administration's inability to craft an immigration policy that isn't riven with resentment and confusion.
If we can be certain about anything when it comes to this White House it's that nothing is certain. Last year, when Trump announced he was ending DED, the White House declared, "Liberia is no longer experiencing armed conflict and has made significant progress in restoring stability and democratic governance."
Now, in the face of a lawsuit supported by ten state attorneys general and a slew of letters from member of Congress, including House majority leader Steny Hoyer, Trump did a 180-degree backflip, writing, "Upon further reflection and review, I have decided that it is in the foreign policy interest of the United States to extend the wind-down period for an additional 12 months. The overall situation in West Africa remains concerning, and Liberia is an important regional partner for the United States."
That's good news - but only for now. Doubtless the reversal was in part due to Trump's well-known fear of bad optics - the same apprehension that led to the president's sudden reversal of his administration's plan to cut funding for the Special Olympics.
Initially, he may have figured that the Liberians affected were so few in number that no one would notice his deportation order. And when he changed his mind and shifted his tone, he may have thought he was throwing a bone to a handful of immigrants for good publicity while continuing to grind up the skeleton of what's left of American immigration policy.
Yet he can't have been pleased by the outpouring of public support for Liberians in the US and the powerful opinion pieces by those affected, such as the op-ed by Yatta Kiazolu, a doctoral candidate at UCLA, who wrote, "After 22 years of living, studying and working in the United States with government authorization, how could I start to untangle the roots that I'd established here? How could I begin to establish them in Liberia, a country where I have no connections and only some distant relatives?"
Of course, Trump's first instinct to put an end to DED, as Kiazolu observed, "continues the Trump administration's callous pattern of stripping protections from immigrants -- a natural extension of the efforts to rescind Deferred Action for Childhood Arrivals [DACA]and take away temporary protected status from those who fled violence and disaster in their home countries. Coupled with a refusal to provide avenues for gaining legal permanent residency in the United States, these actions have destabilized the lives of hundreds of thousands of people, threatening to cut off their futures and divide their families. Systematically dismantling these discretionary relief programs is, seemingly, the most expedient way for the administration to pursue its agenda: to force as many nonwhite, non-European immigrants out of the country as possible by capriciously taking away their legal status."
Despite his stated desires, other lawsuits have so far prevented Trump from ending the DACA Dreamers program or Temporary Protected Status. And there are several pieces of legislation pending in both the House and Senate that could bring relief to all those who are in the country under these tenuous circumstances, including a bill protecting the Dreamers reintroduced by Senators Dick Durbin and Lindsey Graham just last week. But whether the various proposals can be reconciled and most important, signed by this president is, to say the least, in doubt.
"Feckless." That's how even Mark Krikorian, executive director of the conservative, pro-restricted immigration, of the Center for Immigration Studies described our incoherent immigration policy.
I don't agree with Krikorian on much of anything--he made his comment while attacking DED status--but feckless is an excellent choice of words. In the last few days, Trump's threatened to shut down the border "if Mexico doesn't get with it," and vindictively cut off foreign aid to Guatemala, Honduras and El Salvador, a move that can only worsen the flow of desperate refugees toward the United States.
These are just the latest in an endless series of inept, poorly advised, mean-spirited decisions on immigration, reflective of his own racial animus and the egomaniacal political bloodlust that drives him to pander to his base.
Last week, at his Michigan rally, Trump derisively mocked those who seek asylum and screamed, "It's a big fat con job!" Look who's talking. This is an ignorant, cruel and dangerous man.
The West African country of Liberia, which was ground zero for worst Ebola outbreak in recorded history, was declared epidemic-free by the World Health Organization on Saturday.
The WHO, which is tasked by the United Nations with directing international responses to epidemics, made the announcement from the Liberian capital of Monrovia.
"WHO declares Liberia free of Ebola virus transmission," the organization announced in a statement that was read by Dr. Alex Ntale Gasasira, the WHO representative to Liberia. "Forty-two days have passed since the last laboratory-confirmed case was buried on 28 March 2015. The outbreak of Ebola virus disease in Liberia is over."
However, the organization warned, neither the country nor the region is in the clear: "While WHO is confident that Liberia has interrupted transmission, outbreaks persist in neighboring Guinea and Sierra Leone, creating a high risk that infected people may cross into Liberia over the region's exceptionally porous borders."
Furthermore, Liberian President Ellen Johnson Sirleaf told the Associated Press that "The pain and grief will take a generation to heal." The destruction and loss suffered as a result of the outbreak is a "scar on the conscience of the world," she added.
The country's economy was decimated by the outbreak, which killed at least 11,000 people across the region and more than 4,700 Liberians.
The World Health Organization and international community--especially wealthy nations--were broadly criticized for their negligent response to the crisis.
In a press statement issued in late August, Brice de le Vingne, Doctors Without Borders director of operations, slammed western states for their isolationist policies towards the epidemic: "Self-protection is occupying the entire focus of states that have the expertise and resources to make a dramatic difference in the affected countries. They can do more, so why don't they?"
At their announcement on Saturday, the WHO briefly nodded at the poor global response but fell short of a full-throated critique. "International support was slow to start, but abundant when it arrived," the organization said.
The Ebola death toll in the three West African countries most impacted by the virus has climbed to at least 7,373 of 19,031 known infections, the World Health Organization revealed in data released Saturday.
Western Sierra Leone is the "hotspot" of the ongoing outbreak, according to the WHO, which notes that this country has the highest infection rate, followed by Liberia and then Guinea.
However, Liberia accounts for far more Ebola deaths, leading some to question the accuracy of the WHO's statistics on infection rates.
Nonetheless, the data shows an increase in overall cases, which are up by 500 since WHO data was last released on December 17.
The numbers were released following news Friday that Sierra Leone's top-ranking doctor had succumbed to Ebola, making him the 11th of the country's 120 doctors to die from the disease, according to the Guardian.
Meanwhile, humanitarian aid workers have criticized the global community for its failure to respond adequately as West African governments and grassroots initiatives such as the Citizens Alliance to Stop Ebola in Liberia struggle to stem the ongoing emergency.
"The international response to the Ebola crisis in West Africa has been slow and uneven leaving local people, national governments and non-governmental organizations (NGOs) to do most of the practical, hands-on work," the NGO Doctors Without Borders//Medecins Sans Frontieres declared earlier this month.
The lackluster global response comes despite the fact that Western-driven economic policies played a key role in gutting West African public health systems.
"People are still dying horrible deaths in an outbreak that has already killed thousands," said Dr. Joanne Liu, MSF international president. "We can't let our guard down and allow this to become double failure, a response that was slow to begin with and is ill-adapted in the end."
WASHINGTON - The United States proposed this week that the international community write off $100 million in debt owed by West African countries hit hardest by the current Ebola outbreak. The money would be re-invested in health and other public programming.
U.S. Treasury Secretary Jack Lew will be detailing the proposal later this week to a summit of finance ministers from the Group of 20 (G20) industrialised countries. If the idea gains traction among G20 states, that support should be enough to approve the measure through the International Monetary Fund (IMF), where the United States is the largest voting member.
"The plan is for that money to be re-invested in social infrastructure, including hospitals and schools ... to deal with the short-term problem of Ebola but also the long-term failure of the health systems that allowed for this outbreak." --Jubilee USA's executive director Eric LeCompte"The International Monetary Fund has already played a critical role as a first responder, providing economic support to countries hardest hit by Ebola," Lew said in a statement to IPS.
"Today we are asking the IMF to expand that support by providing debt relief for Sierra Leone, Liberia and Guinea. IMF debt relief will promote economic sustainability in the worst hit countries by freeing up resources for both immediate needs and longer-term recovery efforts."
These three countries together owe the IMF some 370 million dollars, according to the U.S. Treasury, with 55 million dollars due in the coming two years. Yet there are already widespread fears over the devastating financial ramifications of Ebola on Guinea, Liberia and Sierra Leone, in addition to the epidemic's horrendous social impact.
Last month, the World Health Organisation warned that the virus now threatens "potential state failure" in these countries. The World Bank, meanwhile, estimates that the virus, which has already killed more than 5,000 people and infected more than 14,000, could cost West African countries some 33 billion dollars in gross domestic product.
Of course, much of the multilateral machinery is often too cumbersome to respond to a fast-moving viral outbreak. Yet there is reason to believe that the U.S. plan could have both immediate and long-term impacts.
That's because the plan would see the IMF tap a unique fund set up in the aftermath of the 2010 Haiti earthquake, which facilitated the cancellation of nearly 270 million dollars of Haitian debt to the IMF. Called the Post-Catastrophe Debt Relief (PCDR) Trust, it is aimed specifically at responding to major natural disasters in the world's poorest countries.
Originally, the PCDR Trust was capitalised with more than 420 million dollars. Today, a U.S. Treasury spokesperson told IPS, the trust has some 150 million dollars in it - money that would be available almost immediately.
"Our proposal is for the IMF to provide debt relief for these Ebola-affected nations from this trust," the spokesperson said. "The U.S. would like to see around 100 million dollars put toward this effort, however the precise amount will need to be determined in consultations with the IMF and its membership."
The IMF, meanwhile, says it is preparing to consider the proposal. In September the Washington-based agency made available 130 million dollars in immediate support to Guinea, Liberia and Sierra Leone.
"We are very glad that some donors have expressed an interest in increasing support for the Ebola-affected countries. We are reaching out to all donors to see how we might be able to take this forward ... using all the tools available to us," an IMF spokesperson told IPS.
"[Debt relief] decisions are made according to the merits of the particular case and this would be approached in the same way. We would expect the Board to be briefed soon on this topic."
Ebola's "natural disaster"
For development and anti-poverty advocates, debt obligations on the part of poor countries constitute a key obstacle to a government's ability to respond to critical social needs, both in the short and long term.
In the West African epicentre of the current Ebola outbreak, many analysts have held chronic low national health spending directly responsible for allowing the epidemic to spiral out of control. And when looking at feeble public sector spending, it is impossible not to take into account often crushing debt burdens.
For instance, Guinea spent a little more than 100 million dollars on public health in 2012 but paid nearly 150 million dollars that same year on internationally held debt, according to World Bank figures provided by Jubilee USA, an anti-debt advocacy network that has spearheaded the push for the United States to make the current proposal.
"As bad as Ebola has been, some of these countries have far greater challenges with deaths from malaria than from Ebola," Eric LeCompte, Jubilee USA's executive director, told IPS.
"The amount is incredibly important because it cancels a significant portion of the debt completely. And the plan is for that money to be re-invested in social infrastructure, including hospitals and schools ... to deal with the short-term problem of Ebola but also the long-term failure of the health systems that allowed for this outbreak."
LeCompte was also involved in the creation of the Post-Catastrophe Debt Relief Trust, in the aftermath of the Haitian earthquake. His office has advocated for the fund's monies to be used since then - for instance, to react to flooding in Pakistan and Typhoon Haiyan in the Philippines.
But he says these and other proposals have been rejected by the IMF's membership, on the rationale that these countries were developed enough to be able to mobilise financing in other ways. (The IMF says PCDR funds are for response to "the most catastrophic of natural disasters" in "low-income countries", when a third of a country's population has been affected and a quarter of its production capacity destroyed.)
Not only are Guinea, Liberia and Sierra Leone among the poorest countries in the world, but the Ebola outbreak there has a potentially direct impact on the rest of the globe.
"This is a very clear opportunity to point to the 150 million dollars left in that fund and to note that Ebola is every bit the same as the Haitian earthquake in terms of being a regional calamity," LeCompte says.
"The difference is that this is also a long-term investment in the very problems that allow Ebola to spread. So we'd be not only addressing the current issue, but also the next disease outbreak in that region."
It is unclear whether there is a mechanism in place to top up the PCDR Trust in the future. The IMF states that "Replenishment of the Trust will rely on donor contributions, as necessary."
But for his part, LeCompte says the fund has the potential to fill a significant gap: offering a pot of money, immediately available, that could be quickly mobilised to deal with true crises afflicting the world's poorest countries, from hurricanes to major financial defaults.
UNITED NATIONS - The widespread outbreak of Ebola in West Africa, which has resulted in over 4,500 deaths so far, is also threatening to trigger a food crisis in the three countries already plagued by poverty and hunger.
Dr. Shenggen Fen, director-general of the Washington-based International Food Policy Research Institute (IFPRI), told IPS the crisis is expected to be confined mostly to the countries directly affected by the spreading disease: Liberia, Sierra Leone and Guinea.
UNITED NATIONS - The widespread outbreak of Ebola in West Africa, which has resulted in over 4,500 deaths so far, is also threatening to trigger a food crisis in the three countries already plagued by poverty and hunger.
Dr. Shenggen Fen, director-general of the Washington-based International Food Policy Research Institute (IFPRI), told IPS the crisis is expected to be confined mostly to the countries directly affected by the spreading disease: Liberia, Sierra Leone and Guinea.
Asked whether the food shortages will also reach countries outside West Africa, he said Ebola is triggering a food crisis through a series of interrelated factors, including farmer deaths, labour shortages, rising transportation costs, and rising food prices.
"Within these countries, where undernourishment has long been a problem, the food crisis may persist for decades," he warned.
And because Sierra Leone, Guinea, and Liberia are all net food-importing countries, the Ebola-triggered food crisis is unlikely to spread to other countries in the region or beyond, Dr. Fan added.
Global food prices tend to have transmission effects on regional or national food prices, but for small markets (on a global scale) such as these three countries, the transmission effect of food prices is unlikely to pass beyond their own boundaries - so long as the disease itself is not transmitted, he said.
According to the latest figures released by the World Health Organisation (WHO), there are over 9,000 cases of Ebola, including 4,262 cases in Liberia, 3,410 in Sierra Leone and 1,519 in Guinea.
The death toll is highest in Liberia (2,484), followed by Sierra Leone (1,200) and Guinea (862).
U.N. Spokesperson Stephane Dujarric told reporters Monday the WHO has officially declared Nigeria free of Ebola virus transmission, after 42 days without a single case.
WHO called it "a spectacular success story that shows that Ebola can be contained".
"Such a story can help the many other developing countries that are deeply worried by the prospect of an imported Ebola case and are eager to improve their preparedness plans," he said.
Dujarric said the announcement comes only a few days after Senegal was also declared Ebola-free.
He said the trust fund set up by Secretary-General Ban Ki-moon to battle the deadly disease now has about 8.8 million dollars in deposits and 5.0 million dollars in commitments.
In total, 43.5 million dollars have been pledged and the secretary-general continues to urge countries to turn these pledges into action as soon as possible.
He expressed regrets over the Ebola-related death of a UN-Women staff member in Sierra Leone. His spouse is currently receiving treatment.
"All measures to protect staff at the duty station in Sierra Leone are being taken as best as possible under the current circumstances," Dujarric said.
This includes decontamination of the U.N. clinic, disposal of the isolation facility and contact tracing, he added.
In a statement released Tuesday, IFPRI painted a grim picture of the situation facing all three countries.
Schools in Sierra Leone have closed, shutting down critical feeding programmes for children. And restrictions on the consumption of bush meat, the suspected source of Ebola, have eliminated a traditional source of protein and nutrition from local diets.
"In addition, the costs of staple foods including rice and cassava are rising precipitously in the affected areas as crops are abandoned and as labor shortages grow," the statement added.
Food that would be imported from these areas is not making its way to other regions, either.
"So, as we weigh the dangers of this dreaded disease, we must not forget the very real threats it poses to food security," the group warned.
"The global community must come together to ensure that there are safety nets to protect not only those infected with the disease, but also those whose access to food is severely affected," IFPRI added.
Asked to identify these safety nets, Dr. Fan told IPS social safety nets are needed to protect not only those infected with Ebola, but also those whose access to food is severely affected.
These safety nets, which could be in the form of cash or in-kind transfers (context-specificity is important here), should be accompanied with nutrition and health interventions.
For example, a conditional cash transfer programme linked to health can help improve access to nutritious foods, particularly when prices are high, while promoting health service use, he added. "This is important, because investing in the nutrition and health of vulnerable populations could lower the mortality rate of diseases like Ebola, as nutritional status and infection are intricately linked."
In the post-Ebola era, Dr. Fan said, combined social protection and agricultural support interventions will be crucial to build resilience to future livelihood shocks.
Asked how many people will be affected by this impending food crisis, he said with Ebola claiming lives of thousands of people in Sierra Leone, Guinea, and Liberia, the mounting food crisis is impacting thousands more still.
Recent efforts by the World Food Programme (WFP) to provide food assistance to around 1.3 million people in these three countries indicate an idea of the scope of the current crisis.
The Food and Agriculture Organisation (FAO) is also providing food assistance to nearly 90,000 farming households to abate the food security crisis, he pointed out.
As the harvest season is beginning, labour shortages are putting the food security of tens of thousands of people at risk in particularly affected areas, he declared.
When the Texas Health Presbyterian Hospital missed a crucial diagnosis of the Ebola virus and released Liberian Thomas Eric Duncan to go home, it unleashed a sequence of events that is still unfolding rapidly.
As in the great AIDS panic, the introduction of the Ebola infection into the American populace has resulted in confusion, speculation, and hysteria. Even perfectly healthy individuals, such as American reporters who have been to the West African region, find themselves being shunned because of irrational fears.
For better or worse, the response of the authorities to this crisis will go down in history. Certain categorical declarations will particularly stand out--and in some cases return as painful ironies. As an example, in late July, Stephen Monroe--the deputy director of the CDC's National Center for Zoonotic Infectious Disease--stated, "Ebola poses little risk to the U.S. general population," adding that, "the likelihood of the outbreak spreading outside of West Africa is very low."
In an effort to tamp down fears over Ebola, CDC director Thomas Frieden asserted in October that "Ebola is scary. It's a deadly disease. But we know how to stop it." It is unclear whether the "we" refers to the CDC, health facilities more generally, or some other entity, but this firm and sweeping assertion was called into question as news broke of the first and then a second case of Ebola transmission to Thomas Duncan's caregivers at Texas Presbyterian Hospital.
Earlier this month, David Lakey, commissioner of the Texas Department of State Health Services, famously said of Dallas, "This is not West Africa. This is a very sophisticated city." Still not sophisticated enough, apparently, to prevent one fumble after another.
U.S. Lapses
The supposed "mystery" as to how these caregivers contracted Ebola when they were supposedly shielded from transmission by their personal protective equipment (PPE) is actually no mystery at all.
As a physician at a wound care center in Southern California, I go through 10 to 20 units of protective gear every day, one for each patient. A quick, self-administered test on removing my PPE revealed that I did it with less than 100 percent safety. It is, quite frankly, not easy.
With Ebola, even 99 percent safety is not good enough. Many hospitals in the United States use PPE for procedures such as wound repair and colonoscopies. And in many wards and intensive care units, healthcare staff don PPE for cases of MRSA or VRE. But not only does the care required in such "ordinary" protection pale beside the vigilance involved in Ebola exposure, the PPE itself is quite different.
So the answer to whether "we," as Frieden put it, know how to stop the virus here in the United States might well be a "no" at worst and a "sort of" at best.
Indeed, National Nurses United Executive Director RoseAnn DeMoro has claimed that there is an absence of any protocol at the Texas Presbyterian hospital on how to deal with the deadly virus. Other hospitals have opted for the World Health Organization's Ebola protocol instead of the CDC's because of its extra guidelines for hand sanitation.
The CDC poster for removal of PPE shows the use of only a single pair of gloves and appears highly lacking compared to the painstaking measures described by Australian nurse Sue Ellen Kovack at a Sierra Leonean Ebola treatment center. Of note in her account is the liberal dousing with a chlorine (or bleach) spray from head to toe, a chlorine hand rinse, hand washing at least eight times during the procedure, and the use of two pairs of gloves instead of just one as recommended by the CDC. On October 16, the CDC effectively admitted that its own guidelines were lax and has moved to the more exacting guidelines.
Ironically, rough-and-ready Ebola treatment centers like the tents constructed by agencies like Doctors Without Borders are much better equipped for safety procedures like the chlorine bath than many modern Western facilities. To do this in a technologically advanced U.S. hospital, separate alcoves would need to be built in designated spaces to accommodate a "spraying area." That could be extremely complicated in the average intensive care unit.
Learning from Africa
Perhaps we in the United States are learning a small lesson in humility.
Is it possible, for example, that Nigeria, of all places, might have some wisdom to convey to the United States? Both Nigeria and Senegal moved quickly to quell an Ebola outbreak through meticulous contact tracing, coordinated national action, exhaustive interviews, and activation of an Ebola Incident Management Center. Both countries are now reportedly free of the disease.
Although the story is not yet over, the U.S. government has lauded Nigeria's initial management of the outbreak. Indeed, the CDC has now ordered dozens of high-tech, infrared, no-touch thermometers to be used in screening procedures at U.S. gateway airports--the same ones that are already being used in West Africa.
David Lakey is right: Texas is not West Africa. But every once in a while, the West African example is worth following.
Although American officials are making lots of reassuring noises about screening passengers coming from West Africa for signs of the dreaded Ebola virus, the truth is that the only way to totally safeguard against the spread of the disease is to close our borders entirely. And I don't see that happening anytime soon.
Although American officials are making lots of reassuring noises about screening passengers coming from West Africa for signs of the dreaded Ebola virus, the truth is that the only way to totally safeguard against the spread of the disease is to close our borders entirely. And I don't see that happening anytime soon.
Talk about an unexpected side effect of globalization. Goods and services spread around the globe at the stroke of a keyboard or the roar of a jet engine, but the same mechanisms we celebrate as having pumped up the global economy also, potentially, have a darker side.
What was it Marx said about the bourgeoisie digging its own grave?
I keep hearing the undertone, in the media reporting on Ebola, of the "blame-the-victim" complaint, "What's wrong with these people? Why are they living in such poverty? Why don't they have doctors, nurses, hospitals? Look how their squalor is putting us all at risk?!"
There is truth to this. The poor folks in Liberia, Guinea and Sierre Leone, former colonies of the U.S., France and Great Britain, respectively, have not managed to modernize their societies. This is due to a number of factors, including corrupt leadership (strongmen often propped up by the Western powers), violent civil wars (armed by Western weapons manufacturers and distributors), and banana republic-style economies where Western corporations rule by extraction, extortion and exploitation, without giving anything back in taxes, infrastructure or education for the local people.
This is where the West has made its big mistake. How could we in the so-called developed world be so naive as to think that we could ignore the poverty and suffering of other parts of the globe without that poverty and suffering coming back to haunt us?
If we had invested in schools, medical facilities and housing in Liberia, instead of sending endless supplies of assault rifles and ammunition, we would not be worrying about Ebola now.
Likewise, if we had invested in education and economic development in the Middle East, instead of relying corrupt warlords to keep the population in line, we would not be dealing with a seemingly endless morphing insurgency of Taliban-Al Quaeda-Islamic State terrorists.
It really is true that an ounce of prevention is worth a pound of cure.
In a globalized society, pretending that vast disparities of wealth don't matter is just plain stupid. Imagining that a vicious virus can be contained by airport thermometer checks is as ridiculous as imagining that an international terrorist network can be stopped by a few fly-by bombings.
The world's leaders need to take a lesson from Malala Yousefzai, the 17-year-old girl who won the 2014 Nobel Peace Prize for her steadfast insistence, even after nearly having her head blown off by the Taliban, that girls should be educated.
Study after study has shown that when a society educates and empowers women, it becomes more economically successful and more politically stable.
This week, in my African Women Writing Resistance class, I've been reading and discussing the autobiography of Ellen Johnson Sirleaf, President of Liberia and first woman head of state in modern Africa.
Sirleaf, who won the Nobel Peace Prize in 2011, has been in the news a lot lately, begging for help in containing the spread of Ebola and warning grimly of the consequences of international inaction.
She came to office vowing to take her country back from the warlords and reintegrate child soldiers, to educate girls and boys and build a sustainable economy. She's made great strides, but the stark pictures of the pathetic state of the nation's health care infrastructure make it clear how far Liberia, like other poor African nations, still has to go.
The bottom line is this: if we want safety, we have to build towards it, step by step, from the ground up. We can't ignore poverty and then get mad when impoverished sick people dare to infect us, or when desperate people turn to radical Islam as a way out of their misery.
There is no excuse, in our globalized world, for the dramatic disparities of wealth and poverty that exist today. Those of us lucky enough to live comfortably in the U.S. or Europe should be using our privilege to advocate for those less fortunate.
Not just out of altruism. Out of self-preservation, too.
If we had been helping Liberia and other West African nations build good social infrastructure, instead of extracting profits from diamonds, rubber and gun sales, we would not be worrying about the spread of Ebola today.
If we had been educating children in Syria, Yemen and Iraq instead of supporting corrupt dictators and ignoring the plight of ordinary people, we would not be facing the spread of Islamic extremism today.
How many innocent humans will have to die before we begin to understand that simple adage? An ounce of prevention is worth a pound of cure.