

SUBSCRIBE TO OUR FREE NEWSLETTER
Daily news & progressive opinion—funded by the people, not the corporations—delivered straight to your inbox.
5
#000000
#FFFFFF
To donate by check, phone, or other method, see our More Ways to Give page.
Daily news & progressive opinion—funded by the people, not the corporations—delivered straight to your inbox.

"Over half the provisions of the Big Ugly Bill have already gone into effect, and the negative results are already devastating."
Independent healthcare analyst Charles Gaba on Thursday published a detailed report estimating that up to 10 million people living in the US have lost their healthcare coverage since the start of President Donald Trump's second term.
In his analysis, Gaba brought together the most recent enrollment data for Medicaid, the Children's Health Insurance Program (CHIP), Medicare, and the Affordable Care Act (ACA).
Breaking things down by program, Gaba estimated there are 5.9 million fewer people enrolled in Medicaid and CHIP, as well as at least 4.5 million fewer people enrolled in the ACA, since Trump returned to power in January 2025.
These losses in coverage are somewhat mitigated by Medicare, whose enrollment has increased by around 1.6 million people during Trump's second term.
Losing access to these programs doesn't mean that the people were on them have gotten well paying jobs and are receiving insurance from their employer, Gaba wrote. Given that the unemployment rate has risen during Trump's second term, Gaba suggested it is highly unlikely that there are now more people who get employer-sponsored coverage now than in January 2025.
Depending on a number of variables, Gaba concluded, somewhere between 8.8 million to 10.3 million fewer people now have healthcare coverage.
Adjusting for population growth, Gaba added, "you get a grand total of between 10.27 million and 11.75 million more Americans not enrolled in a public healthcare coverage program as of May 2026 than in were as of January 2025."
The healthcare analyst noted that "this isn't quite the same thing as counting how many lost coverage, but not having healthcare sucks regardless of how you slice it."
He also pointed out that the lost in healthcare coverage all came before the Medicaid work requirements from the GOP's 2025 budget law are put into effect.
"Over half the provisions of the Big Ugly Bill have already gone into effect," wrote Gaba, "and the negative results are already devastating."
Gaba's analysis was published just days after the Georgetown University Center for Children and Families released a report estimating that nearly 2.5 million children in the US have lost access to Medicaid or CHIP during Trump's second term.
Trump and congressional Republicans have taken a number of actions that have made healthcare less affordable.
First, they cut spending on Medicaid by an estimated $900 billion over a 10-year period when they enacted the One Big Beautiful Bill Act in 2025. The Congressional Budget Office projects these cuts will leave more than 10 million fewer people enrolled in the program by 2034.
GOP lawmakers last year also refused to extend enhanced subsidies for insurance plans purchased through the ACA, even as insurers raised premiums on those plans by an average of 26% this year, according to an analysis published by KFF.
According to Wednesday reporting by Politico, hospitals are sounding the alarm about new regulations being proposed by the Centers for Medicare and Medicaid Services that they say would cost hundreds of billions of dollars in lost revenue.
"If the rules are finalized and they lose hundreds of billions on top of Congress’ funding cuts," Politico reported, "hospitals say they’ll be forced to reduce services, lay off workers, consolidate operations or shutter entirely."
The drop in children covered by Medicaid comes before the most draconian changes to the program made by Republicans' 2025 budget law are set to take effect next year.
Nearly 2.5 million children living in the US have lost access to Medicaid or Children's Health Insurance Program coverage during President Donald Trump's second term, according to data published on Monday by the Georgetown University Center for Children and Families.
In total, five states have seen children's enrollment in Medicaid and CHIP fall by 10% or higher since January 2025, with Indiana seeing a drop in enrollment in those programs of more than 23%.
Colorado and Hawaii were the only two states to see a net increase in children in Medicaid or CHIP over that same period.
Joan Alker, executive director of the Center for Children and Families, described the drop in children enrolled in the programs as "a lot," and said it was important to track because "when Medicaid child enrollment declines, the number of uninsured kids typically goes up."
President Donald Trump and congressional Republicans cut spending on Medicaid by an estimated $900 billion over a 10-year period when they enacted the One Big Beautiful Bill Act in 2025. The Congressional Budget Office projects these cuts will leave more than 10 million fewer people enrolled in the program by 2034.
One way the GOP budget law is projected to kick people off Medicaid has been to add extra administrative burdens and paperwork for people who qualify for the program.
As explained by a Scripps News report published last week, Medicaid starting next year will make beneficiaries enroll twice a year instead of just once, while also mandating adults who "earn above a typical income cutoff and do not have children... work or volunteer at least 80 hours a month, or enroll in school."
Eileen Appelbaum, co-director of the Center for Economic and Policy Research, told Scripps News that this will result in many people not receiving Medicaid coverage despite being qualified for it.
"The best guesses from the experts are that two-thirds of the people that will be disqualified will actually be eligible, but they just couldn't handle the paperwork," Appelbaum explained.
In an op-ed published by Stat on Monday, Brown University epidemiologists Abdullah Shihipar and Brandon DL Marshall highlighted how getting out of the new Medicaid work requirements by proving yourself "medically frail" is shaping up to be a "nightmare scenario for millions of Americans."
"Let’s say you are undergoing cancer treatment, but you don’t have the right paperwork for your renewal," Shihipar and Marshall wrote. "As a result, you’re disenrolled from Medicaid. You desperately try to fix the mistake, but you are faced with long wait times and no answers, so you cease treatment altogether... Paperwork here is not merely an annoyance, it is a matter of life or death for millions with Medicaid coverage."
The Centers for Medicare and Medicaid Services' implementation of the One Big Beautiful Bill narrows the very protections Congress included to prevent vulnerable people nationwide from losing the health coverage they need.
The biggest Medicaid fight today isn't happening in Congress—it's happening inside the Centers for Medicare and Medicaid Services.
Now, a year after H.R. 1’s passage (the 2025 federal reconciliation bill enacting significant cuts and changes to Medicaid), CMS’ recently issued interim final rule (IFR) implementing the law’s work-reporting requirements in the program narrows the very protections Congress included to prevent vulnerable people nationwide from losing the health coverage they need.
The Congressional Budget Office previously estimated that more than 5 million people will lose Medicaid coverage because of these requirements. Already a conservative estimate as other organizations estimated over 10 million people are at risk of losing coverage, the number will surely be higher given CMS' IFR goes beyond the statutory language of the law.
The clearest example of this is the IFR's treatment of the medically frail exemption.
If the goal is really healthier communities and greater workforce participation, making it harder for medically vulnerable people to keep their health insurance is exactly the wrong approach.
Congress recognized that people living with complex medical conditions, disabilities, and chronic illnesses, including substance use disorder (SUD), should be protected from burdensome work-reporting requirements. As such, H.R. 1 specifically includes “medically frail” individuals among those exempt from the new requirements.
Yet CMS has added a new hurdle, putting millions of eligible Americans at dire risk of losing access to essential healthcare.
Under the IFR, people with SUD and other qualifying health conditions must also demonstrate that their condition "significantly impairs" their ability to satisfy the requirement before they can qualify for the exemption. This additional standard does not appear in the statute and will inevitably reduce the number of people who can secure the exemption.
For people living with SUD, the consequences could be profound.
While SUD is a chronic but treatable medical condition, pervasive stigma and discriminatory barriers have led to fewer than 1 in 5 people who need treatment actually receiving it. Amid persistent addiction and overdose crises, we should be making it easier for people to access the services and supports they need to become and stay well, not erecting additional barriers to lifesaving care.
Moreover, while CMS' rule relies heavily on Medicaid claims data and provider documentation to identify individuals who qualify as medically frail, the administration’s approach overlooks the reality that many people with SUD have never entered treatment due to the above-mentioned stigma and discrimination. Requiring additional documentation will not "motivate" people to seek care, as CMS suggests. Instead, it creates yet another barrier for people who are already among the hardest to reach.
When people are deprived of Medicaid access, their ability to engage in preventive care, behavioral health services, medications, and treatment that keep chronic conditions under control is also lost. And it doesn’t take a rocket scientist to understand how untreated health conditions can not just impede a person’s capacity to work but quickly lead to costly emergency services.
These are not only personal tragedies—they are costly public policy failures.
Taking away health coverage does not eliminate health needs. It just shifts and raises costs while undermining public health and safety. Access to healthcare is precisely what enables many people to work, care for their families, and be productive community members, so why are we erecting so many barriers?
If the goal is really healthier communities and greater workforce participation, making it harder for medically vulnerable people to keep their health insurance is exactly the wrong approach.
Last month, both our organizations, along with many other leading advocates nationwide, explicitly articulated these concerns and submitted comments urging the agency to reverse course and faithfully reinforce the protections Congress included in the law. While CMS' public comment period on the IFR is now closed, all those who share the same perspective can still take action by calling their members of Congress to share their concerns about the impact of H.R. 1 and specifically, how the administration is planning to implement the law.
A year after H.R. 1’s passage, the question is no longer simply about what Congress enacted—it is whether the regulations that make the law real will preserve purposeful protections or quietly erode them through administrative action.

New fact sheets detail how people in every US state are suffering from the Republican Party's assault on Medicaid and the Affordable Care Act.
The unprecedented healthcare cuts that President Donald Trump and the Republican Party enacted last summer have impacted people in all 50 US states, stripping insurance coverage from around 8 million Americans total and wreaking havoc on hospitals and other providers nationwide.
The advocacy group Protect Our Care on Tuesday released state-by-state fact sheets detailing how many people have lost Medicaid, Children's Health Insurance Program (CHIP), and Affordable Care Act coverage due to Republican policy decisions, including the party's roughly $900 billion in cuts to Medicaid and decision to let enhanced ACA subsidies expire, sending premiums skyrocketing.
“Eight million Americans have lost their health care because Donald Trump and Republicans decided they would rather hand out tax breaks to billionaires than protect working families," said Brad Woodhouse, the president of Protect Our Care. "Every day that healthcare becomes more expensive, a family is forced to make an impossible choice between putting food on the table and staying covered, a senior is forced to ration their medication, and an expectant mother has to travel farther to access maternity care."
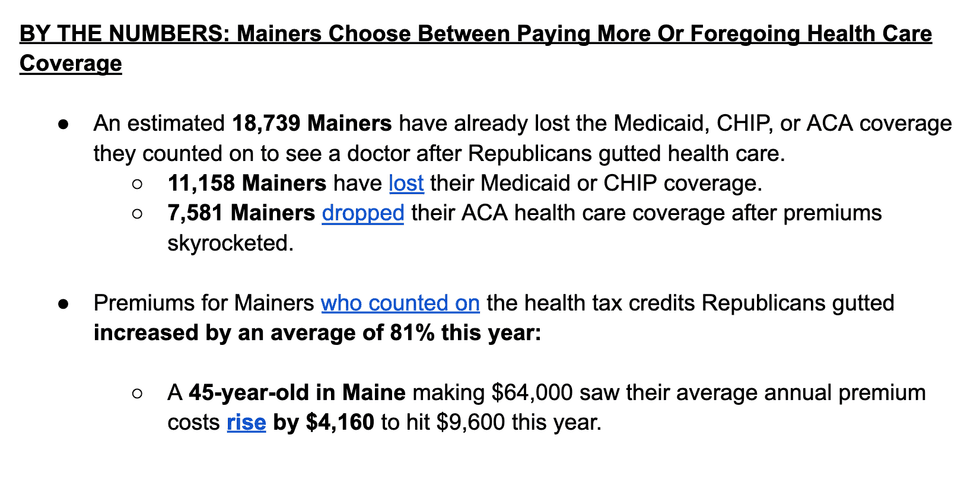
In Maine, where Democrats are looking to finally unseat vulnerable Sen. Susan Collins, more than 18,700 people have lost Medicaid, CHIP, or ACA coverage under the Republican budget law. Included in that total are the more than 7,500 Mainers who dropped ACA marketplace coverage after premiums soared due to the lapse of enhanced subsidies at the end of 2025.
Collins voted to advance GOP budget legislation that included the devastating Medicaid cuts, but voted against final passage.
Protect Our Care noted that "Maine hospitals and clinics are facing a $38 million loss in funding and a 6.7% spike in uncompensated care demand that will affect their ability to keep their doors open."
"As of August 2026, 20 Maine healthcare providers are at-risk, announced cuts, are closing, or have closed," the group added.
More than 25,600 Alaskans have lost health coverage under the Republican budget law and premiums have surged by an average of 346% this year, according to Protect Our Care's fact sheets.
US Sen. Dan Sullivan (R-Alaska), who along with Collins is seen as one of the most vulnerable Republicans this election cycle, voted for the more than $900 billion in Medicaid cuts.
"From Alaska to Florida, these people are our neighbors, our parents, our kids, and they’re sick of paying the price for Republicans’ greed," Woodhouse said on Tuesday. "They deserve better, and in November they will demand it at the ballot box.”

"A plan you will not show the voters before they vote is not reassurance. It is a warning and revealing of Republican priorities.”
In early June, Republican House Speaker Mike Johnson said the GOP has a "plan" to reform Social Security, Medicare, and Medicaid—but would not release the details until "next year," after the 2026 midterms.
But a group of Senate Democrats argued in a letter to Republican leaders on Wednesday that "Americans deserve to have full transparency into Republican plans to attack earned benefits like Social Security." The Democrats—led by Sens. Elizabeth Warren of Massachusetts, Ron Wyden of Oregon, and Chuck Schumer of New York—wrote that "it is time for Republicans to put their money where their mouth is" and "release the plan referenced by Speaker Johnson."
The letter was released as the Senate Finance Committee convened a hearing titled "Exploring Process Approaches for Addressing Social Security Solvency," where Wyden and other Democrats blasted proposals to raise the retirement age and cut Social Security benefits through unaccountable commissions.
"Every time Republicans get their hands on these sorts of ideas for Social Security, life gets worse for older people that count on it to get by," said Wyden, the top Democrat on the Senate Finance Committee. "All we need to do is require billionaires, who have seen their wealth skyrocket to over $9 trillion this year while working people struggle with their grocery bills, to pay their fair share."
According to Social Security's Board of Trustees, the New Deal program's Old-Age and Survivors Insurance Trust Fund will be unable to pay out full benefits by the end of 2032. Members of the Senate Democratic caucus, including Sen. Bernie Sanders (I-Vt.) and Sheldon Whitehouse (D-RI), have introduced legislation that would extend Social Security's ability to pay full benefits for the next 75 years—but neither bill has garnered Republican support.
"We've got a plan. We're not ashamed of our plan," Whitehouse said during Wednesday's hearing. "You actually make people who are making huge amounts of income pay the same Social Security taxes as everybody else, all the way up the rest of their income."
"It's just a question of political will," the senator continued, "and of some people not wanting to own what they want to do to Social Security."
In a radio interview earlier this year, Johnson (R-La) declared that Social Security, Medicare, and Medicaid must be "adjusted and fixed," but did not offer any specific details or policy prescriptions.
"We have a plan to do that," Johnson said, "next year."
House Republicans have previously floated changes such as raising the full Social Security retirement age, which would cut benefits across the board.
In their Wednesday letter to Johnson and Senate Majority Leader John Thune (R-SD), Senate Democrats wrote that "it is critical that the American people understand where Republicans truly stand regarding our preeminent economic security program."
"For decades, Republicans have attacked and undercut Social Security, aiming to cut benefits or privatize the program," the Democratic lawmakers wrote. "A plan you will not show the voters before they vote is not reassurance. It is a warning and revealing of Republican priorities.”

"Pregnant woman disenrolled by mistake. Long waits to get through to the call center for help. No clarity on the rules. Medicaid work reporting requirements don’t work."
A growing chorus of Democratic lawmakers, policy experts, and advocacy organizations is calling on the Trump administration to immediately rescind a rule imposing more strict work reporting requirements on Medicaid recipients, a demand that came as Nebraska began kicking people off the healthcare program for not complying with the new mandates.
Under the expanded requirements, which were established by a 2025 Republican budget package that President Donald Trump signed into law, certain Medicaid recipients must document at least 80 hours per month of work or another qualifying activity to continue receiving assistance. In a statement late last week, Families USA executive director Anthony Wright warned that "these new paperwork requirements will push patients off coverage—not because they aren’t working or not eligible, but because of bureaucratic burdens."
Wright noted that under new rules stemming from the 2025 GOP budget law, even people with terminal cancer and other serious illnesses aren't necessarily exempt from the work reporting requirements, which apply to people between the ages of 19 and 64 who don't have a disability and aren't pregnant, in states that expanded Medicaid under the Affordable Care Act.
"The requirement that a patient doesn’t just need to have cancer or another condition but must produce the equivalent of a doctor’s note with a finding that the conditions leave them unable to work," said Wright, "is nowhere in the underlying statute, and unworkable."
A pair of Democratic lawmakers, Sen. Ron Wyden (D-Ore.) and Rep. Frank Pallone Jr. (D-NJ), similarly warned in a letter late last week that the Trump administration's implementation of the new work requirements "transforms Medicaid from a healthcare program into a bureaucratic maze that will fail eligible Americans, by design."
"It will strip coverage from people not because they are not already working or refuse to work, but because they cannot navigate a complex web of forms, passwords, and deadlines," the lawmakers wrote. "Implementing ineffective, exclusionary work reporting requirements will create costly administrative barriers and deny Americans access to health care, resulting in poorer health, higher mortality, and reduced financial security."
Wyden and Pallone urged the Trump administration to withdraw what the lawmakers described as a "disenrollment scheme" as Nebraska became the first in the US to disenroll Medicaid recipients for failing to comply with the reporting mandates.
The advocacy group Nebraska Appleseed has warned that the work requirements could put 40,000 Nebraskans at risk of losing Medicaid coverage. The requirements took effect in Nebraska on May 1—eight months ahead of schedule—and the state began disenrolling people for purported noncompliance on August 1.
In a blog post published last week, Nebraska Appleseed observed that the three months between the start of the work requirements and the first round of disenrollments was marked by "mass confusion," with Medicaid recipients experiencing "long call center waits, inoperable language lines, understaffed and undertrained caseworkers, policy questions gone long-unanswered, and the lack of public state data."
Joan Alker, executive director of the Center for Children and Families at Georgetown University, pointed with alarm to local reporting about the early impacts of the work reporting mandates in Nebraska.
"So it begins," Alker wrote in a social media post on Monday. "Pregnant woman disenrolled by mistake. Long waits to get through to the call center for help. No clarity on the rules. Medicaid work reporting requirements don’t work."
Under a new policy the administration is defending in court, low-income people with cancer, HIV, Parkinson's, and other life-threatening illnesses must prove they're too sick to work or risk losing their health insurance.
A federal judge on Thursday denied a request by more than two dozen Democratic states to halt a Trump administration policy announced last month that would require Medicaid recipients with terminal diseases to prove they are too sick to work in order to be exempt from new work requirements that go into effect this coming January.
While introducing over $1 trillion in tax cuts for the wealthiest 1% of Americans, last year's massive GOP tax and budget bill also imposed new 80-hour-per-month work requirements that states must implement for Medicaid expansion recipients, who receive government-subsidized insurance coverage at or below 138% of the poverty line.
The law specified that those who are “medically frail or otherwise have special medical needs” are excluded from the work requirement, and specifically listed people with a “serious or complex medical condition.” But it remained unclear what exact conditions met these criteria.
Earlier this month, the Centers for Medicare and Medicaid Services (CMS) introduced a new rule stating that even if a person receives a terminal diagnosis for a disease like cancer, HIV/AIDS, or Parkinson's, that is still not enough for them to be exempt from the work requirements.
Beginning on January 1, 2028, it says they must also demonstrate to states that their condition “significantly impairs” their ability to meet the work requirement.
Democratic attorneys general in 25 states and the District of Columbia filed a preliminary injunction over the rule late last month, arguing that CMS had rewritten the law to introduce a vague and needlessly restrictive new hurdle that vulnerable people will face in obtaining desperately needed care.
“This is one of those cases where it’s really hard to overstate how dire the consequences could be,” North Carolina’s Democratic attorney general, Jeff Jackson, told Politico. “You’re going to have 50 states doing 50 different things, and we’re all going to have to create a whole new bureaucracy... You are talking about a lot more paperwork, more evaluations, more doctor visits, and a lot more work for doctors themselves.”
The Democratic AGs argued that implementation of the work requirements should be paused because they lacked the staff or capacity to meet the timeline set by CMS, which requires states to communicate to enrollees how they'll be affected by the changes by the end of August.
US District Judge Richard Stearns on Thursday denied their initial request to immediately halt the implementation of the requirements while the lawsuit proceeds, but also did not rule on the lawsuit's merits, which are scheduled to be decided before the requirements go into effect on January 1.
Several medical associations, including the American Medical Association, the American College of Physicians, and the American Academy of Pediatrics, have come out against the rule, arguing that it would have dire consequences for people who suffer from severe illness.
"One of the most significant factors in whether someone survives a cancer diagnosis is whether they have health insurance coverage," Lisa Lacasse, president of the American Cancer Society Cancer Action Network, explained in June.
"The new restrictions link the definition of medical frailty to a person’s ability to work," she continued. "This would mean cancer patients and survivors who are suffering from debilitating side effects of the disease or treatment would have to officially prove they can’t work, in a process that is likely to be difficult and take a long time."
The nonpartisan Congressional Budget Office has projected that over the coming decade, changes to healthcare policy introduced by Republicans would increase the number of uninsured Americans by about 11.8 million.
Around 5.7 million of them are projected to be Medicaid recipients who either do not meet the 80-hour work requirement or are otherwise eligible but tripped up by one of the newly imposed paperwork hurdles.
Taya Graham and Stephen Janis argued earlier this week in a piece for The Real News Network that eligible people losing coverage is not an unfortunate side effect of the law, but a goal of the Republicans who passed it, who sought a way to thin the ranks of those who qualify for Medicaid without having to take the politically unpopular step of actually clawing back benefits.
They wrote that what has happened to recipients of the Supplemental Nutrition Assistance Program (SNAP) illustrates how burdensome these new requirements may become.
As The New York Times reported earlier this month, in Arizona, 440,000 people have already been dropped from SNAP after it enacted a formidable regime of paperwork for low-income recipients to prove eligibility, including requiring some people with panhandling income to obtain documentation from donors who drop them a buck on the street.
"If this is what people receiving SNAP benefits have been subjected to," Graham and Janis wrote, "imagine what’s going to happen to people who will need to navigate the new [Medicaid] requirements while struggling with a debilitating or terminal illness."
Medical issues are a leading cause of bankruptcy in the US. According to one study, over 4 in 10 cancer patients over 50 had depleted all their assets within two years of diagnosis.
Melanie D’Arrigo, a campaigner for single-payer healthcare in New York, said that President Donald Trump "cut cancer research, cut healthcare,” and with new Medicaid restrictions, “wants to make sure Americans continue to work as they go broke battling cancer.”

Trump and his allies in Congress have not so much dismantled these programs yet as chipped away at them; if this movement continues unabated, we may be left with the crumbling foundations of programs that were built to last.
There is reason to celebrate Medicare and Medicaid turning 61 years old. Both highly successful programs were signed into law by President Lyndon B. Johnson on July 30, 1965 as a cornerstone of his Great Society agenda. But this year, our celebration is tempered by grave concern over the future of both programs under the Trump regime.
Let’s compare the words of the two presidents:
LBJ:
No longer will older Americans be denied the healing miracle of modern medicine. No longer will illness crush and destroy the savings that they have so carefully put away over a lifetime. No longer will young families see their own incomes, and their own hopes, eaten away simply because they are carrying out their deep moral obligations to their parents.
It’s not possible for us to take care of… Medicaid, Medicare, all these individual things. They can do it on a state basis. You can’t do it on a federal. We have to take care of one thing: military protection. We have to guard the country.
The comparison speaks volumes. One is a leader who understood that the federal government has a crucial role in the protecting the health and well-being of our most vulnerable citizens—including the poor, disabled, and the elderly. The other is a president who claims to support Medicare and then says that the federal government can’t afford it because of his illegal war in Iran. So much for supporting Medicare.
But this goes deeper than Trump’s rhetoric. The Medicare program, like Social Security, is at a pivotal point in its history. The Part A hospital) trust fund must be fortified so that it doesn’t run dry in the 2030s. (There are reasonable solutions that Congress could enact without hurting seniors.) So far, though, we have heard no constructive ideas from Trump.
More urgently, though, the Trump administration is actively undermining the "traditional Medicare" program that LBJ signed into law. The administration has begun a pilot program to use AI bots to determine whether traditional Medicare patients will be covered for procedures their doctors have ordered. This appears to be an attempt to cut costs by erecting obstacles to medically necessary care—with decisions made by bots instead of human beings.
It could be the first step in a scheme to corrupt traditional Medicare and make it more like the privatized Medicare Advantage program run by for-profit insurers, which is a glorified HMO (with frequent denials of care, limited provider networks, and surprise out-of-pocket costs for beneficiaries). Unfortunately, thanks to deceptive but pervasive advertising, Medicare Advantage has now captured more than 51% of the market, leaving traditional Medicare with a shrinking share of enrollees.
The problem is that Medicare Advantage (MA) puts profits over patients. Participating insurance companies have been overbilling the federal government by billions of dollars a year. Ironically, this privatized program was supposed to save taxpayers money. Instead, Medicare Advantage plans cost the government an average of 14% more per patient than traditional Medicare. That translates into an additional $76 billion in federal spending this year alone.
The bottom line: Medicare Advantage puts taxpayers’ money into the hands of large insurance companies while failing to deliver superior or more cost-effective care. It is fair to say that this is not what LBJ had in mind when he created the public Medicare program. (Medicare Advantage arrived—in nascent form—in 1997, after considerable pressure from the insurance industry.)
When we talk about the financial shortfall facing the Medicare program, we must look at Medicare Advantage as an aggravating factor. Reining-in MA would go a long way toward restoring the overall program to fiscal health—along with other commonsense reforms. Unfortunately, the Trump administration has been inconsistent on this issue, initially floating strict curbs on MA overpayments but ultimately rewarding insurance companies with higher payouts.
Traditional Medicare is far from perfect. It should have caps on patients’ out-of-pocket medical costs. It should cover vision, dental, and hearing care. (President Joe Biden attempted to expand coverage in the ill-fated Build Back Better Act.) These are improvements that we have long urged Congress and the White House to enact.
Medicare also faces compound financial challenges—including the overall rise in healthcare costs and soaring prescription drug prices. The Biden administration and Democrats in Congress took a major step in the right direction with the Inflation Reduction Act, which empowered Medicare to negotiate drug prices with Big Pharma. This process is expected to save the government more than $230 billion by 2031.
For the most part, the Trump administration has adhered to the law and continued negotiating with drugmakers—but it also expanded the list of cancer drugs that won’t be eligible for negotiations. The president has largely relied on smoke and mirrors to make it appear that the administration is "tough on Big Pharma," using gimmicks like TrumpRx. Meanwhile, in a move that will make medications less affordable for seniors, the Trump administration has just announced it is ending Biden-era subsidies in the Medicare Part D prescription drug program.
Of course, it’s also Medicaid’s 61st anniversary. The damage that Trump and the Republicans have done to Medicare’s sister program would take up another entire article. Suffice it to say that more than 3 million Americans have already lost health coverage since Trump and the GOP enacted their Big, Ugly Bill, which slashed nearly $1 trillion from Medicaid. (This also hurts older people dually enrolled in both Medicare and Medicaid.) It was correctly labeled the biggest cut in healthcare in US history—to pay for tax cuts largely benefiting the wealthy.
The political right has always been wary of the New Deal and Great Society legacy programs that lifted people out of poverty and provided older and lower-income Americans with basic retirement and health security. Some on the right have outright committed themselves to dismantling these programs, despite their distinguished histories. Trump and his allies in Congress have not so much dismantled these programs yet as chipped away at them under the guise of fighting "fraud and abuse." If this movement continues unabated, we may be left with the crumbling foundations of programs that were built to last, for the good of the American people.

Medicare has become living proof that public, universal health insurance is superior to private insurance in every way.
Sixty one years ago, July 30, 1965, Congress enacted Medicare to provide health insurance for people ages 65 and older and the disabled regardless of income or medical history. At the Harry S. Truman Presidential Library in Independence, Missouri, former President Harry S. Truman and his wife, former First Lady Bess Truman, became the first recipients of the new Medicare health insurance program. President Lyndon Johnson and the US Congress enacted Medicare under Title XVIII of the Social Security Act.
Medicare was a momentous act because it provided new health insurance for people ages 65 and older and the disabled regardless of income or medical history. In the years since, Medicare has become living proof that public, universal health insurance is superior to private insurance in every way. Medicare is more efficient than private health insurance and is administered at a cost of 3-4%, as opposed to private, for-profit health insurance, which has administrative costs above 15%.
Following the successful 1965 grassroots campaign to enact Medicare, many also believed that the dream of a full national, single-payer health insurance system that included all age groups, “Medicare for All,” was right around the corner. Unfortunately decades later, Medicare still has not been expanded. Most of the changes have been contractions with higher out-of-pocket costs for beneficiaries and repeated attempts at privatization by Big Pharma, Big health insurance industry companies-oligarchs-profiteers, and their champions in the White House and Congress.
Big insurance and Big Pharma continue opposing legislation for the new, improved Medicare for All because these resistant, self-serving industries have the most to lose if their huge profits are redirected to direct patient care for all. Individual and corporate predators regard democracy, government, and community as obstacles to their greed and avarice, always placing profits over individual patients, families, and public health. It’s no wonder so many beholden members of Congress want to protect the interests of Big Insurance and Big Pharma, industries that spent $371 million on lobbying in 2017 alone.
The Heritage Foundation’s Project 2025, framed by former Trump administration staffers and secretly endorsed by President Donald Trump himself, proposes changes in Medicare benefits that could destroy Medicare as we know it. Instead, we must fight back and expand Medicare. Although health insurance affordability for the majority of US citizens still remains elusive, President Trump’s health insurance plan still wants to shift many more dollars into private, Wall Street insurance industry hands. The takeover of public health insurance, as with Medicare Advantage plans and others, by private Wall Street entities continues apace as Republicans and Trump propose to increase taxes and give it to the private profit insurance industry—the basic source of our profound administrative waste, along with the costly administrative burdens they place on the delivery system that requires large profits. Profiteering continues unabated as private insurance sells us services we don’t need or want, such as deductibles and other cost sharing and maintenance of narrow networks, requiring prior authorization with increased administrative costs, excessive ongoing paperwork, and documentation requirements, all while avoiding paying for surprise bills and other denied benefits.
No greater disconnect exists between the public good and private interests than in the voracious US system of for-profit Big Insurance and Big Pharma.
Dealing with Covid-19 could have been more lifesaving if Medicare for All had been in place. A New York Times editorial, "Health Care for Some is a Recipe for Disaster," stresses the importance of covering everyone. Even before Covid-19 was known to humans, Northeastern University professor of public health, Wendy Parmet, presciently warned that the push to exclude immigrants from access to healthcare services would be both dangerous and quixotic. “None of us can be self-sufficient in the face of a widespread epidemic,” she wrote in 2018. “That is just as true for noncitizen immigrants as everyone.” In any pandemic, self-sufficiency can be self-deluding; everyone’s health, citizens, immigrants, etc. alike is only as good as our most vulnerable neighbor’s.
Truly a recipe for disaster, vested interests reject the science of public health epidemiology by asserting that only a slow, incremental approach to health insurance reform is possible or acceptable. So, what are we willing to settle for, should we just settle for what we can get? Lower the expectations, turn down the public heat, and keep waiting?. Gradualism, baby steps, extending health insurance coverage to some, but not all, is the mantra of the day; "Medicare for Some," but not "Medicare for All," is fawned over by politicians, profiteers, and advocacy groups alike while reducing communities resources to deal with dangerous epidemics and other health problems.
Virtually all the risky gradual reforms being touted would reinforce a dysfunctional health insurance system with as many standards of insurance as there are dollars to purchase them. It would further lock us into an obsolete private insurance-based model that holds everyone's health hostage to profiteering HMOs and unaccountable big insurance companies for years to come. For these proponents of political expediency, the question remains: Who will be left behind while we wait? Every year many unnecessary deaths are linked to lack of health insurance coverage. Pandemics can quickly increase these numbers.
Big Insurance and Big Pharma dominate our government, and public health takes a back seat to the need for private profit. Many government leaders from both political parties share the same "profits over public health" ideology, even though the Covid-19 pandemic clearly showed how our economic system failed to serve our citizens by allowing these groups to privatize, sabotage, fragment, and cripple our health, public health, and other social services. Many of the changes in traditional Medicare have been contractions with higher out-of-pocket costs for beneficiaries and repeated attempts at privatization by Big Pharma, and Big Health insurance. No greater disconnect exists between the public good and private interests than in the voracious US system of for-profit Big Insurance and Big Pharma and their inherent tendency to invent new needs, disregard all boundaries, and turn everything into an object for sale and big profit.
Medicare for All Act (M4A)-2026 is best solution because it meets eight basic standards:
To continue our 61 years of progress, it’s time to upgrade Medicare by establishing a 21st century improved “Medicare for All” health insurance system that covers all age groups, cradle to grave. Newborns will leave the hospital with their new Medicare card, and drop it off years later at life’s end. Two comprehensive M4A bills now filed in Congress, H.R. 3069 and S.1506, propose to insure or cover all medically necessary services. Patients have their choice of physicians, mental health professionals, other healthcare professionals, hospitals, and clinics.
M4A insured health services include:Because our government, instead of private profit health insurance companies, serves us as the health insurance financing authority, co-pays and deductibles paid at health professionals' offices are ended because payment for health insurance is fully prepaid directly into Medicare, much like Social Security, and covered at first dollar amounts. This means the obsolete 80%-20% payment split between private health insurance companies and Medicare is eliminated, with Medicare for All covering 100%.
The major reason private health insurers are more expensive than government health programs in the US is due to profiteering and administrative costs. Those extra taxpayer funds going to private insurers include costs such as advertising and marketing of their plans, costs of contracting for restrictive provider networks, administering prior authorization requirements, complex systems of processing claims including denial of benefits, simple administrative costs of operating large corporate entities, and distributing generous profits to their executives and passive high profiteering by Wall Street investors.
The Medicare for All Act-2026, now filed in Congress, would much better fill our healthcare financing needs without wasting hundreds of billions of dollars on superfluous administrative costs and end immense profiteering by private insurers and Big Pharma. The USA is a country where health insurance for medical and mental healthcare is a function of socioeconomic status. Everyone knows that this inhumane system should have been corrected long ago.
Please tell your legislators that it’s time to end inadequate and dangerous health insurance programs. Insist on real health insurance reform essential for individuals and families. American history is filled with examples of fundamental, democratic change brought about by successful mass action and public pressure against the counseling of the go-slow, vested-interest crowd. No more waiting! Ask your legislators to fully support Medicare For All 2026 now: H.R. 3069 and S. 1506

While America’s current healthcare system is painfully vulnerable to Republican attacks, there is an opportunity to create a better future where all Americans can rely on guaranteed healthcare.
Sixty-one years ago, President Lyndon Johnson signed Medicare and Medicaid into law, while former President and long-time national health insurance champion Harry Truman watched. What Johnson and Truman understood was that the fight for guaranteed healthcare for everyone has been a generations-long struggle. The creation of Medicare and Medicaid was a key victory in that struggle. Importantly, though, Medicare and Medicaid are—to paraphrase what President Franklin Roosevelt said about the signing of Social Security into law—“a cornerstone in a structure which is being built but is by no means complete.”
After President Truman was unable to achieve his goal of guaranteed healthcare for all Americans, healthcare advocates decided to move incrementally. They began by pushing to cover seniors. Older Americans have the highest medical costs, the hardest time affording private health insurance, and need care the most often. The signing of Medicare achieved this important milestone, alongside the creation of Medicaid to cover healthcare for low-income Americans.
In 1972, Medicare was expanded to cover people with disabilities. But that is where progress stopped. It is well past time that we expand Medicare to cover children and everyone in between. We must also improve Medicare to cover such vital services as hearing, vision, dental and, perhaps most importantly, long-term care. And we must, in this age of abhorrent income and wealth inequality, require the wealthiest to contribute more while eliminating all premiums, co-payments, co-insurance, and deductibles.
Currently, we are at a crossroads. While America’s current healthcare system is painfully vulnerable to Republican attacks, there is an opportunity to create a better future where all Americans can rely on guaranteed healthcare.
With Republicans doing everything they can to disrupt and dismantle the current healthcare system, it is the perfect time to fight for a more durable and universal alternative.
Shamefully, Republicans are chipping away at both Medicare and Medicaid. The attacks take many forms. They include the effort to confuse Americans with the inferior, propagandistically named “Medicare Advantage;” the Trump administration giving AI the power to overrule doctors and block care for Medicare patients; the $1 trillion in cuts to Medicaid and the Affordable Care Act in the so-called Big Beautiful Bill (beautiful for billionaires, ugly for everyone else) passed by Republicans; and new Republican rules for Medicaid that would force cancer patients to get back to work and would cause millions of Americans to lose their healthcare coverage. Though Republican politicians would deny it, their hostility to Medicare and Medicaid is overwhelming.
Meanwhile, Democrats are working to expand and improve Medicare and Medicaid. They have taken concrete steps to lower prescription drug prices. The Inflation Reduction Act, which gives Medicare the power to negotiate for lower prices, was signed into law by a Democratic president, Joe Biden. Democrats are fighting to provide those same savings to those with commercial insurance and lower prices in other ways as well. Importantly, a growing number of Democrats are supporting and fighting for improved and expanded Medicare for All.
It may seem daunting and overwhelming to think about achieving improved and expanded Medicare for All in the current political environment, but it is within sight. Indeed, I have written a book-length road map to achieving improved and expanded Medicare for All, which will be released this September. It is called The Road to Medicare for All: A Call to Action (Routledge Press, forthcoming, 2026).
What would improved and expanded Medicare for All mean? It would mean this: no premiums, co-pays, co-insurance, or deductibles. It would mean comprehensive healthcare coverage for everyone in America, automatically. It would mean going to the doctor of your choice, without worrying whether your provider is in your insurer’s network. The vision of improved Medicare for All would include all services being covered automatically, including dental, vision, and hearing coverage. Medicare should also be expanded to cover long-term care, both at home and in nursing homes.
This November’s election will determine the future of Medicare and Medicaid. Will Republicans make Medicare and Medicaid work even worse for Americans? Will even more hospitals and nursing homes close? Or will Democrats be able to fight back and not only defend Medicare and Medicaid from Republican attacks, but enact a bold vision of improved and expanded Medicare for All?
With Republicans doing everything they can to disrupt and dismantle the current healthcare system, it is the perfect time to fight for a more durable and universal alternative: improved and expanded Medicare for All. Instead of a precarious and shaky patchwork system where a disruption to your healthcare is one job loss or plan change away, it is time to fight for a world where healthcare is truly a right, not a privilege.